Patients who received a thin-strut biodegradable-polymer sirolimus-eluting stent during percutaneous coronary intervention faced a higher risk of net adverse clinical events in the first month after the procedure if they were treated for myocardial infarction rather than for angina, but that early excess disappeared over the following three years. In a prospective, multicenter Korean registry of 932 patients, the one-month rate of the composite endpoint was 12.1 percent in the myocardial infarction group versus 7.0 percent in the non-infarction group, a statistically significant difference with a multivariable hazard ratio of 1.66 and a 95 percent confidence interval of 1.01 to 2.72. Yet in a landmark analysis restricted to patients who were event-free at one month, outcomes from one month to three years were essentially indistinguishable between the two groups, with net adverse clinical events occurring in 12.4 percent of infarction patients and 13.3 percent of non-infarction patients, a hazard ratio of 0.84 with a confidence interval of 0.55 to 1.29 and a p value of 0.425.
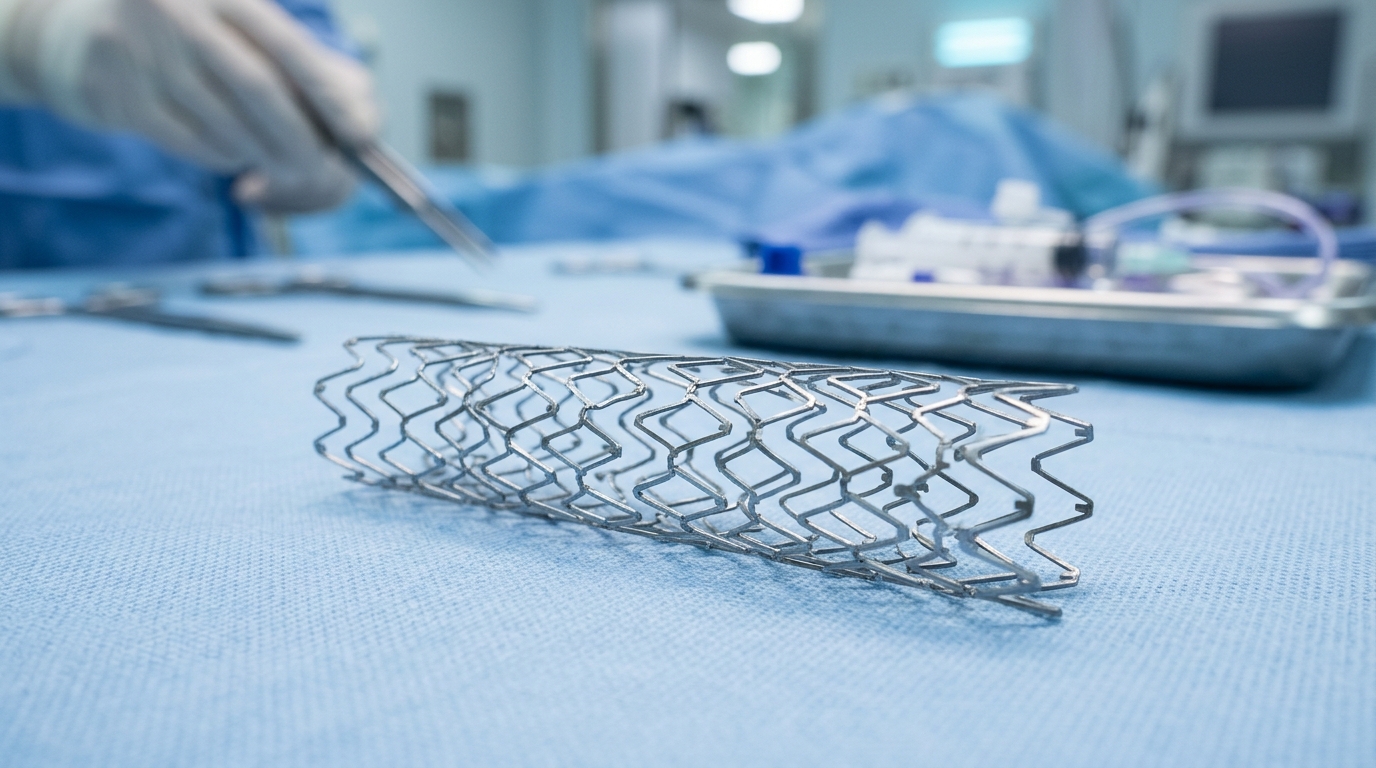
All participants underwent percutaneous coronary intervention with at least one Ultimaster or Ultimaster Tansei stent, thin-strut cobalt-chromium devices with an abluminal-gradient bioresorbable poly(D,L-lactide-co-caprolactone) coating that elutes sirolimus and is designed to fully resorb within three to four months, leaving behind a bare-metal scaffold. Of 1,001 patients enrolled, 69 were excluded because their clinical presentation could not be determined, leaving 346 patients in the myocardial infarction group, comprising 188 with ST-elevation infarction and 158 with non-ST-elevation infarction, and 586 in the non-infarction group, comprising 376 with unstable angina and 210 with stable angina.
That landmark approach, increasingly applied in stent research, separates events driven by patient and lesion factors in the acute phase from events driven by stent-related processes such as vascular healing and late thrombosis.
During the first month, the excess risk in the infarction group was driven primarily by numerical excesses in cardiac death and bleeding rather than by stent-specific complications. Bleeding occurred in 9.5 percent of infarction patients versus 6.1 percent of non-infarction patients, a difference that trended toward significance with a hazard ratio of 1.60 and a confidence interval of 0.93 to 2.74. Cardiac death occurred in five infarction patients and two non-infarction patients in the first month, a difference that did not reach statistical significance. The authors attribute the early cardiac deaths largely to patient- and infarction-related factors, including lower left ventricular ejection fraction, which averaged 52.0 percent in the infarction group versus 60.3 percent in the non-infarction group, and more complex coronary anatomy, with type C lesions in 86.7 percent of infarction patients versus 68.3 percent of non-infarction patients.
Medication patterns at discharge also differed in ways that may explain the early bleeding imbalance. Roughly 86 percent of non-infarction patients received clopidogrel, while about two-thirds of infarction patients were discharged on potent P2Y12 inhibitors, ticagrelor or prasugrel, which carry a higher bleeding risk. Ticagrelor was prescribed for 56.7 percent of infarction patients versus 6.1 percent of non-infarction patients, and beta-blockers for 68.8 percent versus 49.7 percent. The authors suggest that the early imbalance in clinical events reflects the inherent vulnerability of acute infarction presentations and the more potent antiplatelet regimens used in this setting, rather than stent-related complications, since the remaining individual endpoints, including stent thrombosis, repeat revascularization, and target lesion failure, did not differ significantly between groups at one month.
At one year, the cumulative incidence of net adverse clinical events remained numerically higher in the infarction group at 20.5 percent versus 14.9 percent, a relative difference of approximately 40 percent that did not reach statistical significance. Bleeding showed a similar borderline pattern at 16.5 percent versus 12.1 percent, with a univariable hazard ratio of 1.41 and a confidence interval of 1.00 to 2.00 and a p value of 0.053. By contrast, stent-related endpoints were low and comparable: one-year target lesion failure was 6.0 percent overall, 5.3 percent in the non-infarction group and 7.2 percent in the infarction group, and one-year target lesion revascularization occurred in 3.3 percent of all patients, 3.2 percent versus 3.5 percent. The overall target lesion failure rate sits at the upper end of the 3 to 5 percent range reported in prior Ultimaster studies, which the authors attribute to more complex coronary anatomy and a higher proportion of acute coronary syndrome presentations in their cohort.
The landmark analysis yielded the study’s central finding. Among the 847 patients who were event-free at one month, no significant differences emerged between groups for any endpoint from one month to three years. Cardiac death occurred in 5.8 percent of infarction patients versus 4.3 percent of non-infarction patients, recurrent myocardial infarction in 0.6 percent versus 0.5 percent, cerebrovascular accident in 1.5 percent versus 2.4 percent, total bleeding in 8.4 percent versus 8.9 percent, and stent thrombosis in 0.3 percent in both groups. Target lesion failure during the landmark period was 9.3 percent versus 8.5 percent, and target vessel failure 10.1 percent versus 9.6 percent, all with hazard ratios crossing unity. The interaction between infarction status and follow-up period was not significant for any endpoint, with a p value of 0.588 for the primary composite, though the authors note that interaction testing had limited statistical power given the modest number of early events.
Follow-up was robust, with one-year data available in 888 patients, 95.3 percent of the cohort, and three-year follow-up completed in 858 patients, 92.1 percent. The median follow-up duration was 35.9 months. In a subgroup analysis by infarction subtype, outcomes were comparable between ST-elevation and non-ST-elevation infarction in both periods, including stent-related endpoints during the landmark period, suggesting that later stent-related outcomes are governed by the healing of the biodegradable-polymer stent consistently across infarction subtypes, while the early excess risk reflects the acute presentation common to both.
The authors place their findings in the context of a broader shift in interventional cardiology. Earlier substudies of randomized trials using older-generation durable-polymer stents had reported that patients treated for acute coronary syndromes showed higher rates of cardiac death and stent thrombosis at 18 months of cumulative follow-up, a pattern attributed to delayed endothelialization of first-generation devices. In contrast, more recent large-scale evidence, including a randomized all-comers trial of 1,653 patients treated with contemporary stents and an individual patient data meta-analysis of randomized trials, found comparable five-year outcomes across acute and chronic coronary syndrome presentations. The present study extends this picture by specifically isolating patients with myocardial infarction and by separating the early periprocedural phase from subsequent follow-up through a one-month landmark. The authors also emphasize that improvements in secondary prevention, with statins prescribed at discharge in more than 90 percent of patients and wider use of potent P2Y12 inhibitors and intensive lipid-lowering therapy after infarction, may have narrowed the long-term difference between infarction and non-infarction patients independently of the stent platform, making the comparable long-term outcomes the combined result of a contemporary stent and contemporary medical therapy rather than of the stent alone.
Several limitations temper the conclusions. This was an observational, non-randomized registry, so selection bias and residual confounding from unmeasured baseline differences cannot be excluded despite multivariable adjustment for age, sex, hypertension, diabetes, smoking status, prior percutaneous coronary intervention, family history, creatinine, left ventricular ejection fraction, lesion classification, and intravascular ultrasound use. The findings apply to a single thin-strut biodegradable-polymer sirolimus-eluting stent platform and may not generalize to other devices. Angiographic lesion classification relied on operator assessment without core laboratory adjudication, routine angiographic follow-up was not performed so subclinical restenosis may have been underestimated, and the study population was confined to Korean patients at tertiary cardiovascular centers, potentially limiting generalizability to other ethnic groups and clinical settings. The authors also caution that the findings do not establish equivalence of long-term risk and that the absence of a comparator stent precludes conclusions about device-specific benefit. Larger comparative studies with longer follow-up are warranted to confirm these results.
Subject of Research: Long-term outcomes of percutaneous coronary intervention with a biodegradable-polymer sirolimus-eluting stent in patients with versus without myocardial infarction
Article Title: Impact of myocardial infarction status on long-term outcomes after PCI with the ultimaster biodegradable-polymer sirolimus-eluting stent
Article References: Yoo, K.-D., Lee, H.-J., Choi, S.-S., Park, G.-M., Jung, J., Lim, S.-H., Her, S.-H., Lee, J.-H., Lee, S. J., Bae, J.-W., & Lee, K. (2026). Impact of myocardial infarction status on long-term outcomes after PCI with the ultimaster biodegradable-polymer sirolimus-eluting stent. Frontiers in Cardiovascular Medicine, 13, Article 1903710. https://doi.org/10.3389/fcvm.2026.1903710
Image Credits: AI Generated
DOI: 10.3389/fcvm.2026.1903710
Keywords: percutaneous coronary intervention, biodegradable-polymer sirolimus-eluting stent, myocardial infarction, net adverse clinical events, landmark analysis, stent thrombosis, target lesion failure, bleeding risk, Korean registry, drug-eluting stent, cardiac death, secondary prevention
News Source: Ophelia Keating. (November 5, 2026). Early Risk After Heart Attack Stenting Fades, Three-Year Data Show. Scienmag.