The vertical-sagittal first, or VSF, protocol is described in a position statement published in the journal Digital and Aligner Orthodontics by Pierre Pujol and Tommaso Castroflorio. Crucially, the authors are explicit that the protocol is a biomechanical concept, not a validated clinical method: no patient sample or outcome dataset was analyzed, and the framework requires prospective controlled studies before any claims of superiority can be made.
The authors draw on established evidence that rotation of the mandible during growth and treatment is a clinically relevant determinant of sagittal expression, and that occlusal plane inclination changes according to the underlying dentoskeletal pattern. When vertical control is inadequate, they argue, posterior extrusion, anterior extrusion, or clockwise rotation of the occlusal plane can mask forward mandibular positioning and shift the correction toward dentoalveolar compensation, meaning the teeth move to disguise a skeletal discrepancy rather than the skeleton itself changing.
The biomechanical core of the VSF concept rests on the relationship between force vector height and tooth movement. Recent evidence cited in the paper demonstrates that occlusal plane stability is significantly influenced by the height and direction of the applied force relative to the molar center of resistance. When forces pass through or above this center, bodily tooth movement with minimal tipping and intrusion can be achieved; forces applied below it tend to produce crown tipping and extrusion. Traditional Class II elastics typically deliver forces below the center of resistance, which the authors say frequently results in uncontrolled extrusion and clockwise occlusal plane rotation. The VSF framework addresses this by employing skeletal anchorage positioned to optimize the force vector trajectory, maintaining vertical control while delivering sagittal correction.
Facial pattern also matters. Three-dimensional analysis of clear aligner therapy has shown that occlusal plane changes during treatment are significantly correlated with patient facial divergence, with hyperdivergent patients demonstrating greater clockwise rotation of the occlusal plane during conventional distalization. The authors therefore suggest that early intervention to stabilize the occlusal plane may be particularly critical in hyperdivergent patients, while patients with brachyfacial or hypodivergent patterns may theoretically derive less benefit, since vertical instability is generally a less prominent component of their Class II presentation.
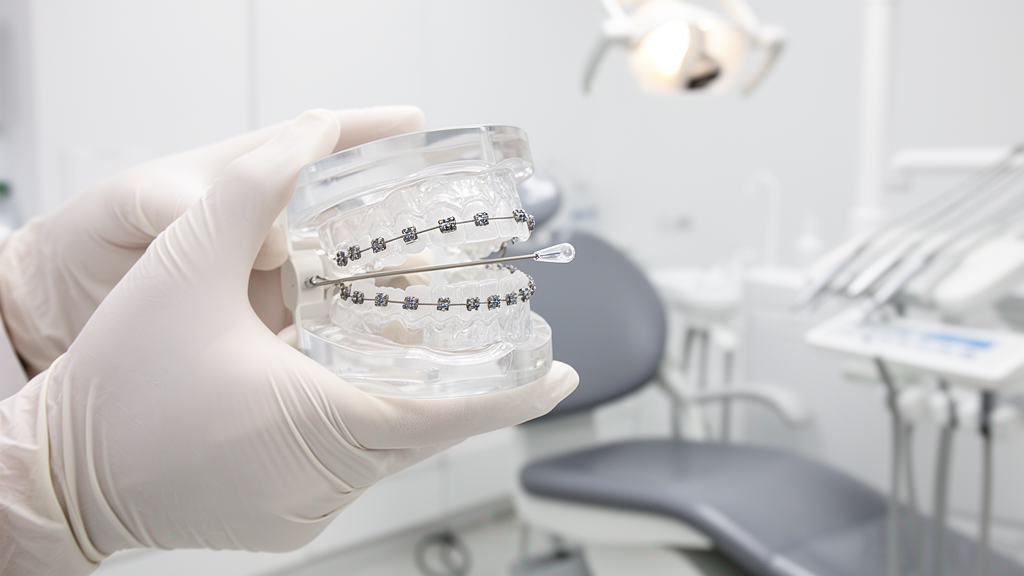
The protocol itself unfolds in two phases. Phase 1 begins with a maxillary temporary anchorage device, typically a miniscrew 1.6 to 2.0 millimeters in diameter, placed in attached gingiva between the first and second premolar region or an equivalent interradicular site chosen according to root anatomy and available bone. The insertion site and angulation are planned to provide primary stability, minimize root proximity, and create a skeletal pivot that supports sagittal traction while limiting unwanted vertical vectors. Into this anchorage, a rigid rectangular distalizing bar is inserted, running from the canine-premolar region to the molar segment, with a nickel-titanium open-coil spring activated between the miniscrew and the bar using a stainless-steel ligature. The configuration is intended to generate a constant, controlled distalizing force while reducing vertical side effects through skeletal anchorage and a guided force pathway.
Supporting elements complete the phase 1 force system. A light elastomeric chain runs from the miniscrew to the canine to prevent canine extrusion, reduce canine lag, and contribute to occlusal plane stabilization, without overloading the anterior segment. Simultaneously, a full-coverage lower clear aligner is introduced from the beginning of the skeletal phase, either passive or selectively active for leveling, lower incisor torque management, or dentoalveolar decompensation. Its primary biomechanical role is to limit lower molar extrusion and reduce the risk of clockwise mandibular rotation. Light type 2 intermaxillary elastics, typically delivering 70 to 120 grams of continuous force, are used as a staged mandibular guidance component rather than a primary distalizing mechanism, a deliberate departure from conventional Class II elastic protocols that rely on higher forces and dental compensation.
The elastic strategy is staged across treatment. In the early phase, light elastics help prevent mandibular retrusion during initial distalization and guide the mandible forward and slightly inferior. During the active growth-sensitive phase, moderate elastics support forward mandibular expression within the CS3 to CS4 cervical vertebral maturation window, when mandibular growth responsiveness is considered optimized. In the finishing phase, light elastics are used only for sagittal stabilization, maintaining gains without inducing further vertical changes. The authors emphasize that the protocol does not claim to create mandibular growth beyond biological limits; its objective is to organize the mechanical environment so that residual growth and functional mandibular positioning, when present, can be expressed under more favorable vertical conditions, with individual growth potential, maturity, facial pattern, and compliance remaining limiting factors.
Phase 2 begins once a stable Class I premolar relationship is reached. The distalizing bar is removed, although the maxillary miniscrew can be retained temporarily as a stabilizing element during controlled movement in the premolar region. During coordination, the same anchorage concept can be maintained through a miniscrew-chain-canine/molar triangular force system, with movements around the premolar regions staged progressively to avoid root interference, preserve vertical stability, and maintain the occlusal plane achieved in phase 1. Final alignment, arch coordination, torque expression, finishing, and occlusal detailing are performed only after the vertical-sagittal environment has been stabilized, with any remaining elastics reduced to a light functional mode. The authors note that cone-beam computed tomography should not be routine solely for checking root proximity, but may be indicated when two-dimensional records or clinical findings suggest limited interradicular clearance.
In their biomechanical interpretation, the authors describe how the system distributes sagittal and vertical components across multiple moderate force vectors rather than a single heavy force. They offer a worked example: a force of approximately 130 grams applied at 30 degrees generates a vertical component of approximately 65 grams and a horizontal component of approximately 113 grams. The oblique force from the miniscrew to the canine, the comparable oblique vectors from the elastics, and the predominantly horizontal distalizing force from the coil spring together form a multi-vector system. The clinical intent, they stress, is not simply to increase total sagittal force but to combine moderate forces in a way that reduces vertical imbalance, with counterclockwise moments from the miniscrew-canine chain and coil-related components intended to counteract the clockwise tendency induced by Class II elastics. They also propose that once Class I premolar relationships are established, the premolar region may act as a functional support rather than a simple occlusal endpoint, a hypothesis they acknowledge remains to be quantified through prospective clinical studies.
The limitations are stated plainly. The protocol is conceptual and requires clinical validation through prospective controlled trials. The skeletal contribution cannot be assumed from occlusal correction alone; three-dimensional imaging is necessary to distinguish true skeletal changes from dentoalveolar compensation. Mandibular response remains biologically limited and patient-specific, and success depends on accurate diagnosis, careful monitoring of root proximity with safety margins of at least 2 millimeters recommended between miniscrews and adjacent anatomical structures, compliance with elastics and aligner wear, and individualized management of vertical facial pattern. The transverse dimension must also be evaluated separately, because sagittal correction on an unstable transverse platform may compromise treatment efficiency and stability, and maxillary expansion may need to be integrated when transverse constriction is present. The authors call for randomized clinical trials comparing VSF with conventional Class II mechanics and other skeletal anchorage protocols, incorporating multiple time points through 24-month post-retention, comprehensive skeletal, dentoalveolar, occlusal-plane and patient-reported outcomes, and standardized three-dimensional imaging with voxel-based registration. Until such evidence is available, they recommend that VSF be applied selectively in well-chosen cases where careful diagnosis indicates favorable growth potential and where the clinician is committed to meticulous mechanical control of both vertical and sagittal dimensions throughout all phases of treatment.
Subject of Research: A conceptual biomechanical protocol for Class II malocclusion correction that integrates vertical stabilization with sagittal correction using skeletal anchorage and clear aligners.
Article Title: The vertical-sagittal first (VSF) protocol for Class II correction: a conceptual biomechanical framework
Article References: Pujol, P., & Castroflorio, T. (2026). The vertical-sagittal first (VSF) protocol for Class II correction: a conceptual biomechanical framework. Digital and Aligner Orthodontics, 1(1), Article 7. https://doi.org/10.1007/s44525-026-00010-8
Image Credits: AI Generated
DOI: 10.1007/s44525-026-00010-8
Keywords: orthodontics, Class II malocclusion, vertical-sagittal first protocol, skeletal anchorage, temporary anchorage devices, clear aligners, occlusal plane, mandibular growth, biomechanics, intermaxillary elastics, dentoalveolar compensation, position statement
News Source: Ophelia Keating. (October 28, 2026). New Orthodontic Framework Pairs Vertical Control With Class II Correction. Scienmag.