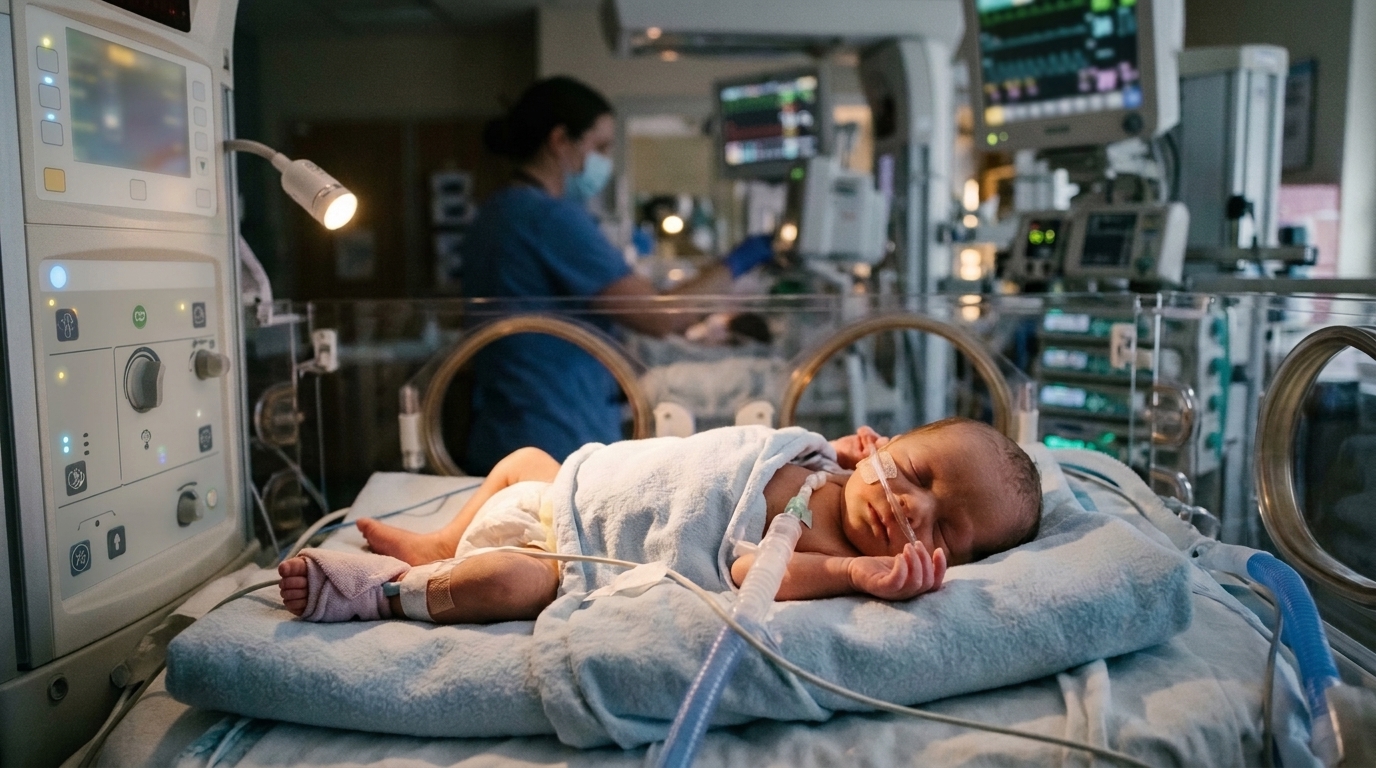
A comprehensive review of perinatal hypoxic-ischemic brain injury proposes Brain Energy Failure as a unifying conceptual framework that links acute metabolic collapse, mitochondrial dysfunction, neuroinflammation, neuroendocrine adaptation, and endogenous neuroprotective signaling in the immature central nervous system. Perinatal asphyxia remains a principal cause of neonatal mortality and long-term neurodevelopmental disability worldwide, continuing to present substantial clinical challenges despite improvements in intensive care. Historically, hypoxic-ischemic injury was predominantly interpreted through the lens of oxygen deprivation, adenosine triphosphate depletion, excitotoxic neurotransmitter release, and oxidative damage. Contemporary research indicates that the severity and progression of neurological deficits cannot be explained exclusively by the initial hypoxic insult. Instead, injury trajectories evolve through dynamic, systemic cross-talk among cellular metabolic pathways, central and peripheral immune responses, and endocrine stress cascades. By evaluating literature published between January 2000 and June 2026 across PubMed, Scopus, and Web of Science, the review delineates how the disruption of cerebral bioenergetics coordinates secondary and tertiary phases of cellular degradation while simultaneously mobilizing endogenous resilience mechanisms.
The developing neonatal brain exhibits exceptionally high baseline metabolic demands because it requires a steady supply of glucose and oxygen to drive mitochondrial respiration, neuronal differentiation, synaptogenesis, axonal growth, and circuit assembly. When oxygen availability is abruptly reduced during perinatal asphyxia, cells undergo primary energy failure within minutes to hours, characterized by electron transport chain disruption, severe intracellular adenosine triphosphate depletion, membrane depolarization, excessive extracellular glutamate release, and massive calcium influx. Although a transient period of partial metabolic recovery often follows, this initial bioenergetic crisis typically initiates secondary energy failure between six and forty-eight hours post-insult. During this secondary window, persistent mitochondrial injury accelerates the generation of reactive oxygen species and reactive nitrogen species, promotes mitochondrial permeability transition pore opening, impairs mitophagy, and triggers apoptotic signaling via cytochrome c release. Rather than operating as isolated downstream anomalies, these oxidative, excitotoxic, and inflammatory cascades represent unified manifestations of impaired cerebral energy homeostasis centered on failing mitochondrial networks.
Parallel to acute cellular stress, perinatal hypoxia rapidly engages systemic neuroendocrine adaptations that directly influence bioenergetic resilience and tissue survival. Hypoxia sensing by central and peripheral oxygen-sensitive systems stimulates the hypothalamic-pituitary-adrenal axis, prompting the secretion of corticotropin-releasing hormone, adrenocorticotropic hormone, and glucocorticoids. In the acute setting, glucocorticoid mobilization supports cardiovascular tone, mobilizes metabolic substrates, and modulates systemic inflammatory cascades. However, prolonged or excessive activation of this neuroendocrine stress response functions as a double-edged sword, potentially suppressing neurogenesis, disrupting synaptic plasticity, and enhancing neuronal vulnerability within susceptible brain structures like the hippocampus. Concurrently, hypoxia alters other hormonal pathways, including growth hormone, insulin-like growth factor-1, and thyroid hormones, which participate in developmental programming. When these endocrine adaptations operate alongside cellular metabolic defenses, they help re-establish homeostatic balance; conversely, when overwhelmed by unmitigated mitochondrial dysfunction, sustained hormonal dysregulation aggravates long-term neurodevelopmental impairment.
At the cellular level, the primary transcriptional coordinator of adaptation to oxygen deprivation is hypoxia-inducible factor-1, an evolutionarily conserved heterodimer consisting of an oxygen-sensitive alpha subunit and a constitutively expressed beta subunit. Under normoxic conditions, the alpha subunit is rapidly hydroxylated by prolyl hydroxylases, polyubiquitinated, and degraded by the proteasome. Hypoxia inhibits prolyl hydroxylase activity, allowing the alpha subunit to stabilize, accumulate, and translocate to the nucleus where it dimerizes with the beta subunit to activate target genes governing angiogenesis, erythropoiesis, glucose transport, and glycolytic shift. By promoting vascular endothelial growth factor and erythropoietin expression, hypoxia-inducible factor-1 facilitates metabolic compensation when oxidative phosphorylation fails. Moderate activation preserves bioenergetic equilibrium and suppresses excessive oxidative stress. Nevertheless, sustained or excessive activation under prolonged hypoxia may induce persistent neuroinflammation and metabolic dysregulation, underscoring that the net outcome of this transcription factor depends closely on injury duration, developmental timing, and the integrity of supporting endogenous defenses.
Complementing hypoxia-inducible transcriptional pathways, heat shock protein 70 and the glutathione antioxidant system serve as critical endogenous defense mechanisms against brain energy failure. Heat shock protein 70 is rapidly induced following oxygen deprivation, oxidative stress, and the accumulation of damaged or misfolded proteins. Acting as a molecular chaperone, heat shock protein 70 stabilizes protein conformation, prevents toxic aggregation, facilitates protein degradation, protects mitochondrial membrane integrity, and blocks caspase-dependent apoptotic pathways. Concurrently, intracellular glutathione represents the principal endogenous antioxidant in neural tissue, protecting developing neurons and glia from free radicals generated by dysfunctional respiratory complexes. Because the immature brain possesses limited baseline antioxidant reserves, rapid glutathione consumption during hypoxia leads to lipid peroxidation, protein carbonylation, and DNA damage. Depletion of glutathione activates nuclear factor-kappa B signaling, which increases the production of pro-inflammatory cytokines, while the preservation of glutathione pools attenuates neuroinflammation, preserves mitochondrial calcium homeostasis, and supports adaptive transcriptional signaling.
Neuroinflammation constitutes a prominent secondary injury process that amplifies cellular damage following perinatal asphyxia. Upon oxygen deprivation, resident microglia transition into reactive phenotypes, generating nitric oxide, reactive oxygen species, and pro-inflammatory cytokines such as interleukin-1 beta, tumor necrosis factor-alpha, and interleukin-6. Although transient microglial activation supports initial cellular debris clearance, sustained inflammatory signaling disrupts the blood-brain barrier, exacerbates mitochondrial respiratory failure, and impairs synaptic maturation. Interleukin-1 beta has been identified as a particularly important mediator linking early neuroinflammatory cascades to chronic behavioral and cognitive impairments. Astrocytes likewise undergo marked functional and morphological transformations, altering their regulation of extracellular glutamate, cytokine release, and blood-brain barrier maintenance. Damage-associated molecular patterns released from degenerating cells, including high-mobility group box 1, further amplify inflammation by activating toll-like receptor 4 and receptors for advanced glycation end products, though direct in vivo evidence of their causative contribution to tertiary-phase developmental deficits remains an area of ongoing study.
The inflammatory response to perinatal hypoxia extends beyond the central nervous system, establishing bidirectional neuroimmune communication across disrupted brain-vascular interfaces. Circulating peripheral leukocytes infiltrate neural parenchyma, while systemic chemokines and cytokines modulate central glial behavior through neurovascular and vagal signaling routes. Furthermore, emerging evidence highlights sex-dependent variations in neuroinflammatory profiles between male and female neonates. Variations in chromosomal architecture and gonadal hormone signaling influence microglial activation states, cytokine profiles, and vulnerability to secondary damage. Estrogens demonstrate anti-inflammatory and cytoprotective properties by limiting microglial activation and decreasing pro-inflammatory cytokine synthesis, whereas variations in androgen signaling modulate neuroimmune responses through separate pathways. These biological disparities indicate that injury trajectories and endogenous repair capacities differ between sexes, providing a strong rationale for exploring sex-stratified neuroprotective approaches in future translational and clinical research.
Nitric oxide signaling occupies a multifaceted role in the progression of perinatal hypoxic-ischemic brain damage. Under physiological conditions, nitric oxide regulates cerebral perfusion, synaptic transmission, and neurovascular coupling through basal enzymatic activity. Following hypoxia, however, excessive calcium influx drives neuronal nitric oxide synthase overactivity, followed hours later by inducible nitric oxide synthase upregulation in activated microglia and infiltrating immune cells. Excess nitric oxide readily reacts with superoxide anions to form peroxynitrite, a potent oxidant that inflicts widespread damage on nucleic acids, structural lipids, and mitochondrial respiratory complexes, particularly cytochrome c oxidase. By impairing mitochondrial electron transport and inhibiting ATP synthesis, peroxynitrite directly exacerbates brain energy failure. In addition, elevated concentrations of nitric oxide and its oxidation products activate inflammatory transcription factors such as nuclear factor-kappa B, promoting persistent cytokine release and establishing a self-sustaining cycle of nitrosative stress, energy failure, and cellular demise.
Evaluating current clinical and experimental neuroprotective interventions through the Brain Energy Failure paradigm highlights critical distinctions between single-target approaches and multimodal therapies. Therapeutic hypothermia remains the standard of care for term and near-term neonates with moderate-to-severe hypoxic-ischemic encephalopathy and is currently the only treatment with demonstrated clinical efficacy. By lowering cerebral metabolic rate and oxygen consumption, hypothermia preserves residual high-energy phosphates, attenuates excitotoxicity, limits free radical production, suppresses microglial activation, and reduces pro-inflammatory cytokine expression. Nevertheless, a substantial proportion of cooled infants still develop permanent motor, cognitive, or behavioral disabilities. This clinical limitation emphasizes that while lowering metabolic demand during the secondary energy failure window provides significant neuroprotection, it does not fully prevent the tertiary phase of chronic neuroinflammation, defective synaptic remodeling, and impaired myelination, thereby necessitating complementary therapeutic interventions.
To address the multi-pathway nature of hypoxic-ischemic cascades, experimental investigations have evaluated various antioxidant, neurometabolic, and anti-inflammatory molecules. Traditional antioxidants such as N-acetylcysteine, melatonin, edaravone, and coenzyme Q10 aim to replenish glutathione stores, scavenge free radicals, and protect mitochondrial integrity. Targeted anti-inflammatory agents, including the interleukin-1 receptor antagonist anakinra and nuclear factor-kappa B inhibitors, seek to interrupt secondary inflammatory amplification. Neurometabolic agents like citicoline promote membrane phospholipid synthesis and support mitochondrial function, while peptide preparations such as Cerebrolysin provide neurotrophic and anti-apoptotic support. In addition, the multifunctional compound 2-ethyl-6-methyl-3-hydroxypyridine succinate has gathered interest because its succinate moiety can act as a substrate for complex II of the electron transport chain while its hydroxypyridine base provides antioxidant free radical scavenging, although published evidence reflects regional clinical experience and preclinical models rather than established global therapeutic superiority.
Among emerging endogenous lipid regulators, palmitoylethanolamide has gained significant preclinical attention for its capacity to modulate multiple interconnected facets of brain energy failure. Palmitoylethanolamide is an endogenous N-acylethanolamide that operates primarily via peroxisome proliferator-activated receptor-alpha signaling. In experimental animal models of perinatal asphyxia, administration of palmitoylethanolamide significantly reduces microglial activation, suppresses reactive astrogliosis, decreases tumor necrosis factor-alpha, interleukin-1 beta, and interleukin-6 levels, and diminishes lipid peroxidation. Crucially, palmitoylethanolamide displays direct mitoprotective properties, preserving mitochondrial membrane potential, supporting ATP synthesis, and preventing the release of pro-apoptotic factors. These combined actions preserve hippocampal neuronal architecture and improve long-term behavioral outcomes in animal studies. Despite these encouraging preclinical findings, human clinical trials in neonatal hypoxic-ischemic encephalopathy are lacking, leaving pharmacokinetic properties, therapeutic windows, optimal pediatric dosing, and compatibility with therapeutic hypothermia unresolved translational hurdles.
Tracking the temporal evolution of hypoxic injury and assessing targeted interventions requires the development of comprehensive, multimodal biomarker panels. Because brain energy failure involves concurrent metabolic, inflammatory, endocrine, and degenerative processes, no individual biomarker can adequately capture injury severity or predict developmental outcomes. Candidate biomarkers include hypoxia-response markers like hypoxia-inducible factor-1 alpha, endogenous defense markers such as heat shock protein 70, redox balance metrics including the ratio of reduced to oxidized glutathione, and nitrosative indices like circulating nitric oxide metabolites. Structural damage markers, such as glial fibrillary acidic protein, neuron-specific enolase, S100B, and neurofilament light chains, provide direct measures of astrocytic injury and axonal degeneration. Simultaneously monitoring endocrine markers, including cortisol and adrenocorticotropic hormone, together with neurotrophic factors like brain-derived neurotrophic factor and insulin-like growth factor-1, could enable clinicians to stratify patient risk, guide personalized neuroprotective therapies, and monitor therapeutic responses over time.
Important scientific and clinical limitations must be considered when translating these mechanistic insights into neonatal practice. Most available data are derived from rodent and large-animal experimental models, which do not entirely replicate the complex clinical scenarios, variable gestational ages, maternal comorbidities, and distinct timing of insults observed in human neonates. Furthermore, because metabolic, immune, and endocrine pathways exhibit extensive bidirectional cross-talk, determining the independent causative contributions of individual pathways to tertiary-phase injury remains exceptionally challenging. Additionally, high-resolution technologies like single-cell transcriptomics and spatial profiling face practical barriers in neonatal medicine, including scarce postmortem human brain tissue, sample heterogeneity, and high technical costs. Addressing these limitations will require reductionist preclinical designs that isolate specific neuroimmune and endocrine pathways, alongside prospective clinical studies validating integrated biomarker panels and exploring multitarget, mechanistically complementary therapeutic combinations centered on preserving mitochondrial bioenergetics.
Subject of Research: Pathophysiological mechanisms and neuroprotective targets in perinatal asphyxia
Article Title: Neuroimmune-endocrine interactions in perinatal asphyxia: from brain injury to neuroprotection
Article References: Capani, F. (2026). Neuroimmune-endocrine interactions in perinatal asphyxia: from brain injury to neuroprotection. Frontiers in Human Neuroscience, 20, Article 2018788. https://doi.org/10.3389/fnhum.2026.2018788
Image Credits: AI Generated
DOI: 10.3389/fnhum.2026.2018788
Keywords: perinatal asphyxia, hypoxic-ischemic encephalopathy, brain energy failure, mitochondrial dysfunction, neuroinflammation, neuroprotection, palmitoylethanolamide, therapeutic hypothermia, Neuroimmune-endocrine, interactions, perinatal, asphyxia
News Source: Cassandra Pierce. (November 7, 2026). Brain Energy Failure Framework Unifies Cellular Damage in Perinatal Asphyxia. Scienmag.