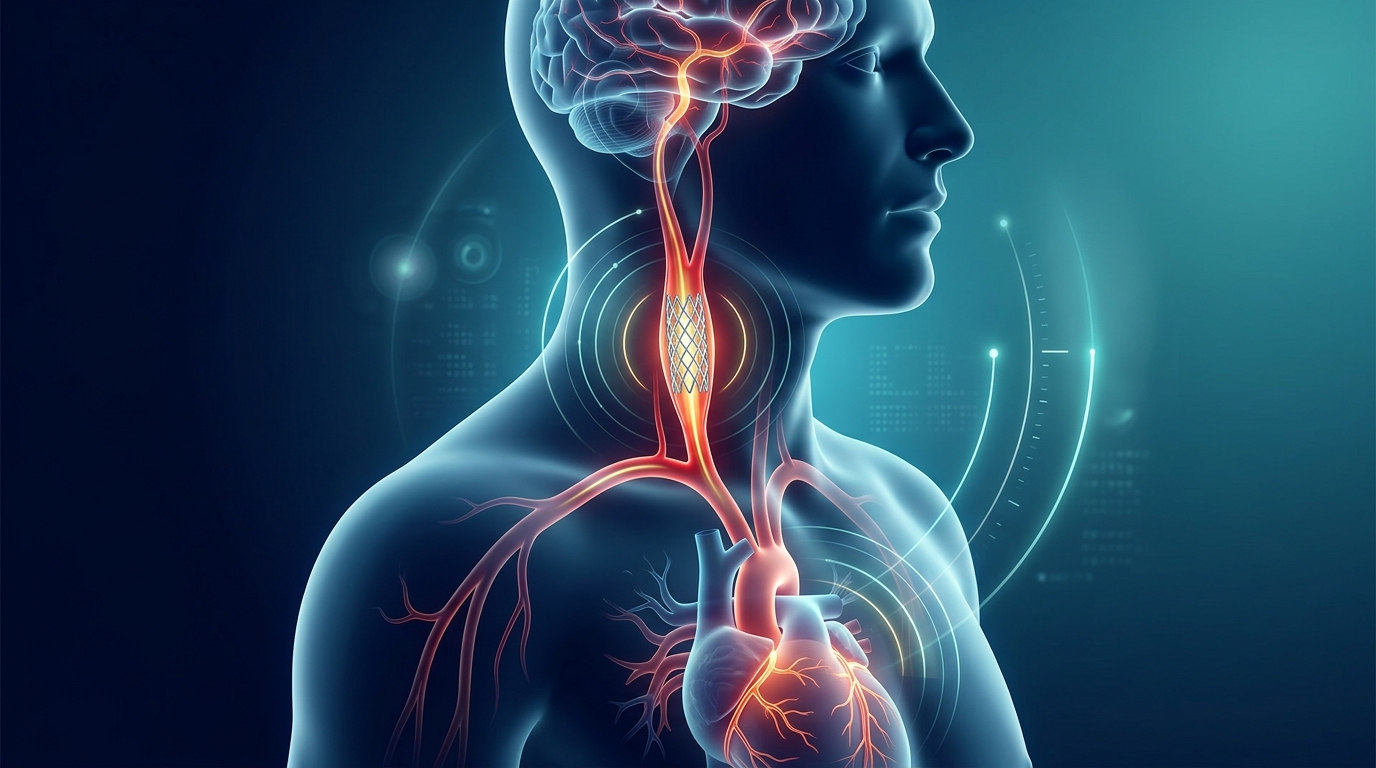
Patients with severe narrowing in the carotid or vertebral arteries who need coronary artery bypass grafting face a difficult sequencing question: should the neck arteries be reopened during the same hospital admission as the heart operation, or weeks beforehand? A single-center retrospective cohort study from Beijing Anzhen Hospital, Capital Medical University, now offers some of the most detailed evidence yet on how that choice plays out in practice. Across 801 adults treated between January 2011 and December 2025, the risk of perioperative death or stroke did not differ significantly between patients who underwent percutaneous cervicocerebral artery revascularization, known as PCAR, at the same time as bypass surgery and those whose procedures were staged. Yet the study’s most striking signal emerged among staged patients operated on within a week of their stenting procedure, who carried the highest estimated odds of the composite endpoint relative to the concomitant group.
The research, published in Cardiology and Therapy, addressed a genuine gap in surgical practice. Combined carotid and coronary revascularization has been performed for more than five decades, and approaches have evolved from concomitant or staged carotid endarterectomy with bypass grafting toward hybrid strategies incorporating percutaneous carotid revascularization before or during the cardiac operation. Evidence guiding the management of severe vertebral artery stenosis in the setting of bypass surgery, however, remains limited. The Beijing team extended previous work by including not only patients with severe carotid artery stenosis but also those with severe vertebral artery disease, and by probing whether the interval between the two procedures influences outcomes among staged patients.
The study population was drawn from roughly 73,000 adults who underwent coronary artery bypass grafting at the institution during the fifteen-year window. All bypass candidates underwent routine duplex ultrasonographic screening of the carotid and vertebral arteries, and patients with suspected stenosis were further evaluated by cervicocerebral computed tomography angiography. Severe stenosis was defined as 70 percent or greater, and the decision to revascularize was made through multidisciplinary evaluation led by neurologists, weighing neurologic symptoms, stenosis severity, vascular anatomy, and overall procedural risk. Patients who had undergone previous cardiac surgery or required additional cardiac procedures such as valve repair or replacement were excluded, as were the 67 patients treated with carotid endarterectomy combined with bypass grafting during the same period.
Of the 801 patients included, 57, or 7.1 percent, underwent concomitant intervention, while 744, or 92.9 percent, had staged procedures. The median interval between PCAR and bypass surgery in the staged cohort was 30 days, with an interquartile range of 9 to 46 days. PCAR was performed for severe vertebral artery stenosis in 221 patients, or 27.6 percent, for severe carotid artery stenosis in 474 patients, or 59.2 percent, and for both in 106 patients, or 13.2 percent. The mean age of the cohort was 65.5 years, with 16.5 percent women. Hypertension was present in 70.4 percent, diabetes mellitus in 46.7 percent, hyperlipidemia in 63.9 percent, peripheral artery disease in 14.6 percent, and prior stroke in 19.1 percent. Fifteen patients, or 1.9 percent, had non-ST-segment elevation myocardial infarction as the principal admission diagnosis, and none had ST-segment elevation myocardial infarction.
The primary endpoint was a composite of perioperative death or stroke, with stroke defined as a new focal or global neurologic deficit lasting more than 24 hours and confirmed by brain computed tomography or magnetic resonance imaging. Neuroimaging was performed only when stroke was clinically suspected, not routinely in asymptomatic patients. Overall, the composite outcome occurred in 38 patients, or 4.7 percent, with seven deaths, or 0.9 percent, and 32 strokes, or 4.0 percent. Because the number of events was small and the data showed potential separation, the investigators used Firth penalized logistic regression, a method designed to produce more stable estimates when outcomes are rare. Peripheral artery disease, chronic renal failure, and bypass surgery performed with cardiopulmonary bypass were each associated with a higher risk of the endpoint in univariable analysis.
The head-to-head comparison of strategies yielded a statistically quiet result. Perioperative death or stroke occurred in one patient, or 1.8 percent, of the concomitant group and 37 patients, or 5.0 percent, of the staged group. No deaths occurred among concomitant patients, who experienced one stroke, while the staged group recorded seven deaths and 31 strokes. After multivariable adjustment, concomitant intervention was not significantly associated with the primary endpoint compared with staged intervention, with an adjusted odds ratio of 0.43 and a 95 percent confidence interval of 0.05 to 1.76, and a P value of 0.280. The authors are explicit that this absence of significance should not be read as proof of comparable safety, because the limited number of events substantially reduced statistical power and precluded any conclusion regarding equivalence between the two strategies.
The interval analysis is where the study becomes genuinely provocative. Among staged patients, restricted cubic spline modeling did not identify a statistically significant nonlinear association between the interprocedural interval and the endpoint, but the curve suggested a trend toward lower risk as the interval lengthened. When staged procedures were categorized as 1 to 7, 8 to 30, 31 to 90, or more than 90 days and compared against the concomitant reference group, the endpoint occurred in 10 of 120 patients, or 8.3 percent, in the 1-to-7-day group, 12 of 228, or 5.3 percent, in the 8-to-30-day group, 13 of 344, or 3.8 percent, in the 31-to-90-day group, and 2 of 52, or 3.8 percent, beyond 90 days. Adjusted odds ratio point estimates generally declined across groups with progressively longer intervals, and the 1-to-7-day group had the highest adjusted odds relative to the concomitant group, at an odds ratio of 4.89 with a 95 percent confidence interval of 1.04 to 48.30 and a P value of 0.044. An additional analysis further adjusting for NSTEMI at presentation produced a nearly identical estimate, with an odds ratio of 4.79.
The investigators propose several mechanisms that might explain the early-interval signal, while stressing that these explanations remain speculative. Shortly after stenting, the treated vascular segment may remain biologically vulnerable because of incomplete endothelialization, procedure-related vascular injury, platelet activation, and residual plaque vulnerability, increasing susceptibility to thromboembolic events during the subsequent cardiac operation. Bypass surgery performed soon after PCAR may also expose patients to hemodynamic fluctuations, microembolization related to cardiopulmonary bypass, and transient intraoperative hypotension before cerebral perfusion reserve has stabilized. Antithrombotic management poses a third challenge: when bypass follows stenting within days, dual antiplatelet therapy may need to be interrupted or withheld over bleeding concerns, and bridging with low-molecular-weight heparin may not fully protect against platelet-mediated stent thrombosis. A longer interval, by contrast, may permit vascular stabilization, better antithrombotic management, and recovery from procedure-related inflammatory and hemodynamic stress.
Confounding by indication looms large over this finding. The reasons for selecting a 1-to-7-day interval were not consistently documented, so the team cannot determine whether earlier bypass surgery was prompted by greater clinical urgency, and patients operated on within a week may simply have had more unstable coronary disease or a higher underlying risk profile. Although additional adjustment for NSTEMI did not materially alter the association, a single covariate cannot fully account for differences in urgency or severity, and residual confounding cannot be excluded. The timing of staged intervention was not governed by a prespecified protocol but was determined pragmatically by clinical considerations, procedural scheduling, and patient availability, which may have introduced further bias. The authors therefore frame the interval-specific results as exploratory and hypothesis-generating rather than as evidence that a shorter interval causally increases perioperative risk.
Several further limitations temper the conclusions. Perioperative myocardial infarction was not systematically assessed in the staged group and could not be incorporated into the overall safety comparison, an important omission when weighing concomitant against staged strategies. As a single-center study, institutional differences in procedural technique and perioperative management may limit generalizability, and the retrospective design is inherently susceptible to selection bias. Postoperative neuroimaging was obtained only when stroke was clinically suspected, so clinically silent or subtle cerebral infarctions may have gone undetected, and stroke severity was not graded with validated scales, precluding reliable classification of strokes as minor or major. The distribution of operative urgency could not be reliably determined because it was not systematically recorded. Given the limited number of events and the resulting imprecision of the estimates, the team concludes that large, prospective, multicenter studies with comprehensive perioperative assessment, including myocardial infarction, are needed before these findings can guide clinical practice.
Subject of Research: Timing of percutaneous cervicocerebral artery revascularization relative to coronary artery bypass grafting and the risk of perioperative death or stroke
Article Title: Concomitant Versus Staged Percutaneous Cervicocerebral Artery Revascularization with Coronary Artery Bypass Grafting
Article References: Zhang, J., He, L., Xu, C., Yue, C., Wang, S., Sun, P., Cui, H., Ren, C., & Lai, Y. (2026). Concomitant Versus Staged Percutaneous Cervicocerebral Artery Revascularization with Coronary Artery Bypass Grafting. Cardiology and Therapy, 15(3), 339-350. https://doi.org/10.1007/s40119-026-00465-5
Image Credits: AI Generated
DOI: 10.1007/s40119-026-00465-5
Keywords: coronary artery bypass grafting, carotid artery stenosis, vertebral artery stenosis, percutaneous revascularization, perioperative stroke, staged intervention, concomitant surgery, Firth penalized logistic regression, interprocedural interval, retrospective cohort study, cerebral perfusion, antiplatelet therapy
News Source: Ophelia Keating. (November 4, 2026). Timing of Neck Artery Stents Before Bypass Surgery May Shape Stroke Risk. Scienmag.