Pre-transplant left atrial strain parameters, specifically left atrial reservoir strain and conduit strain, are independently associated with major adverse cardiovascular events following kidney transplantation, according to a retrospective single-center study conducted at Saint Louis University Hospital. Researchers evaluated routine pre-transplant echocardiograms to establish whether myocardial deformation indices of the left atrium could improve post-transplant risk stratification in adult kidney graft recipients.
Cardiovascular disease represents the leading cause of morbidity and mortality among kidney transplant recipients. These vulnerable individuals experience heightened cardiovascular vulnerability driven by both traditional risks and unique factors related to end-stage kidney disease and immunosuppressive regimens, yet standard clinical risk scores and conventional imaging techniques exhibit suboptimal accuracy in predicting post-transplant cardiovascular complications.
The left atrium plays a fundamental role in cardiac hemodynamics, serving as a sensitive indicator of left ventricular compliance and diastolic performance. Although left atrial volume tends to increase with advancing age, left atrial emptying fraction typically remains stable. In the presence of elevated filling pressures, myocardial damage, infiltrative disorders, and arrhythmogenic stimuli, the chamber undergoes structural and functional remodeling. In normal sinus rhythm, atrial function comprises three distinct phases: reservoir function during ventricular systole, conduit function transferring pulmonary venous blood during early ventricular diastole, and booster pump or contractile function that augments ventricular filling during late diastole.
To investigate atrial deformation in this clinical population, the investigators reviewed records for adult kidney transplant recipients who received transplants between January 1, 2015, and December 31, 2023, and possessed pre-transplant transthoracic echocardiograms in the institutional archives. The pre-transplant imaging had been acquired during standard pre-transplant evaluations, at an average interval of 5.2 ± 2.9 months prior to transplantation. Patients were excluded if they were not in sinus rhythm during echocardiography or if acoustic image quality was inadequate for wall tracking. Out of 518 patients undergoing kidney transplantation, 377 met inclusion criteria, comprising a cohort that was 56.7 percent male with an overall mean age of 53.7 ± 13.1 years.
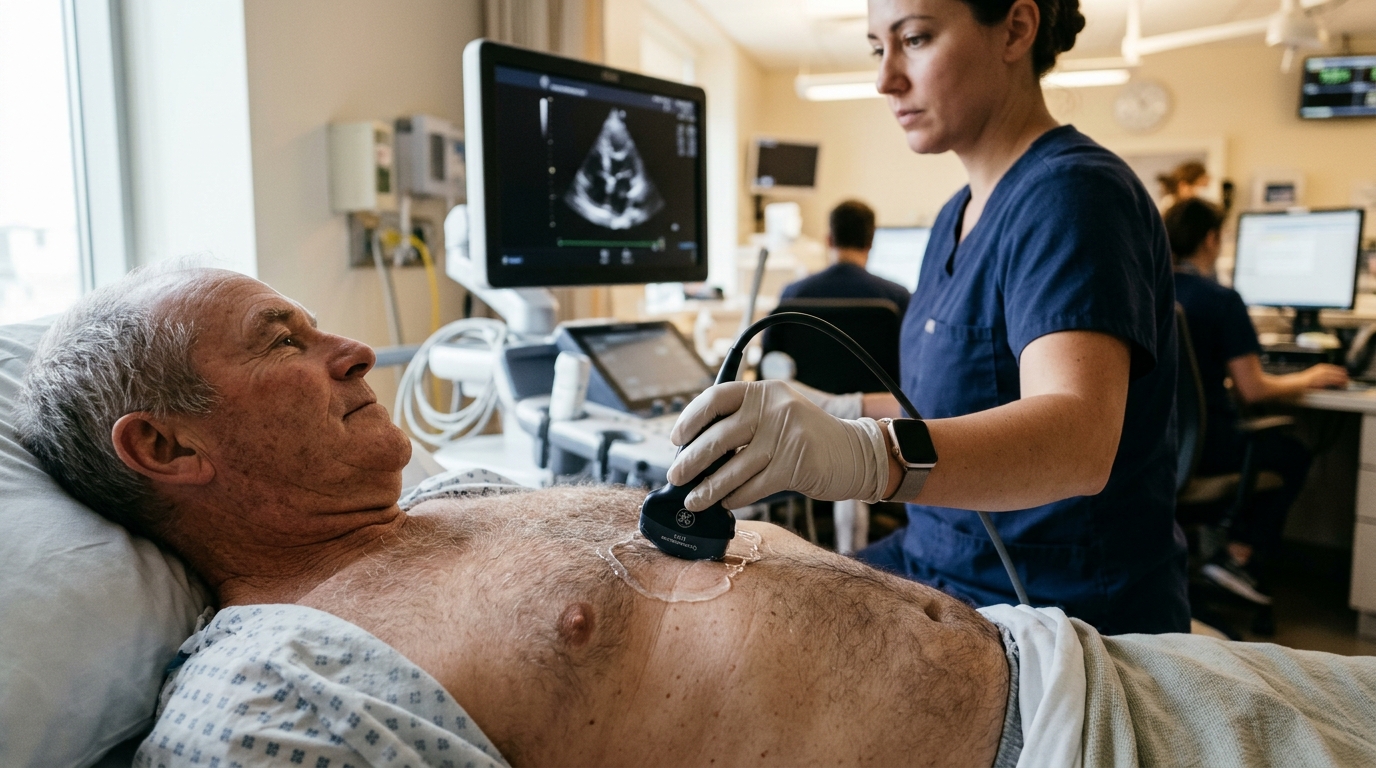
Echocardiographic strain measurements were conducted using vendor-independent speckle-tracking software from TomTec Imaging Systems across apical four-chamber and two-chamber views. Endocardial borders were traced automatically and manually adjusted when necessary to ensure accurate tracking, with strain components calculated by averaging values from both views. To ensure measurement consistency, twelve investigators underwent standardized training directed by the principal investigator, who had completed an advanced cardiac imaging fellowship. Each reader was required to achieve at least 80 percent agreement on a preselected ten-patient sample before contributing to the study, yielding an overall intraclass correlation coefficient for strain of 0.96 with a 95 percent confidence interval of 0.90 to 0.99 under blinded conditions.
Left atrial volumetric analysis was performed utilizing the biplane area–length method, calculating volumes as 0.848 multiplied by the four-chamber area and two-chamber area, divided by the average length across both views. Maximum, minimum, and pre-atrial-contraction volumes were indexed to body surface area. Left atrial ejection fraction was defined as maximum volume minus minimum volume divided by maximum volume, whereas the atrial expansion index was calculated as maximum volume minus minimum volume divided by minimum volume.
The study’s primary endpoint was the occurrence of major adverse cardiovascular events, defined as cardiovascular death, nonfatal myocardial infarction, unstable angina hospitalization, heart failure hospitalization, ischemic stroke, or fatal arrhythmias, with patient follow-up documented through March 2025. Events were extracted from hospital medical records and adjudicated by senior internal medicine residents. Adjudicators applied specific scrutiny to heart failure hospitalizations to verify that the primary admission diagnosis and therapeutic management—including decongestion and guideline-directed medical therapy—were aimed directly at heart failure rather than alternative diagnoses such as pneumonia or chronic obstructive pulmonary disease exacerbation.
Over a mean follow-up duration of 5.3 ± 2.3 years following kidney transplantation, 82 patients, representing 22 percent of the analyzed cohort, reached the composite cardiovascular endpoint. Compared to recipients who remained event-free, patients experiencing adverse events were significantly older, averaging 56.0 ± 12.2 years versus 52.2 ± 13.3 years, and had a higher proportion of Black recipients at 59.8 percent versus 44.5 percent. Patients with cardiovascular events also demonstrated higher baseline frequencies of diabetes mellitus at 46.1 percent versus 34.1 percent, coronary artery disease at 48.5 percent versus 25.1 percent, and previous cerebrovascular events at 7.8 percent versus 2.9 percent, alongside longer pre-transplant dialysis duration of 56.7 ± 40.7 versus 44.2 ± 35.5 months, higher glycated hemoglobin of 5.9 ± 1.2 versus 5.5 ± 0.9 percent, and higher baseline troponin of 1.5 ± 7.3 versus 0.1 ± 0.3.
Baseline echocardiograms demonstrated that all three left atrial strain components were significantly lower among patients who subsequently developed major cardiovascular complications. Aortic valve regurgitation severity also differed between groups, showing higher rates of mild regurgitation and fewer instances of trace or absent regurgitation among patients experiencing events. In contrast, left ventricular ejection fraction did not differ significantly between the event and non-event cohorts.
Kaplan–Meier survival analysis demonstrated significantly lower event-free survival in patients exhibiting abnormal strain values across all three components, based on established thresholds of 39 for reservoir strain, 22 for conduit strain, and 17 for contractile strain. When stratified specifically by normal versus abnormal reservoir strain, patients with abnormal values experienced significantly higher cumulative incidences of adverse cardiovascular events at one, three, and five years following transplantation.
In multivariable Cox proportional hazards regression models adjusted for age, gender, left ventricular ejection fraction, and univariate confounding variables entered individually to prevent collinearity, strain parameters displayed independent prognostic value without violating proportional hazards assumptions. Lower left atrial conduit strain was independently associated with adverse outcomes with a hazard ratio of 0.94 and 95 percent confidence interval of 0.89 to 0.98, while lower reservoir strain remained independently predictive with a hazard ratio of 0.97 and 95 percent confidence interval of 0.94 to 0.995. Contractile strain and left atrial volumetric parameters were not independently associated with post-transplant cardiovascular events in adjusted models.
The authors observed that left ventricular ejection fraction was not predictive of adverse outcomes, likely because the vast majority of study subjects had preserved systolic function, reducing discriminatory variation, while ejection fraction remains load-dependent, insensitive to subclinical diastolic impairment, and subject to post-transplant reversal of uremic cardiomyopathy. Several study limitations were noted, including the single-center retrospective design, potential undercounting of events occurring at outside institutions, lack of data on mitral stenosis severity, subtle measurement variability across multiple readers despite high reliability scores, and the potential presence of unmeasured residual confounding, indicating that external validation is warranted before clinical implementation.
Subject of Research: Echocardiographic left atrial strain and cardiovascular outcomes in kidney transplant recipients
Article Title: Association of left atrial volume and function parameters with cardiovascular outcomes following kidney transplantation
Article References: DeLonais-Parker, A. R., Hobbs, S. H., Coffman, T. R., Kanan, M. F., Lyu, Y., Treiber, E. J., Mansuri, R. F., Okeke, B. C., Lentine, K. L., & Benjamin, M. M. (2026). Association of left atrial volume and function parameters with cardiovascular outcomes following kidney transplantation. Cardiovascular Ultrasound, 24(1), Article 7. https://doi.org/10.1186/s12947-026-00369-3
Image Credits: AI Generated
DOI: 10.1186/s12947-026-00369-3
Keywords: kidney transplantation, left atrial strain, echocardiography, cardiovascular outcomes, major adverse cardiovascular events, end-stage kidney disease, speckle tracking echocardiography, cardiac remodeling, Association, left, atrial, volume
News Source: Ophelia Keating. (November 6, 2026). Left Atrial Strain Predicts Cardiovascular Events Following Kidney Transplantation. Scienmag.