Patients facing surgery for large bladder tumors may benefit from a preparatory step that shrinks the tumor’s blood supply before the scalpel, or rather the resectoscope, ever enters the bladder. The findings, published in CVIR Endovascular, come from a propensity score–matched comparison designed to iron out the baseline differences that have muddied earlier attempts to evaluate this approach.
The procedure in question, transurethral resection of bladder tumor, or TURBT, is the gold standard for diagnosing and treating early-stage bladder cancer. Bladder cancer itself is the most common malignant tumor of the urinary system and a major public health burden. But when a tumor grows large, the operation becomes technically demanding. Bleeding can cloud the surgical field through the endoscope, prolonging the procedure and making it harder to remove the tumor completely. Prolonged operative time is not a trivial inconvenience: it has been associated with a higher incidence of perioperative complications, including urinary tract infection, sepsis, pulmonary embolism, myocardial infarction, and increased mortality. A diameter of three centimeters or more has been used to define large tumors in non–muscle-invasive bladder cancer risk stratification and in prior studies of preoperative embolization, so the research team adopted that threshold.
The idea behind preoperative embolization borrows from established interventional radiology practice. Selective arterial embolization occludes tumor-feeding arteries with embolic particles, reducing tumor vascularity and perioperative bleeding. Urologists and interventional radiologists already use the technique to manage large hypervascular renal masses and to shrink the prostate before surgery for benign prostatic hyperplasia. Several studies have tested preoperative embolization before TURBT, but the authors of the new report argue that the evidence base has been uneven: earlier cohorts were selected by tumor stage or VI-RADS score, comparative groups differed substantially in tumor size at baseline, and small uncontrolled series focused on very large tumors. The interval between embolization and resection also varied from study to study, and embolization-related adverse events were inconsistently reported.
Timing was a central design consideration. Post-embolization syndrome, a constellation of fever, nausea, abdominal pain, and fatigue, typically occurs within 24 to 72 hours after embolization and can interfere with subsequent surgery. In the investigators’ clinical experience, clinically relevant symptoms such as fever and nausea tended to appear more than 24 hours after the procedure. That observation motivated their choice of a tight window: every patient in the embolization arm underwent TURBT within 24 hours of the embolization, ideally capturing the hemostatic benefit before post-embolization symptoms could disrupt the surgical workflow.
The study screened 86 patients with pathologically confirmed bladder tumors measuring at least three centimeters who underwent TURBT between 2020 and 2025 at a single center. Eleven were excluded, including four with abnormal coagulation function, four with concomitant prostate cancer or metastatic disease, one who had another procedure during TURBT, one with an unclear pathological diagnosis, and one in whom super-selective catheterization failed. That left 75 patients: 27 who received embolization followed by TURBT within 24 hours, and 48 who underwent TURBT alone. The decision to embolize was made jointly by a urologist and an interventional radiologist, primarily when substantial bleeding or difficulty achieving hemostasis was anticipated. All resections were performed by urologists with more than five years of endoscopic bladder tumor experience, and all embolizations by a single interventional radiologist with more than a decade of endovascular experience.
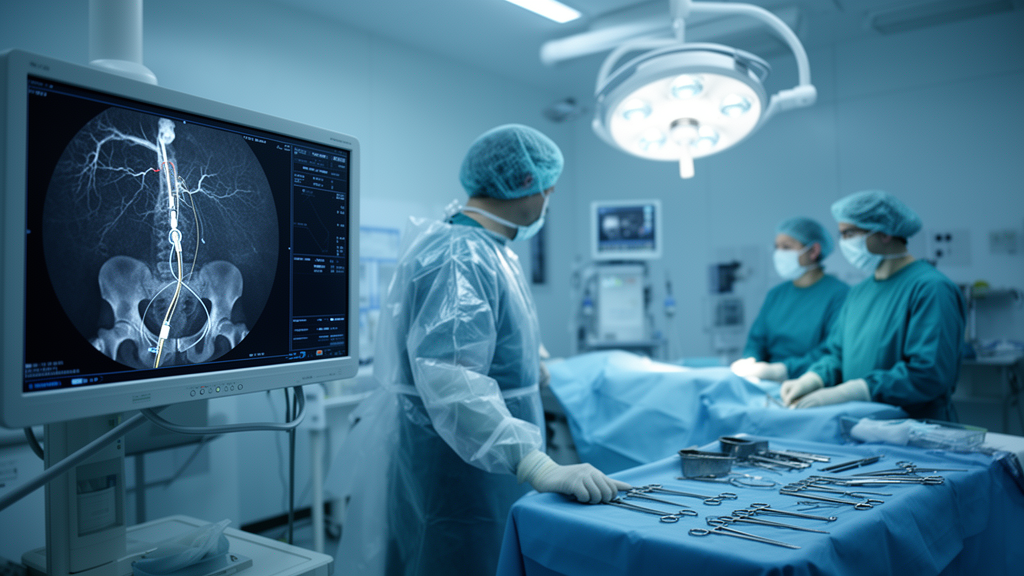
The embolization technique itself was meticulous. After reviewing preoperative contrast-enhanced CT to map the tumor, the radiologist punctured the femoral artery under local anesthesia and performed bilateral internal iliac artery angiography to identify the vessels feeding the tumor. A microcatheter was then advanced super-selectively into the superior and inferior vesical arteries. Most patients received 100 to 300 micrometer Embosphere microspheres, with larger particles added in some cases depending on vessel caliber and residual tumor staining. The endpoint was near-complete disappearance of tumor staining on completion angiography, and the puncture site was closed with a vascular closure device. Among 28 patients in whom embolization was attempted, 27 succeeded, a technical success rate of 96.4 percent; the single failure, a case of unsuccessful super-selective catheterization, was excluded from the comparative analysis.
One-to-one nearest-neighbor matching without replacement, with a caliper of 0.2 standard deviations of the propensity score logit, produced 17 matched pairs. Before matching, tumor size differed significantly between the groups; after matching, most covariates showed improved balance, although sex retained a marginal residual imbalance with a standardized mean difference of 0.209, just above the 0.2 threshold the authors considered acceptable.
The matched comparison favored the embolization group across every perioperative measure the study examined. Estimated intraoperative blood loss was 68.03 milliliters (interquartile range 56.68 to 75.50) versus 101.96 milliliters (93.62 to 116.67) in the TURBT-alone group, a statistically significant difference with P equal to 0.005. The perioperative decrease in hemoglobin was also smaller, 0.66 versus 1.08 grams per deciliter (P = 0.003). Operation time was roughly 20 minutes shorter, 60.00 versus 80.00 minutes (P = 0.009). Postoperative hospital stay was 7 versus 8 days (P = 0.035), and urinary catheterization duration was 6 versus 8 days (P = 0.009). No patient in the embolization group required a blood transfusion, while one patient, 5.9 percent of the matched TURBT-alone group, did.
The authors are candid that the absolute differences are modest. The hematocrit-based formula used to estimate blood loss provides only an indirect measure, which is why they also reported the hemoglobin decline as corroborating evidence. A 20-minute reduction in operative time and a modestly smaller estimated blood loss alone, they write, may not justify preoperative embolization; the case rests on the combination of reduced bleeding, shorter hospitalization, shorter catheterization, and potentially reduced procedural risk, benefits they suggest may matter most for patients in poor general condition or with an anticipated high risk of perioperative bleeding.
Safety data add necessary nuance. Among the 27 successfully embolized patients, six experienced embolization-related complications, with some overlapping events: bladder spasm in four patients (14.8 percent), fever in three (11.1 percent), and hematuria in two (7.4 percent). Graded by the modified CIRSE classification system, two patients had grade 2 complications and three had grade 3a complications, including one case of glans skin ischemic necrosis that the authors attributed to reflux of oversized embolic particles into adjacent arterial branches; it improved with conservative treatment and required no additional intervention. No grade 3b to 6 complications occurred, and no puncture-site bleeding was observed. Cystoscopic and histopathologic observations supported the mechanism: embolized tumors appeared pale with reduced vascularity, and their boundaries were more clearly distinguishable from surrounding mucosa, though the authors note this assessment was qualitative and lacked a standardized scoring system.
The limitations are substantial and the authors state them plainly. This was a retrospective, single-center study in which treatment allocation rested on clinical judgment rather than randomization, so selection bias and residual or unmeasured confounding cannot be excluded despite the matching. The sample was small, particularly after matching, limiting statistical power and making perfect covariate balance unattainable. The study captured only short-term perioperative outcomes; long-term oncological outcomes such as recurrence, progression, repeat resection findings, and bladder-preservation results were not fully assessed. Operator-related variation and incomplete recording of procedural details also cannot be ruled out. The authors call for multicenter prospective studies to validate the sequential strategy and to evaluate its broader value, including cost-effectiveness and patient-reported outcomes such as postoperative pain, recovery speed, and quality of life. Until then, the study stands as suggestive comparative evidence, not proof, that for selected patients with bladder tumors of three centimeters or more, embolizing the tumor’s blood supply a day before resection can make a difficult operation gentler.
Subject of Research: Preoperative bladder artery embolization before transurethral resection of large bladder tumors
Article Title: Preoperative bladder artery embolization before transurethral resection of large bladder tumors: a propensity score–matched retrospective cohort study
Article References: Gu, C., Li, J., Zheng, H., Zhang, Z., Xu, H., Zhang, Z., Shen, G., & Cheng, L. (2026). Preoperative bladder artery embolization before transurethral resection of large bladder tumors: a propensity score–matched retrospective cohort study. CVIR Endovascular, 9(1), Article 134. https://doi.org/10.1186/s42155-026-00779-4
Image Credits: AI Generated
DOI: 10.1186/s42155-026-00779-4
Keywords: bladder cancer, TURBT, arterial embolization, interventional radiology, propensity score matching, perioperative outcomes, blood loss, surgical time, post-embolization syndrome, urologic surgery, retrospective study, vesical arteries
News Source: Ophelia Keating. (October 28, 2026). Bladder Artery Embolization Before Tumor Resection Cuts Bleeding and Surgery Time. Scienmag.