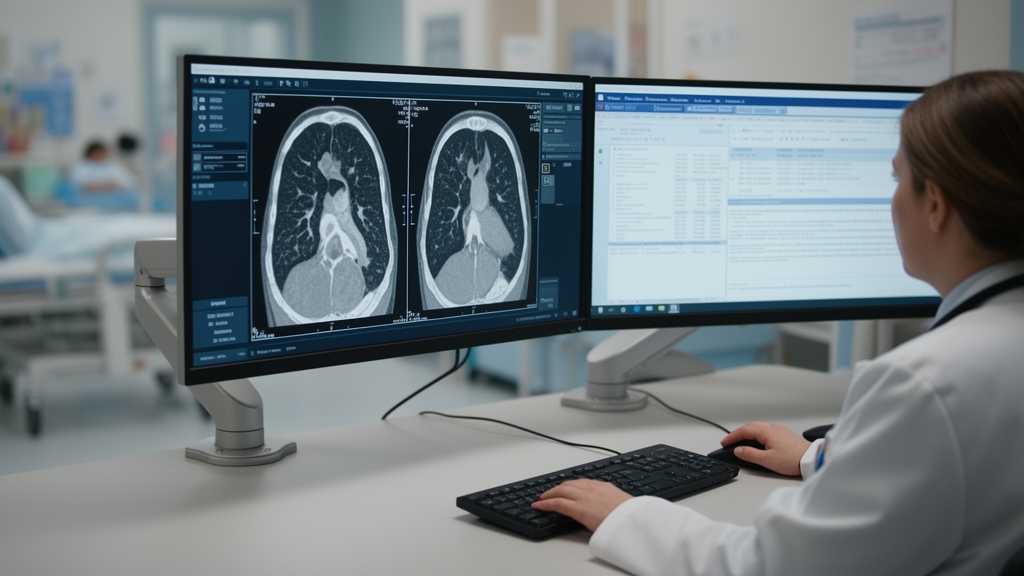
A retrospective study of 364 children hospitalized with severe pneumonia found that a machine-learning model combining chest CT features with electronic medical records performed best at identifying concurrent respiratory failure. The Random Forest model achieved an area under the receiver operating characteristic curve of 0.893 in the training dataset and retained the strongest discrimination in a separate validation set, outperforming Support Vector Machine and Gradient Boosting Machine alternatives. The findings support the combined model as a potential risk-screening tool for this hospitalized pediatric population, although the study did not test whether use of the predictions improves clinical decisions or patient outcomes.
Children in the study were admitted to the pediatric department of one hospital between January 2020 and February 2024. Researchers randomly divided the cohort into a training set of 255 patients and a validation set of 109, producing a 7:3 split. The inputs comprised 20 indicators drawn from demographic information, clinical test results, imaging features and text contained in electronic medical records. Baseline characteristics did not differ significantly between the two subsets, according to the reported analysis with P values greater than 0.05.
The analysis proceeded in stages. Candidate predictors were first screened through univariate analysis, after which feature dimension was reduced with least absolute shrinkage and selection operator, or LASSO, regression. Multivariable logistic regression then identified factors independently associated with respiratory failure occurring alongside severe pneumonia. Seven variables met the study’s threshold of P less than 0.05: fraction of inspired oxygen, C-reactive protein, serum lactate, the number of affected lung lobes, entropy of the gray-level co-occurrence matrix, contrast of the gray-level run-length matrix, and the absolute value of first-order statistical skewness. The first three were clinical measurements, while the final four were CT-derived variables.
Based on the combined data, the researchers constructed Random Forest, Support Vector Machine and Gradient Boosting Machine prediction models. Their performance was evaluated with the area under the receiver operating characteristic curve, sensitivity and specificity. In the training set, Random Forest produced the highest AUC at 0.893, with a 95% confidence interval of 0.826–0.961. The corresponding AUC was 0.836 for Support Vector Machine, with a 95% confidence interval of 0.756–0.916, and 0.854 for Gradient Boosting Machine, with a 95% confidence interval of 0.783–0.924. Random Forest also maintained the best discriminative performance in the validation set, although the supplied abstract does not provide the numerical AUC, sensitivity or specificity for that subset. DeLong tests found a statistically significant difference between Random Forest and Support Vector Machine at P = 0.018, and between Random Forest and Gradient Boosting Machine at P = 0.042.
The analysis highlighted the contrast of the gray-level run-length matrix, entropy of the gray-level co-occurrence matrix, the absolute value of first-order statistical skewness and the number of affected lung lobes as core early-warning factors. Together with fraction of inspired oxygen, C-reactive protein and serum lactate, these variables formed a compact set of laboratory, oxygenation and imaging predictors identified in the multivariable analysis. The reported results show that fusing CT and electronic medical-record information yielded useful discrimination within this retrospective cohort, but important limitations constrain broader interpretation. The study included children already hospitalized at a single institution, used a validation set of 109 patients, and did not report external validation, calibration, decision thresholds or missing-data handling in the supplied abstract. It also assessed prediction of concurrent respiratory failure rather than whether acting on the model would enable earlier intervention. The article supplied for this report is an early, editable version subject to replacement by the final Version of Record.
Subject of Research: Retrospective prediction of concurrent respiratory failure in children hospitalized with severe pneumonia using combined CT and electronic medical-record data
Article Title: Prediction of respiratory failure in severe pediatric pneumonia via CT and electronic medical records fusion
Article References: Huang, C., & Zhang, N. (2026). Prediction of respiratory failure in severe pediatric pneumonia via CT and electronic medical records fusion. BMC Pediatrics. https://doi.org/10.1186/s12887-026-07599-4
Image Credits: AI Generated
DOI: 10.1186/s12887-026-07599-4
Keywords: pediatric pneumonia, respiratory failure, chest CT, electronic medical records, machine learning, Random Forest, risk prediction, medical imaging, retrospective study, Prediction, respiratory, failure
News Source: Harold Sullivan. (October 22, 2026). Prediction of respiratory failure in severe pediatric pneumonia via CT and electronic medical records fusion. Scienmag.