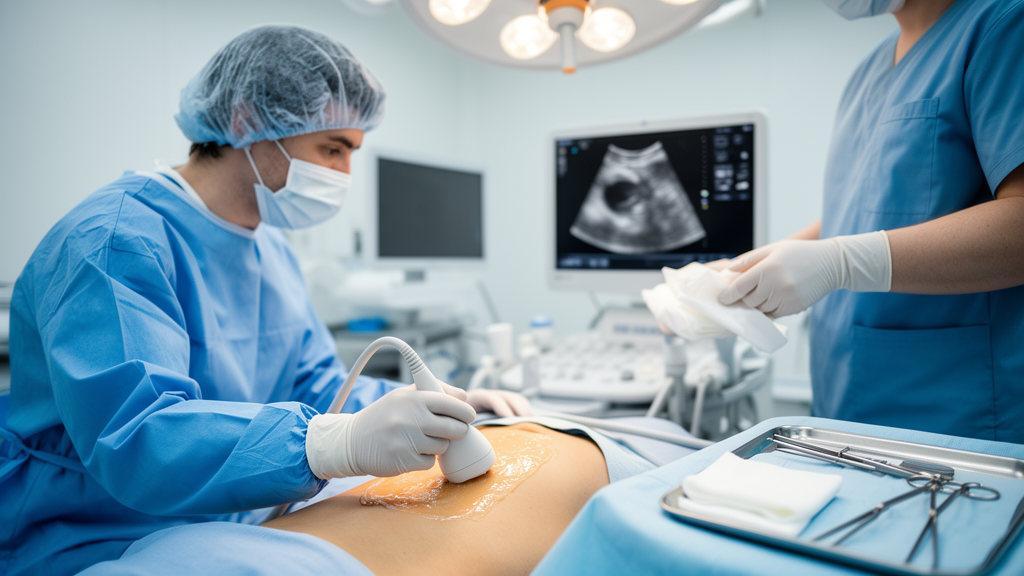
Interventional ultrasound has quietly transformed modern medicine, allowing physicians to biopsy tumors, drain abscesses, sclerose cysts, and ablate cancers through incisions so small they barely merit a bandage. But the same needle-guided precision that makes these procedures so attractive carries an inherent danger that has long lacked a unified global answer: bleeding. Now, in a landmark effort published in BMC Medicine, an international panel of 51 specialists from six countries has delivered the first systematic expert consensus statement dedicated entirely to the prevention and management of bleeding complications in interventional ultrasound, offering clinicians a standardized, evidence-based framework for one of the most feared adverse events in minimally invasive care.
The significance of this consensus lies in what it replaces: a patchwork of institutional habits, fragmented society guidelines, and anecdotal practice. As interventional ultrasound has expanded from simple core-needle biopsies to complex tumor ablations, percutaneous transhepatic biliary drainage, and sclerotherapy of vascular malformations, the range of bleeding risks has widened dramatically. Severe hemorrhage, though uncommon, can be life-threatening and can undo the very benefits that minimally invasive approaches promise. Until now, no international consensus existed to guide clinicians through risk assessment, prevention, monitoring, and rescue management across this rapidly growing procedural landscape.
The rigor behind the document is notable. The development process followed the World Health Organization Handbook for Guideline Development, was reported in accordance with the Reporting Items for Practice Guidelines in Healthcare (RIGHT) statement, and was independently appraised using the AGREE II instrument, a validated tool for judging guideline quality. Evidence quality was graded with the GRADE approach, the international standard for rating the certainty of evidence behind clinical recommendations. To distill disagreement into agreement, the panel employed a two-round modified Delphi process, an iterative voting technique that allows large groups of experts to converge on consensus statements while minimizing the influence of any single dominant voice. The result is a set of 20 finalized recommendations spanning the entire arc of patient care.
At the heart of the consensus is a dual classification system for bleeding complications, organized simultaneously by time of onset and by severity. This dual axis is more than taxonomy; it is designed to standardize clinical communication and decision-making. A hemorrhage that declares itself on the table demands a different response than one that smolders and presents hours later, and a grading scheme that separates minor oozing from catastrophic intra-abdominal bleeding allows teams to escalate care along a shared mental model. Standardized classification also enables meaningful comparison across studies and institutions, something the field has historically lacked because bleeding events were defined inconsistently from one trial to the next.
Equally central is a multidimensional pre-procedural risk assessment that moves far beyond the traditional single-number approach of checking a platelet count and an international normalized ratio. The consensus directs clinicians to weigh procedural risk, meaning the inherent hemorrhagic danger of the specific intervention; patient-related factors, including coagulation status, comorbidities, and antithrombotic medications; lesion characteristics, such as vascularity and depth; device-related factors, including needle caliber and ablation modality; and operator experience, an often-overlooked variable that robust evidence links to complication rates. By forcing a structured evaluation across all five domains, the framework aims to identify high-risk scenarios before the first incision rather than after the first complication.
The recommendations then extend into individualized periprocedural management, addressing one of the thorniest questions in interventional practice: how to handle anticoagulant and antiplatelet therapy. Patients on these medications are increasingly common, and the balance between withholding drugs and risking thromboembolism versus continuing them and risking hemorrhage is genuinely difficult. The consensus emphasizes tailoring periprocedural strategies to the individual patient and procedure rather than applying rigid rules, reflecting the reality that a liver biopsy in a patient on dual antiplatelet therapy is a very different proposition from a superficial thyroid fine-needle aspiration.
After the procedure, the statement introduces risk-adapted ultrasound surveillance, another departure from one-size-fits-all practice. Low-risk patients may require little more than brief observation, while those who underwent high-risk procedures or carry patient-specific risk factors warrant closer monitoring, potentially with color Doppler flow imaging and contrast-enhanced ultrasound, techniques that can detect active extravasation and expanding hematomas at the bedside without ionizing radiation. The principle is that vigilance should be proportional to risk, concentrating resources where they are most likely to change outcomes and catching delayed bleeding before it becomes hemodynamic collapse.
Perhaps the most clinically actionable portion of the consensus is its stepwise hemostatic management algorithm, which escalates from the simplest measures to the most invasive. Local compression remains the first response to accessible bleeding, followed by tract embolization, in which the needle track itself is occluded to stop persistent oozing along the puncture route. When these measures fail, the framework contemplates selected ultrasound-guided interventions, then transarterial embolization, in which interventional radiologists catheterize the feeding vessel under digital subtraction angiography and occlude it, and finally surgery as the definitive rescue option. This graduated pathway gives clinicians a clear sequence of escalation, reducing hesitation and delay, the two factors most consistently associated with poor outcomes in major hemorrhage.
The authors are candid about the limits of their work. The available evidence across interventional ultrasound procedures remains heterogeneous, with robust randomized trial data abundant for some interventions and sparse for others, and some recommendations rest partly on expert opinion where high-quality direct evidence is limited. The panel also stresses that the framework is intended to guide rather than dictate, allowing individualized application according to procedural characteristics, patient-related risk factors, operator experience, and institutional resources. A small hospital without 24-hour angiography suites will apply the escalation pathway differently from a tertiary referral center, and the consensus explicitly accommodates that reality rather than pretending it away.
What emerges is a document with the potential to reshape daily practice across radiology suites, ultrasound departments, and surgical theaters worldwide. By uniting classification, risk assessment, prevention, surveillance, and rescue management under one evidence-graded umbrella, the consensus gives clinicians something they have never had: a shared language and a shared playbook for the complication they fear most. The authors call for further multicenter prospective studies to validate and refine the recommendations, and such research is likely to follow now that standardized definitions exist to make it possible. For patients, the practical meaning is straightforward: fewer surprises, faster responses, and safer minimally invasive care, delivered with the confidence that comes from global agreement rather than local guesswork.
Subject of Research: International expert consensus on prevention and management of bleeding complications in interventional ultrasound procedures
Article Title: Prevention and management of bleeding complications in interventional ultrasound: an international expert consensus statement
Article References: Prevention and management of bleeding complications in interventional ultrasound: an international expert consensus statement. (n.d.). https://doi.org/10.1186/s12916-026-05315-8
Image Credits: AI Generated
DOI: 10.1186/s12916-026-05315-8
Keywords: interventional ultrasound, bleeding complications, hemostasis, expert consensus, patient safety, GRADE, Delphi process, transarterial embolization, contrast-enhanced ultrasound, anticoagulation, tumor ablation, BMC Medicine
News Source: Ophelia Keating. (October 14, 2026). Global Experts Unveil First Consensus to Stop Deadly Bleeding in Ultrasound Procedures. Scienmag.