Waist-to-height ratio showed the most reliable association with first-time myocardial infarction and all-cause mortality among six body-size indicators in a 28-year study of Swedish men from the automotive industry. After researchers adjusted for traditional cardiovascular risk factors, a one-standard-deviation increase in waist-to-height ratio was associated with a hazard ratio of 1.31 for myocardial infarction and 1.27 for all-cause mortality, although the differences between indicators were described as marginal.
The prospective cohort study began in 1993, when 1,000 randomly selected middle-aged Swedish men took part in a nurse-led health examination. Investigators recorded body measurements, blood pressure readings and fasting blood test results. They subsequently linked the cohort to the national Myocardial Infarction Register, Swedeheart, to identify first-time myocardial infarction and to the Swedish Cause of Death Register for mortality data. Data were collected for 959 men over the 28-year follow-up period.
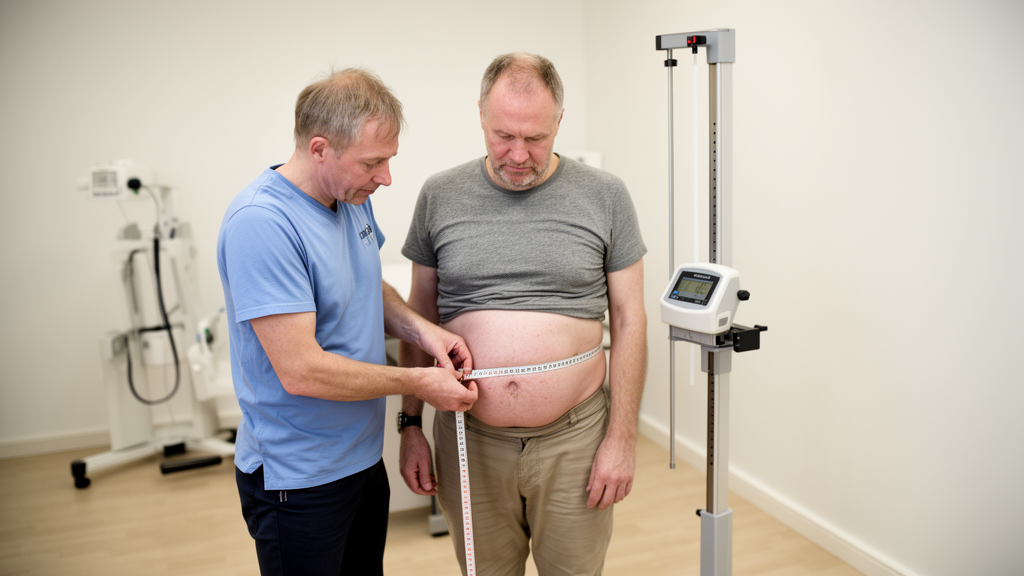
Researchers examined six anthropometric indicators: body mass index, waist circumference, waist-to-height ratio, waist-to-hip ratio, sagittal abdominal diameter, and sagittal abdominal diameter divided by height. They found significant correlations among the measurements, and all six were associated with cardiovascular risk factors, myocardial infarction and mortality. These initial associations did not translate into equally strong relationships after adjustment for traditional cardiovascular risk factors, when associations with cardiovascular endpoints diminished or disappeared for most measures.
The statistical analysis used Cox proportional hazards models and evaluated the z-scores of the six body measurements both before and after adjustment for covariates. Waist-to-height ratio was the indicator that retained the clearest reported relationships with the two outcomes. For myocardial infarction, its adjusted hazard ratio was 1.31, with a 95% confidence interval of 1.07–1.62. For all-cause mortality, the adjusted hazard ratio was 1.27, with a 95% confidence interval of 1.08–1.49. These estimates describe associations within the cohort and do not demonstrate that changes in body size cause either outcome.
Body mass index was expressed in kilograms per square metre, with the study background identifying a BMI of 25–30 as overweight and 30 or above as obesity. Although body mass index and the other five measures were correlated, their value as indicators of cardiovascular outcomes was not identical. Waist-to-height ratio emerged as more reliable in this population, while the authors cautioned that its comparative clinical significance was marginal and noted that there is currently no consensus on a preferred obesity indicator for cardiovascular risk prediction.
The findings therefore distinguish between the initial evidence and the adjusted results. Before accounting for traditional risk factors, every indicator was associated with myocardial infarction and mortality. After adjustment, the relationships for most indicators weakened or were no longer present, while waist-to-height ratio continued to be associated with both outcomes. The reported confidence intervals quantify uncertainty around the adjusted hazard ratios, and the study does not establish that waist-to-height ratio is superior in every population or for every clinical purpose.
The scope of the evidence is important. Participants were middle-aged Swedish men drawn from an occupational setting, and their examination took place at a single point in 1993. The analysis then followed the cohort for 28 years through national registers. Because the research population was specific, the results characterize associations in this group of Swedish automotive-industry male workers rather than establishing a universal relationship for all adults, women or other occupational and geographic populations.
Within those boundaries, the study offers a technically focused comparison of six ways of measuring body size against long-term cardiovascular and mortality outcomes. Its central result is not that waist-to-height ratio was definitively the “best” measure, but that it was the more reliable indicator after adjustment in this cohort, with modest differences between indicators. The authors concluded that waist-to-height ratio proved more reliable for myocardial infarction and mortality in this population while acknowledging the marginal clinical significance of the comparative differences.
Subject of Research: Associations of six body-size indicators with myocardial infarction and mortality in Swedish automotive-industry men
Article Title: Six anthropometric indicators and their associations with myocardial infarction and death in Swedish automotive industry male workers followed for 28 years
Article References: Joulha Ian, L., & Dimberg, L. (2026). Six anthropometric indicators and their associations with myocardial infarction and death in Swedish automotive industry male workers followed for 28 years. BMC Public Health, 26(1), Article 2759. https://doi.org/10.1186/s12889-026-29630-0
Image Credits: AI Generated
DOI: 10.1186/s12889-026-29630-0
Keywords: waist-to-height ratio, myocardial infarction, all-cause mortality, anthropometric indicators, body mass index, cardiovascular risk factors, prospective cohort, Swedish men, Swedeheart, anthropometric, indicators, associations
News Source: Ophelia Keating. (October 21, 2026). Adjusted waist-to-height ratio linked to heart attack and death in Swedish men. Scienmag.