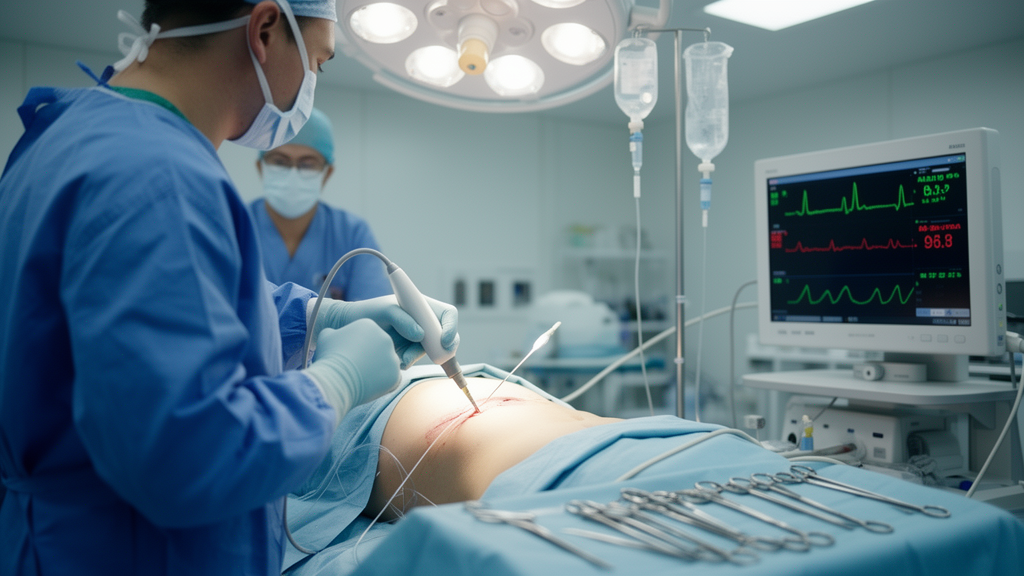
Patients with adrenal tumors face a peculiar danger on the operating table: the very tumors surgeons are removing can flood the bloodstream with hormones that send blood pressure soaring. Now a randomized clinical trial from Shanxi Bethune Hospital in China reports that a simple nerve block, delivered with ultrasound guidance before surgery begins, substantially steadied the cardiovascular rollercoaster. In the study, published in Frontiers in Neuroscience, patients who received a stellate ganglion block before laparoscopic partial adrenalectomy developed intraoperative hypertension at less than half the rate of those who received a sham procedure, 14.3% versus 37.1%, and needed far less intravenous antihypertensive medication during their operations.
The trial enrolled 72 adults aged 18 to 65 with adrenal tumors scheduled for laparoscopic partial adrenalectomy, a minimally invasive operation that removes only the tumor while preserving the remaining functional adrenal cortex. After screening 80 patients, the investigators excluded eight, including three with pheochromocytoma, a hormone-secreting tumor whose removal can trigger dangerous postoperative blood pressure crashes. The remaining participants were randomly assigned in a 1:1 ratio to receive either an ultrasound-guided stellate ganglion block or a sham procedure in which the needle was placed but no anesthetic was injected. One patient in each group was later excluded, leaving 35 per group. The study was prospectively registered and conducted according to CONSORT guidelines, with written informed consent from all participants.
The stellate ganglion is a sympathetic nervous structure formed by the fusion of the inferior cervical and first thoracic ganglia, typically located in front of the transverse processes of the sixth and seventh cervical vertebrae. Blocking it involves injecting local anesthetic into the tissue surrounding this relay station of the fight-or-flight nervous system. In the trial, anesthesiologists performed the block 20 minutes before inducing general anesthesia, using a 10 MHz linear ultrasound probe to identify the ganglion on the surface of the longus colli muscle, deep to the internal carotid artery at the level of the cricoid cartilage. After confirming by negative aspiration that the needle had not entered a blood vessel, the airway, or the spinal fluid, they slowly injected 3 milliliters of 1% lidocaine to a depth of 3 to 3.5 centimeters. A successful block was confirmed by the appearance of Horner’s syndrome on the same side of the face, a combination of a constricted pupil, drooping eyelid, sunken eye, and conjunctival redness that signals the sympathetic pathway has been interrupted.
The design was single-blind but carefully constructed to protect the integrity of the results. Only the anesthesiologist performing the block or sham puncture knew the group assignments; the anesthesiologists managing anesthesia in the operating room, the surgeons, the nursing staff, and the patients themselves all remained blinded. Every patient received the same standardized general anesthesia, induced with etomidate, sufentanil, and rocuronium, and maintained with infusions of propofol and remifentanil plus inhaled sevoflurane, with anesthetic depth titrated to keep the bispectral index between 40 and 60. All patients had invasive arterial blood pressure monitoring established before induction, allowing beat-to-beat tracking of mean arterial pressure and heart rate at nine predefined time points, from baseline through tracheal intubation, the start of surgery, the establishment of the carbon dioxide pneumoperitoneum, tumor exploration, specimen removal, and the end of the operation.
The primary outcome was the incidence of intraoperative hypertension, defined as a systolic blood pressure of at least 180 mmHg or a rise of 30% or more in mean arterial pressure from baseline. Only 5 of the 35 patients in the block group, 14.3%, met this definition, compared with 13 of 35 controls, 37.1%, a statistically significant difference with a p value of 0.029. The sample size had been calculated from a pilot study of 15 patients per group, in which hypertension rates were 6.7% with the block and 33.3% without, powered at 80% to detect such a difference with a 10% allowance for dropouts.
The hemodynamic tracings told a consistent story. Patients in the block group had significantly lower mean arterial pressure and heart rate than controls at all eight post-baseline time points, from immediately after tracheal intubation to the end of surgery, with p values ranging from less than 0.001 to 0.009. Relative to their own baselines, block-group patients showed significant drops in mean arterial pressure from the start of surgery onward, with mean differences reaching as much as 16 mmHg below baseline by the end of the operation. In the control group, by contrast, mean arterial pressure spiked significantly immediately after intubation, rising by an average of about 11 mmHg, and heart rate jumped by an average of about 7 beats per minute at the same moment. The block group showed no significant heart rate rise at intubation at all.
Drug use reflected these differences. Patients in the block group required significantly less phentolamine, the alpha-blocker used to treat hypertensive spikes, with a median intraoperative dose of 0 mg compared with 0 mg in controls whose interquartile range extended to 4 mg, a difference with a p value of 0.008. The trade-off came on the other side of the blood pressure ledger: the block group consumed significantly more norepinephrine, the vasopressor used to treat hypotension, with an interquartile range reaching 8 micrograms versus none in controls, p = 0.004. Hypotension, defined as systolic pressure below 80 mmHg or a 30% fall in mean arterial pressure, occurred in 12 block-group patients, 34.3%, versus 2 controls, 5.7%, a significant difference. Consumption of esmolol for tachycardia and atropine for bradycardia did not differ between groups.
The authors attribute the benefit to the block’s dampening of sympathetic nervous system activity on several fronts. Direct inhibition of sympathetic efferent impulses reduces the release of stress hormones such as norepinephrine, relaxing vascular smooth muscle and lowering peripheral vascular resistance. The block may also modulate the hypothalamic-pituitary-adrenal axis, curbing excessive adrenal hormone secretion at its source. And by preemptively interrupting sympathetic conduction, it can blunt the reflex surge triggered when surgeons traction or compress the tumor. The surgical context matters: adrenal tumors can secrete aldosterone or cortisol, and manipulation of the tumor can provoke abrupt hormone release causing intense vasoconstriction, while the carbon dioxide pneumoperitoneum needed for laparoscopy raises intra-abdominal pressure, compresses the aorta, impairs venous return, and further fuels catecholamine release. The authors also note that the stellate ganglion shares connective tissue with vagus nerve fibers, so mild vagal blockade may occur, though they consider this influence minimal compared with the dominant sympathetic inhibition.
Safety findings were reassuring. All patients in the block group developed the expected transient Horner’s syndrome, and no case persisted after surgery. One patient experienced transient hoarseness that fully resolved within two hours. Rates of postoperative nausea, hoarseness, and sore throat did not differ significantly between groups, and the overall incidence of intraoperative adverse events was comparable. The authors suggest that the increased norepinephrine requirement may partly reflect the block’s vasodilating effect, and possibly an overestimated depth of analgesia, since pain perception was not specifically monitored and a relatively high remifentanil dose could have worsened intraoperative hypotension.
The trial has clear limits that the authors themselves emphasize. It was a single-center study with a modest sample, so selection bias and limited generalizability remain concerns pending multicenter replication. Patients with pheochromocytoma were excluded for safety, leaving the block’s effects in that high-risk population unknown. No pre-specified subgroup analysis by tumor subtype, such as aldosterone-producing adenoma, cortisol-producing adenoma, or non-functioning adenoma, was performed, even though differing hormone profiles and baseline sympathetic tone might produce different responses. The study also captured only intraoperative hemodynamics, with no follow-up on postoperative cardiovascular function or quality of life. Within those boundaries, the authors conclude that preoperative ultrasound-guided stellate ganglion block reduced the risk of intraoperative hypertension in this operation without elevating adverse events, offering a potential strategy for optimizing anesthetic management in patients undergoing laparoscopic partial adrenalectomy.
Subject of Research: Effect of ultrasound-guided stellate ganglion block on intraoperative hemodynamics during laparoscopic partial adrenalectomy
Article Title: Effect of ultrasound-guided stellate ganglion block on intraoperative hemodynamics in laparoscopic partial adrenalectomy: a randomized clinical trial
Article References: Nie, J., Wang, H., Zhang, W., Wang, H., Hao, P., Liu, J., Shang, J., & Zhang, W. (2026). Effect of ultrasound-guided stellate ganglion block on intraoperative hemodynamics in laparoscopic partial adrenalectomy: a randomized clinical trial. Frontiers in Neuroscience, 20, Article 1966414. https://doi.org/10.3389/fnins.2026.1966414
Image Credits: AI Generated
DOI: 10.3389/fnins.2026.1966414
Keywords: stellate ganglion block, laparoscopic adrenalectomy, intraoperative hypertension, hemodynamic stability, randomized controlled trial, anesthesiology, adrenal tumors, sympathetic nervous system, ultrasound-guided nerve block, vasoactive drugs, Effect, ultrasound-guided
News Source: Ophelia Keating. (October 26, 2026). Nerve Block Tames Blood Pressure Spikes During Adrenal Tumor Surgery, Trial Finds. Scienmag.