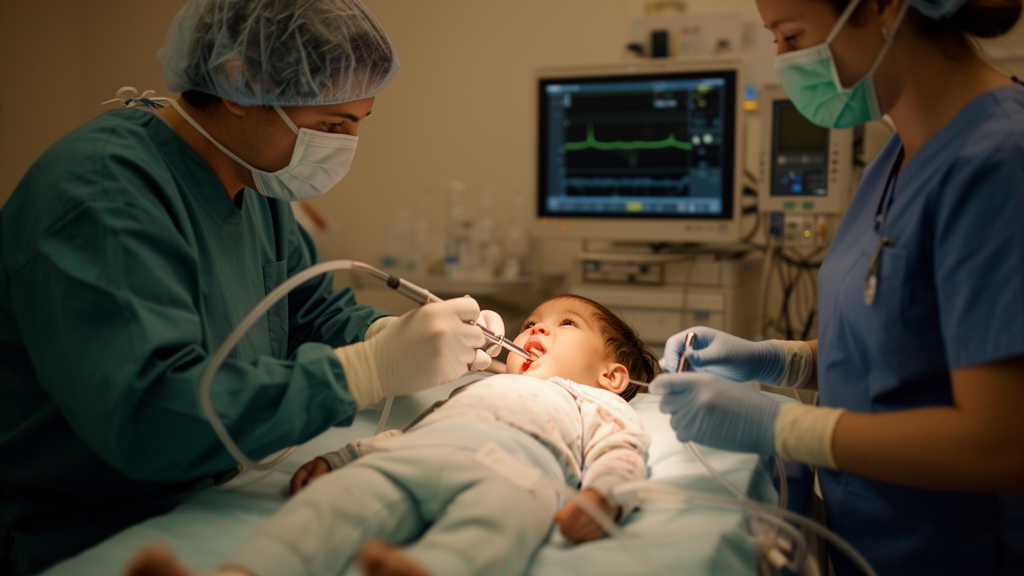
Endoscopic retrograde cholangiopancreatography, better known in medical circles as ERCP, has long been one of the most technically demanding procedures in digestive medicine. The technique involves threading a side-viewing endoscope called a duodenoscope deep into the upper small intestine, locating the tiny opening where the bile and pancreatic ducts drain into the gut, and then injecting contrast dye and deploying instruments to remove stones, open strictures, or place stents. In adults it is a routine therapeutic workhorse. In children, it has always been more complicated, because the instruments were designed for adult anatomy and pediatric-specific scopes are not widely available. A new 14-year study from Seoul National University Hospital, published in BMC Pediatrics, now offers one of the clearest long-term pictures yet of what happens when doctors routinely use conventional adult duodenoscopes in young patients, and the findings carry an important warning about the youngest children.
The retrospective study, led by Tae Seung Lee and Woo Hyun Paik of the Department of Internal Medicine and Liver Research Institute at Seoul National University Hospital, together with pediatric gastroenterology colleagues at Seoul National University College of Medicine, analyzed every ERCP procedure performed in patients younger than 19 years at their tertiary referral center over a 14-year period. The research team combed through demographic characteristics, clinical indications, procedural details, and sedation methods, and then tracked two critical endpoints: technical success, meaning the endoscopist actually accomplished the intended therapy, and ERCP-related adverse events, with particular attention to post-ERCP pancreatitis, the procedure’s most feared complication. Sedation was delivered according to institutional protocols and categorized as moderate to deep sedation based on American Society of Anesthesiologists definitions, reflecting the reality that children almost never tolerate this procedure awake.
The scale of the dataset is notable for a procedure that remains rare in pediatrics. Over the 14 years, 82 patients underwent a total of 153 ERCP procedures. That means many children returned for repeat interventions, a pattern typical of complex pancreatobiliary disease in young patients, where stones reform, stents need exchanging, and ductal anatomy demands staged treatment. Crucially, the cohort included 28 procedures performed in children aged just 1 to 6 years, a group in whom even the conventional adult duodenoscope represents an outsized instrument relative to body size, and in whom data have historically been thinnest.
The headline result is encouraging on the efficacy front. The technical success rate was 91.5 percent, meaning that in more than nine out of ten procedures the team achieved its therapeutic goal despite working with equipment never specifically designed for children. For a procedure that requires cannulating a ductal opening that may be only a millimeter or two across in a toddler, and then manipulating guidewires, sphincterotomes, and stents through it, that figure suggests that experienced hands at a high-volume center can compensate substantially for the lack of pediatric-specific hardware. It also reinforces a long-standing principle in interventional endoscopy: operator and center experience matter enormously when adapting adult technology to pediatric patients.
Safety, however, tells a more nuanced story. Procedure-related adverse events occurred in 46 of the 153 procedures, a rate of 30.1 percent. That number looks striking at first glance, particularly against adult ERCP series where overall adverse event rates typically sit far lower, but the severity distribution is the key detail. The overwhelming majority of events in this pediatric cohort were mild to moderate, and there were no severe adverse events and no mortality across the entire 14-year experience. In other words, while nearly one in three procedures produced a complication, none of those complications escalated into the catastrophic territory of perforation requiring emergency surgery, severe systemic illness, or death.
The most common complication was post-ERCP pancreatitis, or PEP, which occurred after 22 procedures, a rate of 14.4 percent. PEP arises when the pancreatic duct is irritated or transiently obstructed during the procedure, triggering inflammation of the pancreas that typically manifests as abdominal pain and elevated pancreatic enzymes in the hours after sedation wears off. It is the most studied and most dreaded complication of ERCP in all age groups, and preventing it is a major focus of endoscopy research, from prophylactic nonsteroidal anti-inflammatory drugs given before or after the procedure to pancreatic duct stenting in high-risk cases. A pediatric rate of 14.4 percent is higher than the single-digit figures generally reported in large adult series, and understanding why became the analytical heart of the study.
The answer the researchers found was age. In multivariable analysis, which adjusts for multiple factors simultaneously to isolate independent effects, younger age was independently associated with an increased risk of post-ERCP pancreatitis. The effect was quantified as an odds ratio of 0.81 per unit increase in age, with a 95 percent confidence interval of 0.71 to 0.93 and a p-value of 0.003, a statistically robust signal. Expressed in practical terms, each additional year of age reduced the odds of PEP by roughly 19 percent, meaning the youngest children in the cohort bore a disproportionately high share of the pancreatitis risk. This finding aligns with the plausible biology: smaller ducts, a smaller papilla, and the mechanical mismatch of an adult-caliber instrument against infant and toddler anatomy all conspire to increase pancreatic trauma during cannulation and manipulation.
The clinical implications of that risk gradient are significant. Age, the authors conclude, may serve as a useful risk stratification factor, allowing pediatric gastroenterologists and their endoscopy partners to identify in advance which children deserve the most aggressive preventive measures and the closest post-procedural monitoring. For a toddler with a choledochal cyst or pancreatobiliary maljunction, conditions that appear among the study’s indexed keywords and that are classic indications for therapeutic ERCP in children, the decision to proceed should now be weighed against a quantified, age-adjusted pancreatitis risk rather than a vague sense that children do fine. It also strengthens the case for prophylactic strategies such as rectal NSAIDs, which are established PEP prevention in adults and can reasonably be applied to pediatric high-risk cases under specialist judgment.
The study also speaks to a persistent equipment gap. Pediatric-specific duodenoscopes remain preferable, the authors state, but they are not widely available, which is precisely why conventional adult scopes dominate real-world pediatric practice. Their conclusion is measured: conventional duodenoscopes may be a reasonable alternative in selected patients when pediatric scopes are unavailable. That conditional phrasing matters. The 91.5 percent technical success and absence of severe events come from a single tertiary referral center with a mature pediatric hepatology and pancreatobiliary service, deep anesthesia and sedation support, and endoscopists who perform high volumes of complex ERCP. Transplanting those expectations to a low-volume center without pediatric infrastructure would be a mistake, and the 30.1 percent overall adverse event rate is a reminder that acceptable is not the same as benign.
For families facing a recommendation of ERCP for a child, the practical takeaways are concrete. The procedure works most of the time even with adult equipment, serious complications were not seen in this large 14-year experience, and the main risk to plan for is post-procedural pancreatitis, which is usually mild to moderate and concentrated in the youngest patients. For the field, the study adds a substantial longitudinal dataset to a sparse evidence base and makes a clear implicit argument: the development and wider availability of pediatric-specific duodenoscopes, sized for the anatomy of the smallest patients, could convert today’s acceptable outcomes into genuinely optimized ones. Until then, age-stratified risk assessment and experienced tertiary centers remain the best safeguards for children undergoing one of gastroenterology’s most intricate procedures.
Subject of Research: Outcomes and safety of pediatric ERCP performed with conventional adult duodenoscopes
Article Title: Practice patterns and outcomes of pediatric ERCP using conventional duodenoscopes: a 14-year single-center experience
Article References: Lee, T. S., Choi, J. H., Cho, I. R., Lee, S. H., Shim, J. O., Moon, J. S., Ko, J. S., Ryu, J. K., & Paik, W. H. (2026). Practice patterns and outcomes of pediatric ERCP using conventional duodenoscopes: a 14-year single-center experience. BMC Pediatrics. https://doi.org/10.1186/s12887-026-07664-y
Image Credits: AI Generated
DOI: 10.1186/s12887-026-07664-y
Keywords: pediatric ERCP, duodenoscope, post-ERCP pancreatitis, endoscopy, pancreatobiliary disorders, choledochal cyst, pancreatobiliary maljunction, technical success, adverse events, tertiary referral center, risk stratification, BMC Pediatrics
News Source: Harold Sullivan. (October 15, 2026). Adult Scopes, Small Patients: 14-Year Study Maps the Real Risks of Pediatric ERCP. Scienmag.