


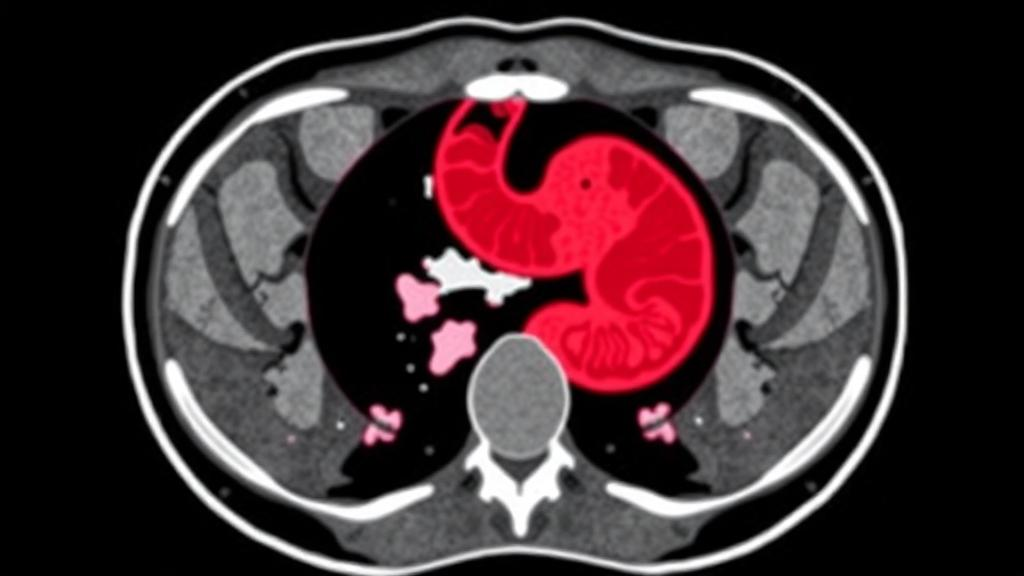
Gastric cancer remains one of the most formidable challenges in global oncology, a disease that is often diagnosed late and treated with decisions that must be made before a surgeon ever sees the tumor with their own eyes. The difference between an aggressive treatment plan and a conservative one frequently hinges on pathological features that can only be confirmed after surgery, when a pathologist examines the resected tissue under a microscope. Now, a sweeping systematic review and meta-analysis published in BMC Medical Imaging suggests that artificial intelligence may be able to close that gap, extracting predictive signals from ordinary preoperative CT scans that the human eye routinely misses. The study, led by Shichang Cui and colleagues at the First Affiliated Hospital of Shandong First Medical University in Jinan, China, pooled data from 40 studies encompassing 12,769 patients and found that radiomics-based models can predict several high-risk pathological features of gastric cancer with impressive, though not yet clinical-grade, accuracy.
The four features at the heart of the analysis are among the most consequential determinants of gastric cancer prognosis. Perineural invasion, or PNI, describes cancer cells wrapping around nerve fibers, a route the tumor can exploit to spread beyond the visible mass. Lymph node metastasis, LNM, indicates that the disease has already seeded the lymphatic system, a finding that fundamentally reshapes the surgical approach and the decision to administer neoadjuvant chemotherapy. Lymphovascular invasion, LVI, signals tumor cells invading blood or lymphatic vessels, portending hematogenous spread. Serosal invasion means the tumor has penetrated the outermost serosal layer of the stomach wall, dramatically raising the risk of peritoneal dissemination. Today, clinicians estimate these risks using endoscopic ultrasound, contrast-enhanced CT, and clinical judgment, but each modality has well-documented blind spots, particularly in assessing nodal involvement and microscopic invasion patterns that do not visibly thicken the gastric wall.
Radiomics offers a fundamentally different way of interrogating medical images. Rather than relying on a radiologist’s qualitative impressions, radiomics pipelines convert regions of interest drawn on CT, MRI, or PET/CT scans into hundreds or thousands of quantitative features. These descriptors capture first-order statistics of pixel intensity, texture measures that quantify heterogeneity at multiple scales, and shape parameters describing the tumor’s geometry. The underlying premise is elegant: the molecular and cellular chaos of an aggressive tumor, including its infiltrating stroma, necrotic cores, and irregular vasculature, leaves a fingerprint in the spatial distribution of image intensities. Machine learning algorithms, ranging from penalized logistic regression with LASSO feature selection to random forests, support vector machines, and increasingly deep neural networks, are then trained to map these fingerprints onto pathological ground truth.
To evaluate how well this promise has translated into published evidence, the research team conducted a review registered with PROSPERO and reported according to the PRISMA-DTA guidelines, the international standard for systematic reviews of diagnostic test accuracy studies. They systematically searched PubMed, Web of Science, the Cochrane Library, and Embase for studies published up to May 11, 2026, that developed or validated radiomics models for preoperatively predicting PNI, LNM, LVI, or serosal invasion in gastric cancer. Methodological rigor was scrutinized with two complementary instruments: a modified version of the Quality Assessment of Diagnostic Accuracy Studies-2 tool, known as QUADAS-2, which probes sources of bias and applicability concerns in diagnostic studies, and the Radiomics Quality Score, or RQS, which grades how faithfully a radiomics study adheres to best practices such as external validation, open data, and biological corroboration.
The statistical machinery of the meta-analysis was equally deliberate. Predictive performance, expressed as the area under the receiver operating characteristic curve, or AUC, was pooled using a bivariate random-effects model, the standard approach for jointly synthesizing sensitivity and specificity while accounting for their trade-off. Because many studies reported multiple models or multiple effect sizes, the authors also applied a three-level random-effects model to properly partition variance between effect sizes within studies and between studies, preventing artificially narrow confidence intervals that arise when correlated estimates are treated as independent. This dual approach lends the pooled estimates a credibility that simpler meta-analyses of diagnostic models often lack.
The headline results are striking in their consistency. In validation cohorts, combined models, which integrate radiomics features with clinical variables such as patient age, tumor location, and serological markers, achieved a pooled AUC of 0.85, with a 95 percent confidence interval of 0.82 to 0.88, for predicting perineural invasion. For lymph node metastasis, the pooled AUC was likewise 0.85, and for lymphovascular invasion it edged slightly higher to 0.86, with a confidence interval of 0.82 to 0.89. Serosal invasion proved the best-predicted target: among seven studies addressing it, five contributed to the combined-model analysis, which yielded a pooled AUC of 0.90, with a confidence interval of 0.87 to 0.93. An AUC of 0.90 places such a model in territory traditionally reserved for the best diagnostic tests, suggesting that quantitative image features of serosal penetration are particularly conspicuous in preoperative imaging.
Yet the authors are careful, and rightly so, to temper enthusiasm with a crucial caveat. The 95 percent prediction interval for specificity in the serosal invasion analysis stretched from 0.44 to 0.97, an extraordinarily wide range that reveals how heterogeneous the underlying studies are. A prediction interval this broad means that while the average model performs well, any individual model applied in a new hospital could plausibly perform far worse. This heterogeneity likely stems from differences in scanner vendors, reconstruction kernels, slice thickness, segmentation protocols, feature selection strategies, and the class balance of the patient cohorts. Radiomics features are notoriously sensitive to such technical variation, and a model trained on one institution’s imaging pipeline may degrade substantially when transplanted to another.
A second, equally important limitation is that the evidence base rests predominantly on internal validation, meaning that most studies tested their models on data drawn from the same patients or the same institution used for training. Internal validation, whether through cross-validation or random train-test splits, systematically overestimates real-world performance because it cannot capture the full spectrum of population and technical variability a model will encounter in practice. Only a minority of the 40 studies performed true external validation on independent cohorts from different centers. The authors conclude that prospective, multicenter external validation is required before any of these models can be responsibly deployed in the clinic, a sentiment that echoes broader concerns in the radiomics literature about the gap between published performance and clinical readiness.
The methodological quality assessment reinforced this caution. While the modified QUADAS-2 evaluation and the Radiomics Quality Score provided a structured picture of where the field stands, the very need for such scrutiny reflects a young discipline still standardizing its practices. Many radiomics studies omit pre-registration, fail to share code and data, and report selective feature sets, all of which inflate apparent performance. Initiatives such as the Image Biomarker Standardisation Initiative and the emergence of federated learning frameworks, in which models are trained across hospitals without moving patient data, offer plausible paths toward the robust, generalizable models this meta-analysis implicitly calls for.
Even with these caveats, the implications of the study are considerable. If combined radiomics-clinical models can be validated prospectively, they could transform the preoperative workup of gastric cancer, helping surgeons decide between gastrectomy with extended lymphadenectomy and less invasive approaches, guiding the selection of patients for neoadjuvant therapy, and flagging cases at high risk of peritoneal spread for staging laparoscopy. For patients, that could mean avoiding overtreatment with its attendant morbidity, or conversely ensuring that aggressive disease is met with appropriately aggressive multimodal therapy from the outset. The 12,769 patients represented in this analysis have, in aggregate, provided the strongest evidence yet that the information needed to make those decisions may already be hiding in plain sight on a routine CT scan, waiting for algorithms mature enough, and validated broadly enough, to read it reliably.
Subject of Research: Radiomics-based preoperative prediction of high-risk pathological features in gastric cancer
Article Title: Radiomics-based models for the preoperative prediction of high-risk pathological features in gastric cancer: a systematic review and meta-analysis
Article References: Cui, S., Zhang, A., Liu, Z., Li, L., Zong, R., Li, W., Zhang, Z., Zhang, W., & Zhu, J. (2026). Radiomics-based models for the preoperative prediction of high-risk pathological features in gastric cancer: a systematic review and meta-analysis. BMC Medical Imaging. https://doi.org/10.1186/s12880-026-02804-3
Image Credits: AI Generated
DOI: 10.1186/s12880-026-02804-3
Keywords: gastric cancer, radiomics, machine learning, computed tomography, lymph node metastasis, perineural invasion, lymphovascular invasion, serosal invasion, meta-analysis, diagnostic accuracy, artificial intelligence, BMC Medical Imaging
News Source: Ophelia Keating. (October 13, 2026). AI Reads CT Scans to Predict Hidden Gastric Cancer Risks Before Surgery. Scienmag.



