Continuous regional anesthesia (CRA) has emerged as a cornerstone for managing postoperative pain, particularly in procedures where single-injection nerve blocks provide insufficient duration. By utilizing perineural and fascial plane catheters, clinicians can extend analgesic delivery far beyond the hours provided by a standard peripheral nerve block, potentially reducing reliance on systemic opioids. Despite its widespread adoption across surgical specialties, the efficacy of CRA remains contingent upon meticulous patient selection, precise catheter placement, and robust troubleshooting protocols. As surgeons and anesthesiologists navigate the complexities of modern perioperative care, this catheter-based approach offers a flexible solution for maintaining effective analgesia, though its clinical benefits vary substantially depending on the anatomical target, the specific infusion strategy, and the inherent risk profile of the patient population.
Central to the execution of CRA are the two primary catheter designs: catheter-through-needle (CTN) and catheter-over-needle (CON) systems. CTN systems, which mirror the logic of epidural placement, allow the catheter to be advanced through a needle after precise positioning. This method provides flexibility in depth adjustment and permits tunneling when prolonged use is anticipated. However, the puncture tract created by the larger needle can sometimes lead to leakage at the insertion site and a higher risk of dislodgement. Conversely, CON systems function similarly to standard intravenous cannulation, where the catheter advances over the needle or within an outer sheath. This design promotes a tighter seal, which enhances catheter stability and reduces leakage, though it typically limits the ability to adjust the insertion depth or perform extensive tunneling.
The configuration of the catheter tip further distinguishes these systems. Single-orifice catheters deliver a concentrated injectate, whereas multi-orifice catheters distribute local anesthetic through several lateral openings, potentially fostering a broader, more uniform tissue spread. This broader distribution might reduce the probability of catheter blockage, though effectiveness hinges on all lateral openings remaining within the intended space; partial displacement can lead to unintended intravascular or extraneural administration. Beyond configuration, technological advancements have introduced stimulating catheters, which include a conductive element to assess proximity to a target nerve through electrical stimulation. While these tools allow for functional confirmation, they often require longer insertion times compared to ultrasound-guided nonstimulating variants, without necessarily providing a definitive analgesic advantage. Echogenic catheters, which utilize surface modifications to improve visibility under ultrasound, are increasingly favored for real-time positioning in technically challenging anatomical fields.
The delivery of local anesthetic is managed through either electronic or elastomeric pumps, each presenting trade-offs for clinical application. Electronic pumps are highly adaptable, providing the ability to deliver basal infusions, programmed intermittent boluses, and patient-controlled demand doses, all supported by sophisticated alarms and lockout intervals. Their primary limitation remains their bulk, cost, and power dependence, which can restrict their use in ambulatory settings. In contrast, elastomeric pumps are silent, lightweight, and require no power, making them highly practical for outpatient care. Their passive recoil mechanism delivers a fixed, manufacturer-specified flow rate. However, they lack programmable versatility and sophisticated alarm features, and their flow rates are sensitive to ambient temperature and back pressure, necessitating visual monitoring of reservoir volume to ensure consistent delivery.
Infusion strategies range from simple continuous basal delivery to more complex programmed intermittent bolus (PIB) protocols. Continuous basal infusion, while simple, is associated with a higher risk of systemic local anesthetic exposure and motor impairment due to the constant dosage. PIB regimens inject defined volumes at scheduled intervals, generating higher tissue pressures that may broaden local anesthetic spread within fascial planes. Although some studies suggest PIB improves analgesic efficiency, the clinical evidence is far from uniform. For example, randomized trials in patients undergoing video-assisted thoracoscopic surgery have shown that PIB does not always improve overall quality of recovery or patient outcomes compared to continuous infusion, suggesting that theoretical advantages in injectate spread do not always translate into measurable clinical improvement in every surgical cohort.
The success of catheter insertion relies heavily on ultrasound guidance, which begins with ergonomic positioning and a thorough preprocedural scan to identify anatomy. The choice between short-axis (SAX) and long-axis (LAX) imaging, alongside in-plane (IP) or out-of-plane (OOP) needle orientation, is dictated by the specific anatomical target and the operator’s expertise. SAX-IP remains the standard for visualizing cross-sections, allowing the needle and tip to be tracked as a continuous line. Once the catheter is advanced, functional confirmation of the tip position is vital, especially for CTN systems where the catheter can unpredictably coil. While direct visualization is the gold standard, small-volume saline injections can provide functional proof of injectate spread around the nerve or within the fascial compartment. Caution is advised with air-based confirmation, as reverberation artifacts can obscure the anatomy and complicate subsequent interventions.
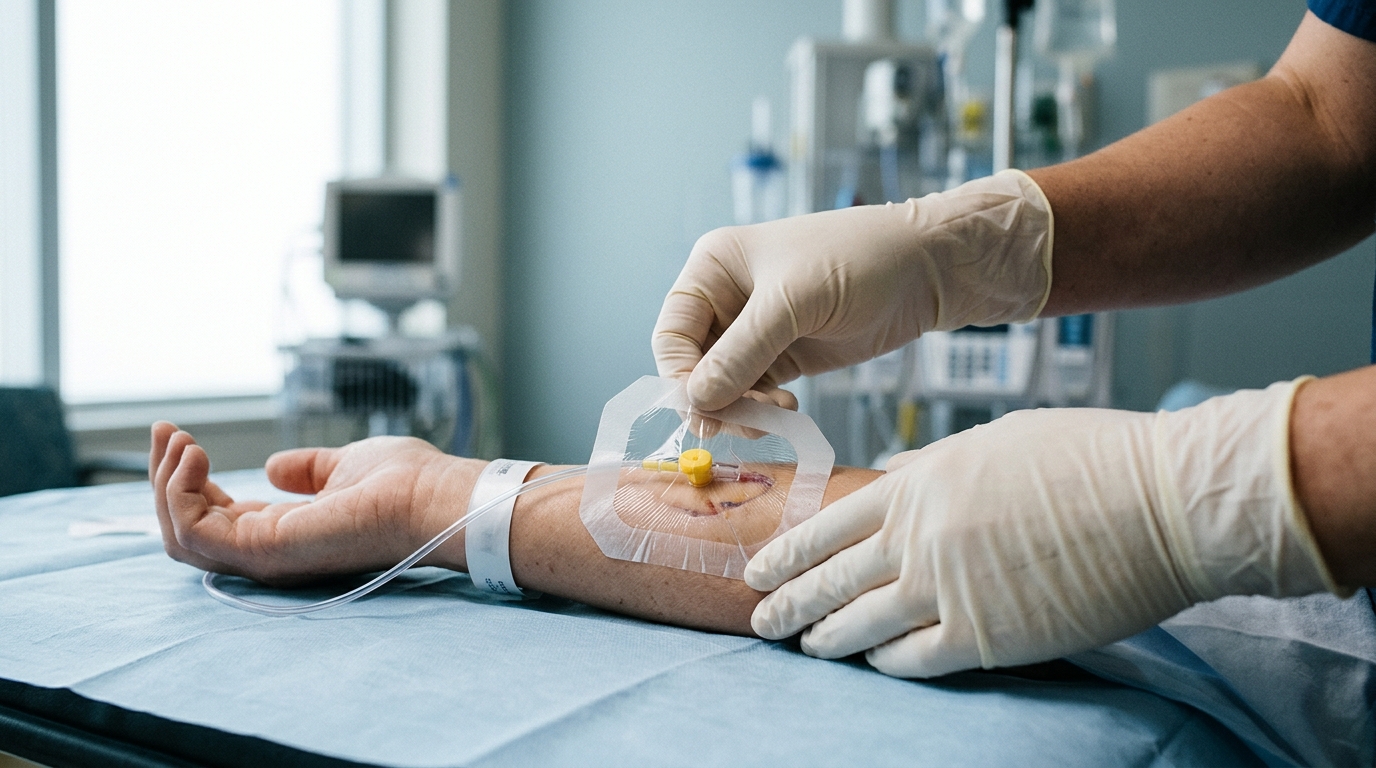
Catheter migration remains a persistent obstacle in CRA, often leading to secondary block failure and the need for premature removal. To mitigate this risk, clinical protocols often adopt a multimodal fixation approach. Cleansing the skin thoroughly and applying 2-octyl cyanoacrylate at the catheter-skin interface can reinforce the puncture site and limit leakage. Furthermore, dedicated sutureless anchoring devices, such as Clik-FIX-type systems, transfer traction away from the insertion site, providing additional mechanical stability. While tunneling—placing a segment of the catheter beneath the skin—is often employed to prevent accidental withdrawal and potential bacterial colonization, clinical evidence suggests that it should be reserved for scenarios involving prolonged catheterization or extensive patient mobilization, as it does not replace the necessity for robust external securement.
Clinical evidence for CPNB effectiveness is robust for upper limb surgeries, where techniques like infraclavicular and interscalene blocks offer profound analgesia and opioid-sparing effects. In the lower limbs, femoral nerve catheters are prioritized for cases where prolonged anesthesia is necessary, such as complex hip fractures. However, they have been partially replaced in elective procedures by motor-sparing alternatives like adductor canal blocks, which better preserve quadriceps function and facilitate early rehabilitation. For foot and ankle surgeries, continuous popliteal sciatic blocks provide dense analgesia, though success depends on precise positioning within the paraneural sheath. For trunk and thoracic procedures, fascial plane blocks such as the continuous erector spinae plane block (cESPB) and the continuous serratus anterior plane block (cSAPB) have shown significant promise, often matching the analgesic efficacy of more invasive techniques like thoracic epidural analgesia while maintaining hemodynamic stability.
In abdominal surgery, the utility of continuous fascial plane blocks varies. Continuous transversus abdominis plane blocks (cTAPB) have demonstrated efficacy in accelerating mobilization and reducing hospital stays after radical cystectomy, yet their effectiveness in controlling visceral pain remains limited, often necessitating a multimodal analgesic approach. Breast surgery evidence indicates that continuous pectoral fascial plane blocks can effectively spare opioids, matching the outcomes of more traditional neuraxial techniques with fewer risks. Cardiac surgery, which presents unique challenges due to systemic anticoagulation, increasingly relies on these non-neuraxial catheters. While results for cESPB in minimally invasive cardiac surgery have been mixed, continuous parasternal intercostal plane blocks have demonstrated potential in reducing opioid consumption and improving recovery after median sternotomy, emphasizing the importance of selecting the appropriate block based on the expected dermatomal coverage of the surgical incision.
The safety of CRA is underpinned by strict adherence to local anesthetic dosing principles, which must account for the total cumulative exposure from all catheters, boluses, and systemic sources. Local anesthetic systemic toxicity (LAST) remains the most critical safety concern, particularly in patients with organ dysfunction, low body weight, or frailty. While ultrasound reduces the risk of incorrect injection, it does not eliminate the potential for systemic absorption. Safety protocols demand independent verification of dose calculations, the use of the lowest effective concentration, and the ongoing monitoring of patients for neurologic or cardiovascular signs of toxicity. Because delayed LAST can manifest days after the procedure, an initially successful block does not preclude the need for persistent, daily reassessment of both the clinical necessity of the catheter and the potential for toxicity.
Troubleshooting a failing catheter requires a systematic clinical algorithm. If analgesia is insufficient, clinicians must first distinguish between mechanical issues—such as pump malfunction, kinking, or site leakage—and anatomical malposition. A small rescue bolus can provide an essential diagnostic clue; if analgesia improves, the catheter remains functional but may require a dosage adjustment. If the block does not recover, replacement or removal is often indicated. As the field looks to the future, research remains focused on standardizing the mode of delivery, refining pharmacokinetic understanding of different anatomical approaches, and developing more effective catheter-fixation technologies. By integrating these structured troubleshooting techniques with individualized, evidence-based care, CRA continues to evolve as a vital tool in modern multimodal postoperative pain management.
Subject of Research: Clinical review of continuous regional anesthesia techniques and catheter management.
Article Title: Continuous Regional Anesthesia: A Practical Review of Perineural and Fascial Plane Catheters, Clinical Evidence, and Troubleshooting
Article References: Dost, B., Narayanan, M., Kaya, C., Wand, R., Yayik, A. M., John Martin Alexis, R., Bugada, D., Turunc, E., & De Cassai, A. (2026). Continuous Regional Anesthesia: A Practical Review of Perineural and Fascial Plane Catheters, Clinical Evidence, and Troubleshooting. Pain and Therapy. https://doi.org/10.1007/s40122-026-00899-8
Image Credits: AI Generated
DOI: 10.1007/s40122-026-00899-8
Keywords: Continuous Regional Anesthesia, Peripheral Nerve Blocks, Fascial Plane Blocks, Catheter Systems, Ultrasound-Guided Anesthesia, Postoperative Pain Management, Local Anesthetic Systemic Toxicity, Catheter Migration, Programmed Intermittent Bolus, Opioid-Sparing Analgesia, Catheter Fixation, Anesthesiology, Regional Analgesia, Clinical Troubleshooting, Infusion Strategies
News Source: Ophelia Keating. (November 16, 2026). Optimizing Continuous Regional Anesthesia Through Precision Catheter Management. Scienmag.