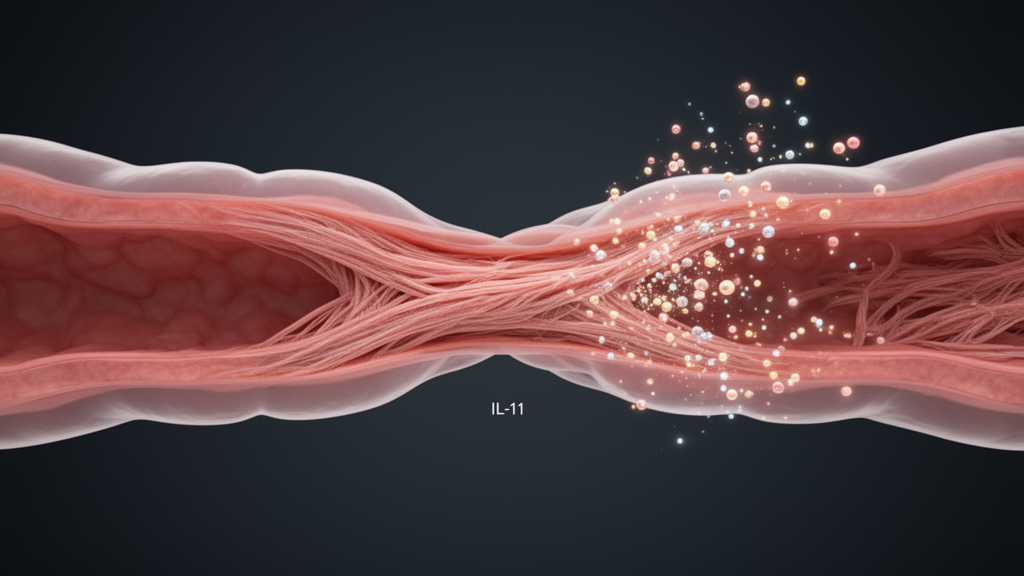
For millions of people living with Crohn’s disease, the most feared complication is not the inflammation itself but what it leaves behind: fibrostenotic strictures, segments of bowel wall so thickened with scar tissue and muscle that food can no longer pass through. Anti-inflammatory drugs can quiet the immune system, yet once a stricture has formed, patients typically face endoscopic balloon dilation or surgery. A narrative review published in Frontiers in Pharmacology by He Chen and Shuang Liang of the Fourth People’s Hospital of Shenyang now takes a hard, technically rigorous look at interleukin-11 (IL-11), a cytokine increasingly proposed as the next great anti-fibrotic drug target, and asks a question that is deceptively simple: does high IL-11 in a strictured bowel wall mark an ongoing dependency that a drug could reverse, or does it merely flag remodeling that is already too advanced to undo?
The review’s central framing is the selective-inhibition hypothesis. IL-11, a member of the IL-6 cytokine family, binds its specific alpha receptor IL-11Rα and then recruits gp130, the shared signal transducer used by other IL-6-family ligands, triggering JAK/STAT, ERK and downstream signaling that depends on the responding cell. Because IL-11Rα expression, unlike broadly expressed gp130, helps determine which cells respond, blocking the ligand or its alpha receptor is a far more selective pharmacological question than inhibiting gp130, ERK or JAK/STAT, all of which are shared with other cytokine pathways. Chen and Liang are explicit that an effect seen after gp130 or STAT3 inhibition cannot identify IL-11 as the responsible upstream ligand, and that total serum IL-11 or phosphorylated STAT3 alone is an insufficient measure of intestinal target engagement.
The historical record is more ambivalent than current enthusiasm suggests. In the 1990s, recombinant human IL-11 (rhIL-11) was developed as an agonist, not an inhibitor, motivated by preclinical evidence that the cytokine stimulated crypt-cell proliferation, accelerated mucosal recovery after chemotherapy and radiation, and dampened NF-κB activity in activated macrophages. Three randomized trials in active Crohn’s disease followed. A 1999 dose-escalation trial in 76 participants found exploratory response rates of 33 to 42 percent in the 16 μg/kg/week groups versus 7 percent with placebo. A 2002 trial in 148 evaluable patients reported remission in 36.7 percent of the once-weekly 15 μg/kg arm versus 16.3 percent on placebo, though the primary continuous Crohn’s Disease Activity Index endpoint showed only a non-significant trend and the twice-weekly regimen failed to replicate the signal. The decisive blow came in 2006, when a double-blind trial comparing rhIL-11 with prednisolone in 51 patients found remission at week 4 of just 4 percent versus 46 percent. None of the three trials selected patients by imaging-defined fibrostenosis or measured bowel-wall mechanics, so they neither validate IL-11 inhibition nor exclude a different effect at a different disease stage.
Mouse genetics tell an equally context-dependent story. In acute dextran sulfate sodium (DSS) colitis, global Il11 or Il11ra1 deficiency worsened epithelial apoptosis, mucosal injury and weight loss, suggesting that endogenous IL-11 protects the epithelium during acute injury. Yet when Pokatayev and colleagues induced Il11 deletion after each of three cycles of DSS injury and recovery, colonic collagen-positive area, hydroxyproline content and profibrotic transcripts all fell, while inflammatory trajectories were broadly similar between groups. The study also identified a circuit in which proinflammatory macrophages induce IL-11 production by inflammation-associated fibroblasts. Gain-of-function experiments add nuance: smooth-muscle-targeted Il11 overexpression increased inflammation, muscularis thickness, collagen staining and hydroxyproline, whereas fibroblast-targeted overexpression increased inflammation and muscle thickness but did not significantly increase the reported collagen or hydroxyproline measurements. Sufficiency, in other words, depends on the cellular source and the outcome measured.
Human evidence links IL-11 to fibrostenosis but stops short of causation. Tan and colleagues reported increased IL11 transcripts and IL-11 protein in fibrostenotic Crohn’s tissue, with immunostaining localizing the protein to COL1A1-positive cells and single-cell RNA data placing IL11RA transcripts predominantly in fibroblasts. Recombinant human IL-11 increased matrix proteins in primary intestinal fibroblasts. In a serum cohort of 63 patients, IL-11 was higher in stricturing and penetrating disease than in non-stricturing, non-penetrating disease, and an exploratory 19-patient subgroup linked higher serum IL-11 to subsequent surgery. Separately, Li and colleagues reported enrichment of IL11-expressing fibroblasts in anti-TNF non-responders, with IL-11 immunostaining higher in 23 subsequent non-responders than in 13 responders among 36 pretreatment samples. Full-thickness spatial profiling by Koplev and colleagues mapped COL7A1-high inflammatory fibroblasts to immune-rich mucosal ulcers, whereas GREM1-high fibrotic muscle and TNC-high myofibroblasts predominated in adjacent, relatively immune-depleted submucosal fibrosis, with fibroblasts showing the highest IL11 expression. These are associations with subsets and compartments, not proof that an IL-11-high lesion responds to selective blockade.
The review is equally careful about stricture biology. A Crohn’s stricture is not synonymous with collagen accumulation: it is a structural lesion in which extracellular-matrix deposition and cross-linking, smooth-muscle hypertrophy and hyperplasia, myofibroblasts, pericytes, vascular and neural remodeling, edema, immune infiltrates and mesenteric creeping fat coexist in a spatially organized process. An IL-11-dependent fibroblast response could account for only part of the narrowing. Reduced collagen expression might leave smooth-muscle expansion, tissue stiffness and luminal caliber unchanged, while reduced edema might improve imaging without indicating matrix regression. Activated muscularis propria cells can even create an extracellular-matrix niche that promotes preadipocyte migration and creeping-fat formation, and mesenteric adipose-derived exosomal TINAGL1 has been shown to activate primary intestinal fibroblasts and increase experimental fibrosis through TGF-β/SMAD4 signaling, illustrating that the stricture phenotype extends well beyond a fibroblast-only model.
Pharmacologically, several intervention classes are on the table. Neutralizing anti-IL-11 antibodies offer direct ligand selectivity and potentially interpretable free-ligand assays, provided the assay accounts for drug-bound ligand and complex-mediated clearance. Anti-IL-11Rα antibodies intercept receptor-proximal signaling but differ in occupancy, internalization and tissue distribution. Engineered competitive antagonists or decoy ligands may permit tunable exposure profiles but require unusually rigorous partial-agonism testing because receptor binding without productive signaling is the intended mechanism. A sponsor-led report describes LASN01, an IL-11Rα-blocking antibody, in early studies outside inflammatory bowel disease, with systemic pharmacokinetics, pharmacodynamics and preliminary adult tolerability up to 48 weeks of exposure. In a small phase 2 thyroid eye disease study, 17 participants received LASN01 and nine received placebo; the clinical activity score response favored LASN01 but proptosis response did not. Cross-organ work in lung, liver, kidney, heart and pancreas supports the tractability of IL-11 inhibition, but differing endpoints and exposure requirements preclude direct extrapolation to Crohn’s strictures, and intestinal efficacy remains untested.
Safety considerations are nontrivial. Biallelic IL11RA variants cause developmental craniosynostosis syndromes, and congenital deficiency differs from reversible adult drug exposure but identifies developmental and skeletal domains requiring surveillance. Historical agonist exposure supports hematologic monitoring, and the acute-deficiency mouse data raise a timing hypothesis: an initial study might favor patients with controlled mucosal inflammation and persistent, predominantly fibrotic narrowing rather than severe active ulceration. The review proposes that early studies monitor endoscopic ulceration, inflammatory markers, wound healing, infections and hematologic effects alongside exposure, with prespecified interruption criteria for new ulceration, poor healing or infection, and that background biologic or small-molecule therapy be recorded because combination treatment can alter infection risk, exposure and inflammatory outcomes.
The decisive next test, Chen and Liang argue, is selective inhibition initiated after a structural lesion is documented by central imaging, with verified intestinal tissue exposure and separate structural, inflammatory and repair outcomes. A randomized add-on study could enroll adults with non-emergent ileal or ileocolonic strictures receiving stable, optimized anti-inflammatory care, using blinded, standardized magnetic resonance enterography or intestinal ultrasound to follow the same lesion over time, with inflammation assessed independently. Interpretation must distinguish inadequate tissue exposure or insufficient follow-up from a biological null result, and structural stabilization must be separated from regression relative to baseline. Concordant tissue and structural improvement would justify a larger trial, provided it cannot be explained solely by reduced inflammation. Until such a study is done, the review’s verdict stands: IL-11 is a biologically credible target for fibrostenotic Crohn’s disease, but the claim that an IL-11-high stricture is pharmacologically reversible remains exactly that, a hypothesis awaiting its experiment.
Subject of Research: IL-11 in fibrostenotic Crohn’s disease: historical agonism, the selective-inhibition hypothesis, and evidence thresholds for translation
Article Title: IL-11 in fibrostenotic Crohn’s disease: historical agonism, the selective-inhibition hypothesis, and evidence thresholds for translation
Article References: Chen, H., & Liang, S. (2026). IL-11 in fibrostenotic Crohn’s disease: historical agonism, the selective-inhibition hypothesis, and evidence thresholds for translation. Frontiers in Pharmacology, 17, Article 1951110. https://doi.org/10.3389/fphar.2026.1951110
Image Credits: AI Generated
DOI: 10.3389/fphar.2026.1951110
Keywords: IL-11, fibrostenotic, Crohn, disease, historical, agonism, selective-inhibition, hypothesis, evidence, thresholds, translation, scientific research
News Source: Ophelia Keating. (October 17, 2026). IL-11: The Cytokine That Could Finally Soften Crohn’s Disease Strictures. Scienmag.