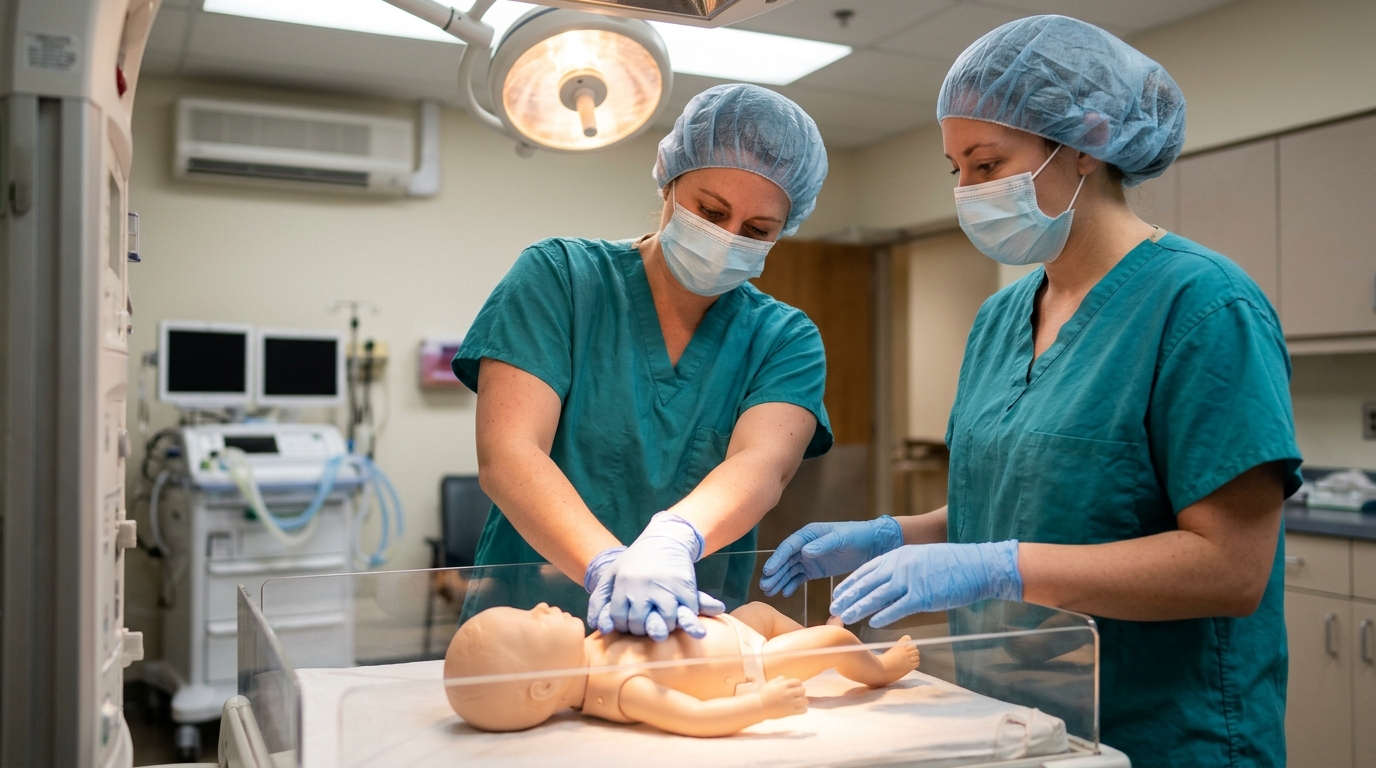
Chest compressions are among the rarest interventions in neonatal medicine, required in fewer than 0.1% of births, yet they are among the most physically demanding. A new simulation study by Wang and colleagues, published in Pediatric Research, examined whether rotating the clinician performing compressions every minute preserves compression quality better than rotating at the currently recommended interval. In carefully controlled manikin trials involving trained neonatal clinicians, more frequent rotation preserved compression depth and frequency and improved a novel composite measure of compression efficacy over three minutes of cardiopulmonary resuscitation, without significantly increasing interruption times or reducing the chest compression fraction.
The study introduced a composite metric called the pumping effect, designed to capture overall compression efficacy rather than isolated parameters such as depth or rate. Compression quality in neonatal resuscitation has been difficult to assess, and much of the available evidence relies on simulation or animal models rather than clinical studies. Unlike adult resuscitation, where mechanical devices deliver consistent compressions with machine precision, neonatal resuscitation depends entirely on clinicians, making human factors such as fatigue a central concern. Previous neonatal manikin studies have shown that compression performance deteriorates during prolonged resuscitation.
The benefits of frequent rotation came with an important caveat. The more frequent rotation group showed a reduction in complete chest recoil, a metric that matters because it ensures full decompression and filling of the heart chambers between compressions. Despite this incomplete recoil, the mathematically generated composite score was similar across the groups, and the authors acknowledge that the pumping effect may not reflect improved cardiac output leading to improved perfusion in a newborn infant. This gap between the composite measure and true physiological benefit is a key limitation of the findings.
Practicality is another concern. Frequent rotation of staff during real neonatal resuscitation is likely to be impractical, and the costs may outweigh the presumed benefit. Evidence from animal studies indicates that cardiac compressions can vary significantly and still produce return of spontaneous circulation, and large randomised controlled trials in out-of-hospital adult cardiac arrest found no difference between machine-delivered and human-delivered compressions. These findings suggest that modest reductions in compression quality caused by rescuer fatigue may have less physiological significance than often assumed, although their translation to newborns remains uncertain.
The equipment used in the simulation also limits clinical applicability. The bag valve mask had no positive end-expiratory pressure valve, and the manikin was already intubated. Most newborns who require compressions at birth have suffered perinatal asphyxia, are not intubated, and need effective non-invasive ventilation. A T-piece device that provides PEEP is recommended in well-resourced settings such as Australian hospitals, while self-inflating bags remain important as back-up and in resource-limited settings. Constant PEEP prevents atelectasis and allows functional residual capacity to increase, and maintaining an appropriate face seal is crucial for delivering it, something that frequent provider rotation could compromise further in a non-intubated patient.
Frequent rotation may also disrupt other critical tasks. The study included two staff for each rotation scenario, but in clinical practice frequent role changes could make intubation more difficult and increase the likelihood of accidental endotracheal tube dislodgement even when intubation succeeds. Neonatal resuscitation takes place in a confined space under a radiant warmer, which limits access and visibility for the team, so roles are typically allocated and left unchanged for most of the resuscitation to ensure consistent ventilation, frequent reassessment and smooth progression through the resuscitation algorithm. It remains unclear how frequent role changes would affect this overall progression, even if the compression composite score itself was minimally interrupted.
Any discussion of neonatal chest compressions must also recognise what makes newborn resuscitation fundamentally different from adult practice. The cornerstone of newborn resuscitation is effective ventilation, which clears lung fluid, reduces pulmonary vascular resistance and prevents respiratory failure and subsequent asystole. Resuscitation algorithms worldwide follow a logical stepwise order in which ventilation is prioritised and the patient is reassessed at defined time points before escalation to cardiac compressions. Compressions are therefore a late and rare escalation, applied to a small fraction of the smallest and sickest infants.
The authors frame the work as a thought-provoking step toward understanding clinician fatigue in neonatal cardiac compression efficacy rather than as a practice-changing result. They suggest that the pumping effect metric deserves further study and could improve manikin technology and provide real-time feedback for clinicians. Generalisability challenges remain, and future manikin research will need to assess the impact of frequent rotations on tasks such as non-invasive T-piece ventilation, intubation, venous access and medication administration before any change to resuscitation practice could be considered.
For now, the study adds a measured data point to an underexplored question. It shows that in a controlled simulation setting, rotating compressors every minute preserved depth and frequency over three minutes of resuscitation and improved a novel composite efficacy measure, at the cost of reduced complete chest recoil and with uncertain physiological meaning. Whether that trade-off matters for asphyxiated newborns, whose survival depends first on effective ventilation, remains an open question that only clinical research can answer.
Subject of Research: Effects of clinician rotation frequency on chest compression quality during simulated neonatal resuscitation
Article Title: Beyond fatigue: optimising cardiac compression efficacy for the asphyxiated newborn
Article References: Kariyawasam, U., & Malhotra, A. (2026). Beyond fatigue: optimising cardiac compression efficacy for the asphyxiated newborn. Pediatric Research. https://doi.org/10.1038/s41390-026-05634-9
Image Credits: AI Generated
DOI: 10.1038/s41390-026-05634-9
Keywords: neonatal resuscitation, chest compressions, cardiopulmonary resuscitation, rescuer fatigue, compression quality, pumping effect, chest recoil, perinatal asphyxia, simulation study, manikin, positive end-expiratory pressure, T-piece ventilation
News Source: Harold Sullivan. (November 5, 2026). Frequent rescuer rotation preserves newborn chest compression quality in simulation study. Scienmag.