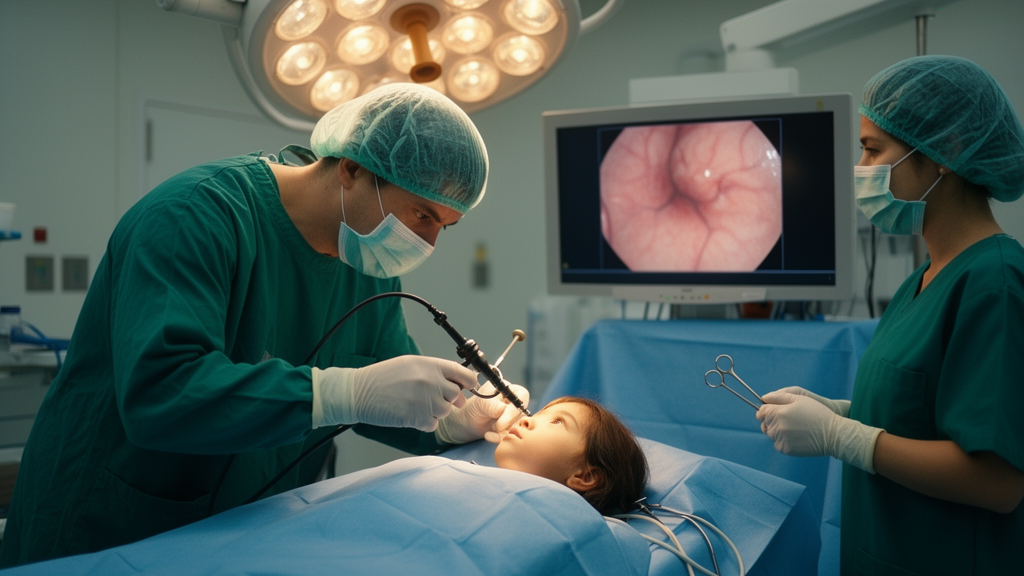
A systematic review and meta-analysis published in BMC Neurology on 27 October 2026 reports that endoscopic third ventriculostomy (ETV), performed alone or combined with choroid plexus cauterization (CPC), achieved treatment success in approximately 65% of children with hydrocephalus across African clinical settings. The pooled treatment success rate was 65.2% (95% confidence interval 59.3%–70.6%), defined as freedom from repeat cerebrospinal fluid diversion during follow-up.
The review, conducted according to PRISMA guidelines, searched PubMed/MEDLINE, EMBASE, CINAHL, African Journals Online and Google Scholar from database inception through 31 July 2026. Eligible studies included children younger than 18 years who underwent ETV alone, ETV combined with CPC, or procedures reported within mixed cohorts in African countries. In total, 27 studies involving 2,808 children were included in the systematic review, of which 24 studies involving 2,724 children contributed to the quantitative synthesis. Across the meta-analysis, 1,609 children achieved treatment success.
Sex was reported in 19 of the 27 included studies; among the 1,279 participants with sex-specific data, 762 were male and 517 were female, corresponding to 59.6% male. Postoperative complications and mortality were assessed separately from the primary outcome, although the abstract does not report their pooled estimates.
Subgroup analyses showed pooled treatment success rates of 67.8% (95% CI 56.9%–77.0%) for ETV-alone cohorts, 65.6% (95% CI 47.8%–79.9%) for ETV/CPC cohorts, and 64.5% (95% CI 54.6%–73.4%) for mixed-procedure cohorts. The confidence intervals overlapped substantially, providing no clear evidence of a difference in treatment success between ETV alone and ETV/CPC. The authors emphasise that these procedure-specific estimates were derived largely from observational studies and indirect comparisons, so the available evidence does not demonstrate a definitive advantage of ETV/CPC over ETV alone.
Between-study heterogeneity was substantial, with I² of 85.9% and τ² of 0.268, and the 95% prediction interval ranged from 39.7% to 84.2%. This wide prediction interval indicates that outcomes vary markedly across clinical environments, meaning that an individual setting could plausibly see success rates anywhere within that range. Heterogeneity was assessed using Cochran’s Q, I² and τ², and study-level proportions were pooled with a DerSimonian–Laird random-effects model following logit transformation.
In a leave-one-out sensitivity analysis, pooled estimates ranged from 63.3% to 66.5%, indicating that no individual study disproportionately influenced the result. However, funnel-plot asymmetry and Egger’s regression test suggested possible small-study effects (intercept 2.26, standard error 0.81; p = 0.011), a finding the authors say should be interpreted cautiously because of the substantial clinical and methodological heterogeneity. Risk of bias was evaluated using ROBINS-I for non-randomized studies and RoB 2 for randomized trials, and prespecified subgroup analyses were performed according to procedure category and risk of bias.
The review notes that treatment outcomes vary across clinical settings and that the comparative effectiveness of ETV alone versus ETV/CPC has remained uncertain, which motivated the synthesis of the available African evidence.
The authors conclude that ETV with or without CPC was associated with an overall treatment success rate of approximately 65% among children with hydrocephalus in African settings, but they stress that the considerable heterogeneity and wide prediction interval limit generalisability. They call for standardized definitions of treatment success, longer follow-up, multicenter prospective studies, and adequately powered head-to-head randomized trials to establish comparative effectiveness and improve the generalizability of recommendations across Africa. Until such trials are completed, the pooled estimate offers a broad benchmark for expected outcomes rather than a basis for choosing between the two procedures.
Subject of Research: Outcomes of endoscopic third ventriculostomy with or without choroid plexus cauterization for paediatric hydrocephalus in Africa
Article Title: Outcomes of endoscopic third ventriculostomy with or without choroid plexus cauterization in paediatric hydrocephalus management in Africa: a systematic review and meta-analysis
Article References: Shafik, K., Onen, J., Muhumuza, M. E., Bongomin, F., Ronald, O., Lekuya, H. M., & Kamabu, L. K. (2026). Outcomes of endoscopic third ventriculostomy with or without choroid plexus cauterization in paediatric hydrocephalus management in Africa: a systematic review and meta-analysis. BMC Neurology. https://doi.org/10.1186/s12883-026-05442-y
Image Credits: AI Generated
DOI: 10.1186/s12883-026-05442-y
Keywords: hydrocephalus, endoscopic third ventriculostomy, choroid plexus cauterization, paediatric neurosurgery, systematic review, meta-analysis, Africa, treatment success, cerebrospinal fluid shunting, heterogeneity, BMC Neurology, Outcomes
News Source: Harold Sullivan. (October 27, 2026). Endoscopic third ventriculostomy succeeds in about 65% of African children with hydrocephalus. Scienmag.