Assisted-reality remote supervision of routine stroke unit ward rounds achieved full technical completion without major failure while matching conventional bedside care in diagnostic agreement, according to findings from a prospective randomized pilot study conducted by researchers at the Department of Neurology at University Hospital Carl Gustav Carus in Dresden, Germany.
Telemedicine has established a widespread presence in hyperacute stroke management, yet research examining telemedical supervision during routine inpatient stroke unit care has remained limited. To address this evidence gap, investigators designed the STROKE-AR trial to evaluate both the technical feasibility and the clinical integration of assisted-reality technology during daily inpatient rounds.
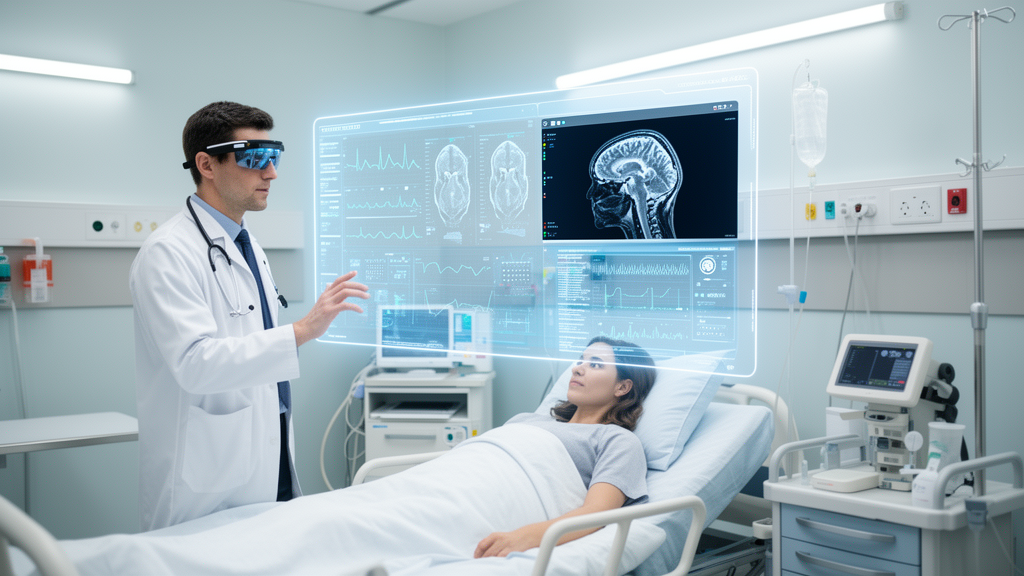
The trial evaluated routine inpatient ward rounds randomized to either assisted-reality remote supervision or conventional on-site supervision. During sessions assigned to the assisted-reality intervention, bedside physicians donned a head-mounted device that established continuous, first-person audiovisual transmission with a remote board-certified stroke neurologist who directed and observed the clinical encounter.
The study established feasibility as its primary endpoint, defined specifically as the successful execution and completion of assisted-reality ward rounds without major technical failure. Secondary endpoints encompassed technical performance, overall ward round duration, interrater reliability on the National Institutes of Health Stroke Scale, System Usability Scale ratings, and questionnaire-based measures of workflow integration and perceived clinical support.
A total of twelve ward rounds involving 45 patients with suspected acute stroke were analyzed across the study arms, split evenly into six rounds per group. Within this cohort, 20 patients received assisted-reality remote supervision, while 25 patients underwent standard bedside supervision. Assisted-reality supervision met the primary feasibility endpoint by completing all six assigned rounds without encountering any major technical failure.
Neurological evaluation fidelity remained consistent across both supervision modalities when compared against independent reference examinations. Agreement between ward round assessments and reference National Institutes of Health Stroke Scale scores was good to excellent, yielding an intraclass correlation coefficient of 0.882 with a 95 percent confidence interval of 0.726 to 0.952 for assisted reality, compared to 0.932 with a 95 percent confidence interval of 0.853 to 0.969 for conventional bedside supervision.
Ward round timing showed modest differences between modalities, with a median duration per patient of 7 minutes and an interquartile range of 5 to 9.5 minutes in the assisted-reality group, compared to a median of 5 minutes and an interquartile range of 4 to 8 minutes under conventional supervision. This translated to a cluster-adjusted mean difference of 1.5 minutes, with a 95 percent confidence interval spanning minus 1.2 to 4.2 minutes.
Usability and clinician satisfaction metrics showed positive acceptance from participating medical staff. Residents recorded a median System Usability Scale score of 66.3 with an interquartile range of 50 to 72.5, while supervising stroke neurologists reported a median score of 63.8 with an interquartile range of 50 to 70. Questionnaire-based evaluations additionally demonstrated favorable ratings regarding seamless workflow integration and perceived clinical support during patient encounters.
The authors concluded that assisted-reality remote supervision of routine stroke unit ward rounds is technically feasible and provides reliable neurological assessments that align closely with independent reference evaluations. Given the pilot scope of the trial, the researchers noted that larger randomized investigations are needed to fully evaluate the intervention’s impact on ward round duration and long-term clinical patient outcomes.
By establishing continuous first-person audiovisual transmission between bedside physicians wearing head-mounted equipment and a remote board-certified stroke neurologist, the trial evaluated whether telestroke practices could effectively expand into everyday inpatient stroke unit care. The intervention successfully completed all six allocated rounds without encountering major technical failures, confirming that supervising neurologists could observe clinical assessments remotely while maintaining dependable audiovisual interaction throughout the bedside encounter.
To verify diagnostic consistency across both supervision modalities, the study design evaluated interrater reliability by comparing ward round findings directly against independent reference assessments on the National Institutes of Health Stroke Scale. Although the cluster-adjusted difference in patient round duration remained modest, the investigators highlighted that this prospective pilot study focused primarily on demonstrating feasibility, underscoring that larger randomized trials will be essential to establish definitive impacts on clinical outcomes and hospital workflow integration.
Subject of Research: Assisted-reality remote supervision of routine stroke unit ward rounds
Article Title: STROKE-AR: a randomized pilot study of assisted reality-supported remote supervision of stroke unit ward rounds
Article References: Schoene, D., Arndt, M., Emmerich, J., Nicklas, M., Holzmueller, K., Diel, N. J., Stuckart, I., Huttner, H. B., Siepmann, T., & Barlinn, K. (2026). STROKE-AR: a randomized pilot study of assisted reality-supported remote supervision of stroke unit ward rounds. Frontiers in Digital Health, 8, Article 1963050. https://doi.org/10.3389/fdgth.2026.1963050
Image Credits: AI Generated
DOI: 10.3389/fdgth.2026.1963050
Keywords: assisted reality, stroke unit, ward rounds, telemedicine, telestroke, acute stroke care, remote supervision, National Institutes of Health Stroke Scale, System Usability Scale, interrater reliability, head-mounted devices, inpatient stroke care, clinical feasibility, audiovisual transmission, neurological assessment, randomized pilot study
News Source: Cassandra Pierce. (November 18, 2026). Assisted-Reality Remote Supervision Proves Feasible for Routine Stroke Unit Ward Rounds. Scienmag.