


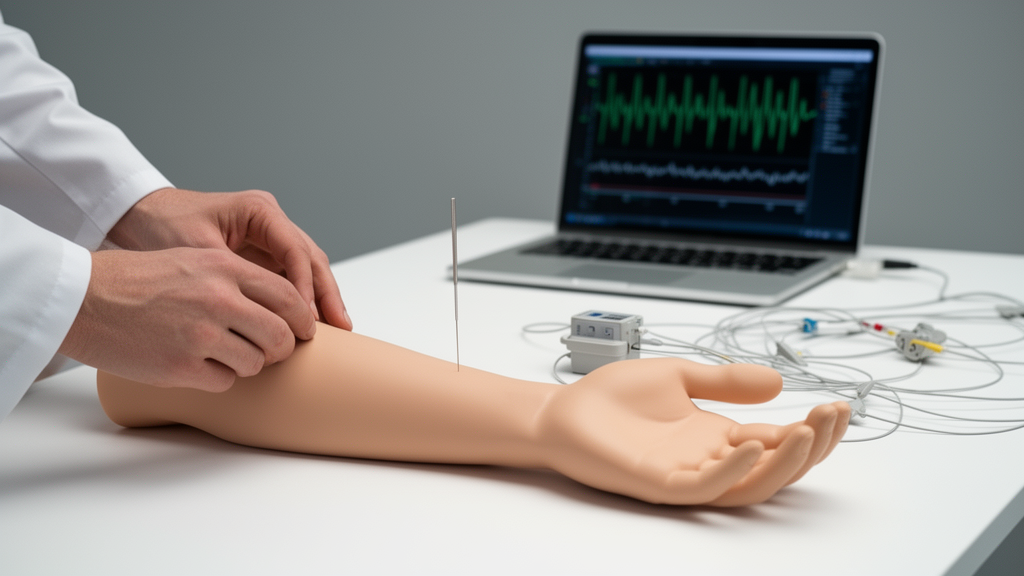
Acupuncture has long lived in a gray zone between clinical practice and craft: two practitioners needling the same point may deliver wildly different doses without either realizing it. A new comment article published in the journal Chinese Medicine argues that this variability is no longer an unavoidable fact of tradition. Drawing together recent studies of dose, needling technique, patient feedback, and emerging biomarkers, its authors propose a closed-loop framework for “precision acupuncture” in which every stage of treatment—what is delivered, how it is delivered, and how the patient responds—becomes a measurable quantity.
The input stage defines the dose of treatment, mainly in terms of stimulation intensity, and translates traditional diagnostic reasoning into a small set of measurable manipulation parameters. The process stage concerns how that stimulation is physically delivered, how it can be quantified through kinematic metrics, and how it can be taught through sensorimotor training. The control stage uses the sensation known as deqi as a real-time feedback signal, while candidate pretreatment biomarkers are considered as feedforward modifiers for initial dose selection.
The dose question sits at the heart of the proposal. Acupuncture dose can be broken down into three components: the number of needles used, the frequency and cumulative count of sessions, and stimulation intensity. According to the authors’ earlier systematic analysis, needle number and treatment frequency did affect outcomes, but their individual contributions were smaller and less consistent than that of stimulation intensity, and the two tended to interact with intensity rather than act independently. Because most trials change several parameters at once, a formal weighting of each factor is not yet possible from the available data. The authors therefore treat stimulation intensity as the primary, but not sole, determinant of dose, capturing the amplitude and frequency of manipulation, retention time, and insertion depth in a single adjustable input.
That framing also gives traditional concepts a quantitative reading. Tonification and sedation—techniques corresponding to deficiency and excess patterns in traditional diagnosis—can be understood as two ends of a stimulation-intensity spectrum. Quantitative studies of practitioners show that sedation-oriented manipulations tend to involve larger rotation amplitudes, higher movement frequencies, and longer continuous periods of manipulation than tonification. In rough terms, sedation is generally delivered with rotation amplitudes above about 90 degrees and manipulation frequencies over roughly 2 hertz, sustained for longer stretches, whereas tonification uses smaller amplitudes below about 90 degrees, frequencies on the order of 1 hertz or less, shorter continuous manipulation, and a shallower, slower lifting–thrusting motion. The authors caution, however, that universally validated cutoffs for manipulation amplitude or frequency have not yet been established.
Making such parameters auditable requires a validated physical interface, and this is where phantom acupoints enter the picture. Usually made from agarose gel, these phantoms can be tuned by changing the gel concentration to reproduce the mechanical forces and the characteristic “needle grasp” of different human acupoints. They have proved a useful teaching tool: phantom-based programs measurably improve the basic technical skills of novice students, and the phantoms offer an inexpensive, portable, and ethically uncomplicated way to rehearse depth control and timing before a trainee ever touches a patient.
On top of validated phantoms, motion- and force-sensing technologies can record displacement, rotation, frequency, and force continuously during manipulation. A striking pattern emerges from these analyses: practitioners differ markedly from one another but remain strongly consistent within themselves, so that every practitioner exhibits a stable motion “signature.” This combination of high between-practitioner variability and strong within-practitioner reproducibility helps explain why acupuncture has long been regarded as an art—and why standardization has been so difficult. Three-dimensional motion tracking breaks complex hand movements down into sinusoidal waveforms defined by amplitude and frequency, producing digital signatures of expert technique that can support empirical training and intelligent systems, including robot-assisted devices that reproduce expert manipulations while monitoring motion and force, and mixed-reality platforms combining virtual avatars with haptic feedback.
Machine-learning methods push this quantification further. Vision-based deep learning and three-dimensional hand-pose estimation can classify manipulation type and estimate amplitude and frequency in real time, providing immediate feedback on consistency and on deviations from an expert reference. The same data stream can also generate a structured, time-stamped record of each treatment automatically, so practitioners could document intensity-related parameters as an auditable clinical record without manual note-taking. A concrete training example is the Acupuncture Manipulation Education System, which tracks needle movement and displays the learner’s trajectory as it is generated, superimposed on an expert waveform template, so that error is displayed visually and can be corrected quickly. Novices trained with this system improve their motion fidelity and reduce error on phantom acupoints—though whether these gains transfer to human needling has not yet been established.
The control stage of the loop rests on deqi, the heaviness, soreness, or distension that patients report during treatment. The authors are careful to position it as a response signal rather than a dose component: it guides real-time adjustment of amplitude, frequency, and duration during a session. Clinical and neurophysiological studies tie appropriate deqi to a greater chance of symptom improvement, especially in pain and in autonomic or cardiovascular conditions, and its presence, quality, and time course track with manipulation parameters and with activation of limbic–paralimbic–neocortical networks involved in interoception and affective processing. In some conditions a shorter deqi latency has been linked to faster improvement, suggesting its timing may index how sensitive a given patient is to stimulation.
Beyond within-session feedback, the article surveys four classes of candidate biomarkers that might predict responsiveness before treatment begins: gut microbiome profiles, neuroimaging-based markers, inflammatory cytokine levels, and circulating microRNA panels. Early reports link baseline microbial taxa to response in postpartum depression, pre-treatment MRI features to outcomes in migraine and mild traumatic brain injury, cytokine levels to pain responsiveness, and microRNA signatures to chronic pain severity. But the authors stress that these biomarkers remain exploratory: most studies are small and single-center, and no trial has yet shown that biomarker-guided dosing beats experienced clinical judgment. Multi-omics assays and advanced neuroimaging remain costly, depend on specialized equipment and analytic expertise, and have turnaround times poorly suited to point-of-care decisions. Within the framework they are best regarded as feedforward modifiers that may one day help define an initial dose range or stratify selected patients, not as routine tests.
The authors are equally candid about the limits of the framework as a whole. A fully closed-loop clinical system has not yet been achieved: the kinematic tools have mostly been validated on phantoms rather than patients, the predictive biomarkers are still at an early stage, and no controlled trial has shown that quantitative, feedback-guided dosing produces better outcomes than the judgment of an experienced practitioner. It also remains unclear how specific stimulation parameters map onto physiological responses and clinical effects, and whether closed-loop, biomarker-guided acupuncture can actually improve clinical outcomes is an open question the authors themselves pose. They present the framework, therefore, as a research agenda that complements clinical expertise with measurement rather than as an established standard of care. Even so, the pieces they assemble—phantom models, kinematic monitoring, sensor-based feedback, and deqi-centered titration—already make parts of the loop feasible, pointing toward a practice in which the ancient art of the needle is documented, taught, and adjusted with the precision of an engineered system.
Subject of Research: A proposed closed-loop framework for quantifying acupuncture dose, manipulation technique, and patient feedback in precision acupuncture research.
Article Title: From art to metrics: a closed-loop framework for quantifying dose, manipulation, and feedback
Article References: Tang, W.-C., Yoon, D.-E., & Chae, Y. (2026). From art to metrics: a closed-loop framework for quantifying dose, manipulation, and feedback. Chinese Medicine, 21(1), Article 221. https://doi.org/10.1186/s13020-026-01492-z
Image Credits: AI Generated
DOI: 10.1186/s13020-026-01492-z
Keywords: acupuncture, precision acupuncture, stimulation intensity, deqi, kinematic metrics, phantom acupoints, sensorimotor training, biomarkers, dose-response, motion tracking, machine learning, closed-loop control
News Source: Ophelia Keating. (October 29, 2026). Acupuncture Meets the Machine: A Closed-Loop Plan to Quantify Every Needle Move. Scienmag.



