A 21-year-old man with a giant chylous mesenteric cyst required resection of 18 cm of small bowel because the cyst was tightly fused to the intestine and shared its mesenteric blood supply, making separation too dangerous. The unusual operation is the central feature of this single case report, which documents a year of progressive abdominal pain and distension, extensive imaging and surgery, a benign pathology result and a reassuring recovery. The findings show how a rare lymphatic malformation can become a large abdominal mass and why the anatomy of a cyst, rather than its size alone, may determine whether it can be removed without sacrificing bowel.
Mesenteric cysts are rare, benign intra-abdominal masses that develop within the mesentery supporting the gastrointestinal tract. They account for approximately one in 100,000 adult hospital admissions, according to the article. Chylous mesenteric cysts, which contain milky lymph-rich fluid, represent about 7% to 9% of mesenteric cysts and arise mainly in the small-bowel mesentery. They are generally attributed to developmental abnormalities of lymphatic vessels, including vessels that do not communicate properly with the lymphatic system. The resulting accumulation of lymph can gradually enlarge the cyst and produce pressure on neighboring organs. Because these lesions are lined by lymphatic endothelium, their lymphatic or lymphangioma type is a histological classification rather than a separate diagnosis.
The patient had no notable medical or surgical history. Over one year, he developed progressive, vague, dull abdominal pain, intermittent distension and a palpable mass that continued to enlarge. He did not experience nausea, vomiting, loss of appetite, fever, weight loss or constipation, illustrating the nonspecific presentation of a large mesenteric cyst. On examination, his abdomen was asymmetrically distended by a smooth, firm, non-tender mass estimated at about 20 × 20 cm in the central abdomen, extending toward the hypogastric region. The mass moved readily when moved perpendicular to the axis of its mesenteric attachment. This movement produced a positive Tillaux’s sign, a physical clue that supported a mesenteric origin and was later corroborated by imaging and surgery.
Laboratory testing, including hemoglobin, electrolytes, liver and kidney function, and the tumor markers CEA and CA 19-9, was within normal reference ranges. Contrast-enhanced CT of the abdomen and pelvis revealed a massive, well-defined, thin-walled, multiloculated cystic mass measuring approximately 20 × 20 × 15 cm. It arose from the small-bowel mesentery and produced pronounced mass effect, displacing adjacent small-bowel loops laterally and superiorly as well as displacing the colon. The internal septa were thin and enhanced slightly after contrast, but there was no calcification, fat attenuation, solid mural component or sign of local invasion. Imaging also showed no mechanical bowel obstruction. These features supported a benign cystic lesion, although CT alone could not reliably distinguish a chylous cyst from an enteric duplication, mesothelial cyst, pseudocyst or cystic neoplasm.
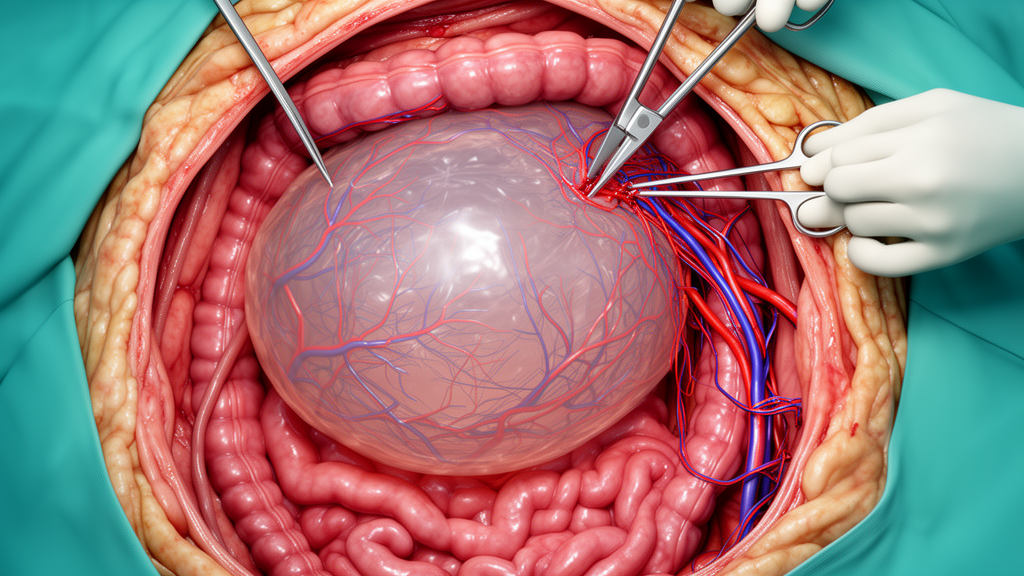
Because the mass was large, progressive and symptomatic, the team proceeded to exploratory laparotomy. Operative findings explained why the operation required more than simple removal of the cyst. A giant multiloculated cyst arose from the small-bowel mesentery and was tightly adherent to the mesenteric border of an adjacent intestinal segment. More importantly, it shared that segment’s mesenteric vascular supply. Enucleation would have required cutting or injuring vessels that perfused the bowel, creating a risk of ischemia and damage to the intestinal wall. The surgeons therefore resected the involved 18-cm small-bowel segment together with the entire cyst and restored intestinal continuity with a primary anastomosis. During surgery, controlled opening of one locule released copious milky chylous fluid, decompressed the cyst and supported a lymphatic origin.
The resected specimen appeared smaller than it had in place because the cyst collapsed after drainage and the bowel contracted after removal. It contained an 11-cm segment of small bowel and a collapsed multiloculated cyst measuring 12 × 7 cm, with walls up to 2 mm thick and no papillary or solid components. Microscopic examination showed a thin fibrocollagenous wall with minimal chronic inflammation and scattered smooth-muscle fibers. A single layer of bland cuboidal or flattened cells lined the cyst without atypia or other worrisome features. The neighboring bowel retained regular villi covered by tall columnar epithelium and showed only minimal nonspecific chronic inflammation. There were no granulomas, atypia or signs of malignancy in the examined tissue.
Immunohistochemistry established the cyst’s lymphatic character and helped exclude other possible diagnoses. The lining cells were strongly positive for the lymphatic endothelial markers D2-40, also known as podoplanin, and CD31. They were negative for calretinin and WT-1, which supported excluding a mesothelial cyst; negative for pan-cytokeratin, which argued against an epithelial lesion; and negative for the estrogen and progesterone receptors, which helped exclude a Müllerian cyst. In combination with the intraoperative chyle, the benign microscopic appearance and this marker profile established the final diagnosis as a chylous mesenteric cyst of lymphangioma type arising in the small-bowel mesentery.
The postoperative course was uneventful. The patient resumed oral intake on the third day after surgery, passed flatus and stool and was discharged in stable condition on day 6. At six months, his abdominal pain and distension had completely resolved. Clinical examination found no palpable intra-abdominal mass or localized tenderness, while abdominal ultrasound showed normal-appearing bowel loops with no fluid collection or cystic lesion. These observations indicated no clinical or ultrasonographic evidence of recurrence during the reported follow-up. The outcome was encouraging, but the authors emphasize that six months is a short surveillance period and cannot establish whether the result will remain durable over the long term.
Complete excision is generally considered the treatment of choice for mesenteric cysts because incomplete removal can increase recurrence risk; aspiration and marsupialization have largely been abandoned. When anatomy permits, enucleation that preserves the bowel is preferred, and a recently reported giant chylous mesenteric cyst in a young adult was managed in that way. This case differed because the cyst and bowel were not separate structures: their shared vascular supply made attempted enucleation unsafe. Bowel resection has also been described when mesenteric vessels are involved or a cyst cannot be cleanly separated from the intestine. For this patient, removing the affected bowel segment was therefore a means of achieving complete cyst excision rather than an avoidable complication.
As a single case with six months of follow-up, the report cannot establish segmental bowel resection as the standard approach for giant chylous mesenteric cysts. Its practical contribution is to show how careful assessment of the relationships among the cyst, bowel and mesenteric vessels can influence the operation. The clinical course also demonstrates that a lymphatic cyst may produce slowly progressive pain and distension for months or longer without systemic or gastrointestinal symptoms. When complete removal is pursued, imaging and operative assessment should establish whether safe separation is possible; if the cyst shares the bowel’s blood supply, resection of the involved segment may be required to avoid vascular injury and ischemia.
Subject of Research: Management of a giant chylous mesenteric cyst sharing vascular supply with adjacent small bowel
Article Title: Giant Chylous Mesenteric Cyst Requiring Segmental Small Bowel Resection in a Young Adult: A Case Report
Article References: Siddique, M. W., Shahzad, M. H., Zameer, R., Javaid, H., Obaid, E., Cheema, M. A., & Dalir, N. (2026). Giant Chylous Mesenteric Cyst Requiring Segmental Small Bowel Resection in a Young Adult: A Case Report. Clinical Case Reports, 14(10), Article e73762. https://doi.org/10.1002/ccr3.73762
Image Credits: AI Generated
DOI: 10.1002/ccr3.73762
Keywords: chylous mesenteric cyst, lymphangioma, small-bowel surgery, mesenteric vessels, lymphatic malformation, abdominal mass, contrast-enhanced CT, segmental bowel resection, case report, six-month follow-up, Giant, Chylous
News Source: Ophelia Keating. (October 21, 2026). Shared Blood Vessels Forced Resection of Giant Chylous Mesenteric Cyst. Scienmag.