A retrospective imaging investigation led by researchers at the University of Iowa has identified distinct geometric patterns in the thoracic aorta that precede acute type A aortic dissection, revealing that longitudinal elongation occurs independently of the severe radial enlargement traditionally used to guide preventive surgical intervention. Current clinical practice relies predominantly on a maximum thoracic ascending aorta diameter threshold of 5.5 centimeters to trigger prophylactic surgical replacement, yet clinical registries demonstrate that most dissections occur below this cutoff. In the newly reported cohort, all patients who developed acute dissection with available prior computed tomography angiography exhibited maximum ascending diameters below 5.5 centimeters, averaging 3.89 ± 0.60 centimeters, while simultaneously demonstrating disproportionate lengthening of the ascending aorta. By comparing pre-event imaging from thirteen patients who subsequently suffered acute type A dissection against fifty nonaneurysmal controls and sixty-one patients with established thoracic aneurysms, the investigators demonstrated that abnormal longitudinal remodeling distinguishes predissection aortas from both healthy vessels and classical aneurysmal disease.
The study addressed a critical diagnostic limitation in cardiovascular medicine: while elective surgical replacement of thoracic ascending aortic aneurysms carries a low procedural mortality of approximately 3.5 percent, acute type A aortic dissection represents a lethal surgical emergency with mortality exceeding 50 percent. Existing guidelines establish intervention thresholds based on radial diameter measurements, but evidence from large registries, such as the International Registry of Acute Aortic Dissection, indicates that 59 percent of dissections occur at diameters below 5.5 centimeters, and prior series of pre-event scans found 96 percent of patients were below this standard surgical marker. Biomechanical investigations have established that the aorta functions as a complex three-dimensional vessel subject to multiaxial forces, where peak mechanical stress often concentrates along proximal curvatures rather than at the region of maximum caliber. Consequently, the research team examined whether comprehensive multiplanar radiographic phenotyping could detect subtle, multidimensional structural alterations that precede catastrophic dissection, focusing specifically on centerline longitudinal length and regional diameter distributions.
To investigate thoracic morphology across disease states, the authors conducted a single-center retrospective review of 151 consecutive patients presenting for surgical repair of acute type A aortic dissection between January 2019 and December 2024. Among these individuals, thirteen patients (8.6 percent) had undergone diagnostic chest computed tomography angiography within three years prior to their dissection, with a median interval of 165 days and a range between 29 and 868 days. Scans from this predissection group were collected from regional referring facilities across a largely rural catchment area alongside institutional scans. For comparative analysis, fifty control subjects who had undergone chest computed tomography angiography for non-aortic indications and sixty-one surveillance patients with thoracic ascending aortic aneurysms defined by a maximal diameter of at least 4.5 centimeters were selected from the same operating period. Patients presenting with bicuspid aortic valves, previous cardiac surgery, or active acute aortic syndromes on baseline examinations were systematically excluded across all cohorts to isolate primary morphometric relationships.
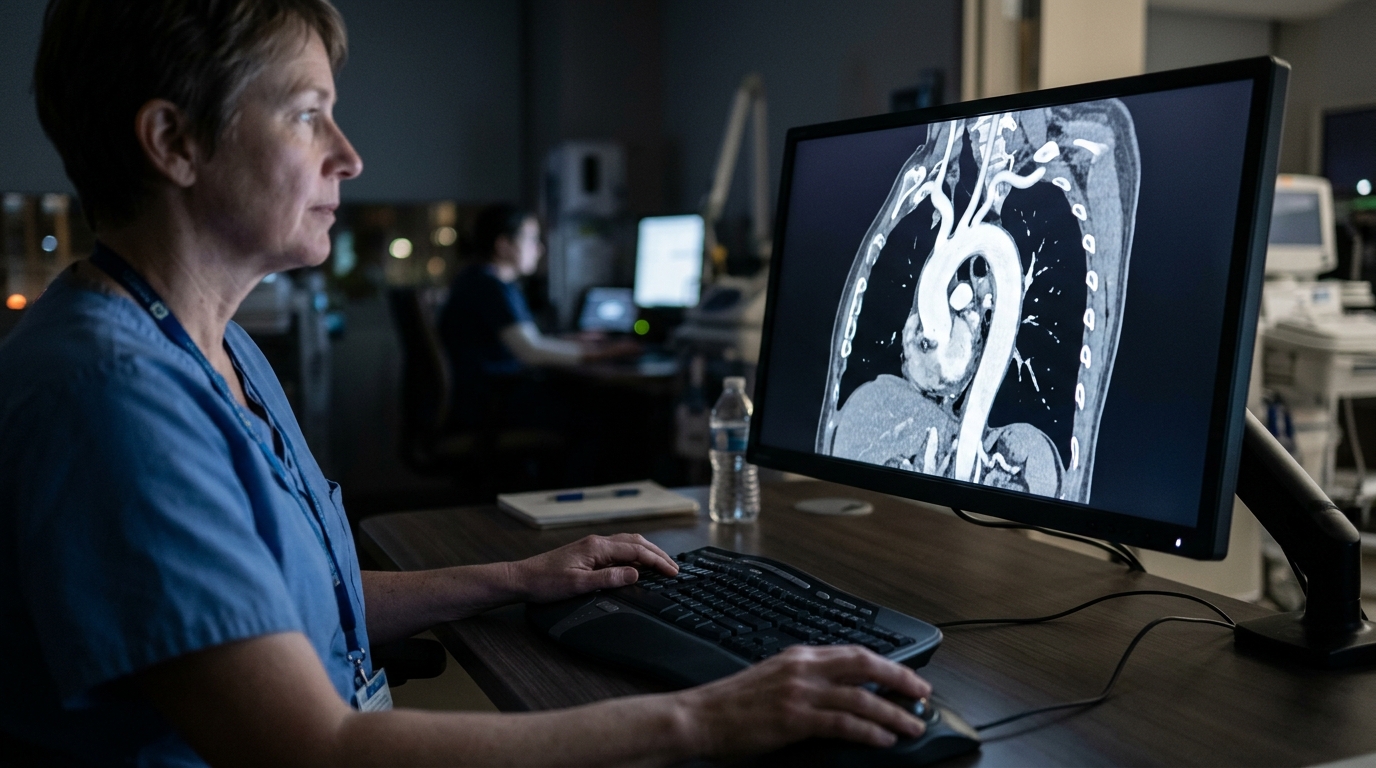
Radiographic assessment was conducted using multiplanar reconstructions and three-dimensional visualization on a dedicated Vitrea Advanced Visualization workstation. Each study was evaluated retrospectively by two radiology fellows and a board-certified thoracic radiologist possessing twenty-three years of specialized experience. Contrast-enhanced helical scans were reconstructed at slice thicknesses of 1.0 to 3.0 millimeters using standard vascular kernels, and semiautomated intensity thresholding was utilized to segment the vessel lumen from the aortic root to the diaphragm, or down to the iliac bifurcation when extended coverage was available. Three-dimensional vascular centerlines were derived to permit standardized double-oblique cross-sectional measurements perpendicular to the centerline axis. Outer-to-outer wall diameters were recorded at specific anatomical levels, including the coronary cusps, sinotubular junction, mid-aortic arch within zone 1, mid-descending thoracic aorta, and the level of the diaphragm. Maximum ascending diameter was measured from the sinotubular junction to the origin of the innominate artery, while ascending aortic length was quantified along the central luminal pathway between the sinotubular junction and the base of the right brachiocephalic artery.
To verify measurement consistency across varying anatomical scales, the team performed a blinded interobserver reproducibility evaluation in seventy-two accession-matched patient pairs encompassing twenty-five controls, forty aneurysm patients, and seven predissection scans. Independent readings by two observers demonstrated excellent reproducibility across all morphologic variables, with two-way absolute agreement single-measure intraclass correlation coefficients ranging from 0.97 to 1.00. The primary metric of ascending aortic length relative to maximum diameter achieved an intraclass correlation coefficient of 0.99 with a 95 percent confidence interval between 0.98 and 0.99. Bland-Altman mean bias assessments and coefficients of variation further confirmed consistent centerline tracking across normal, dilated, and elongated geometries. Statistical analyses were executed in Python using scikit-learn, NumPy, SciPy, and statsmodels, applying one-way analysis of variance with post hoc Tukey honest significant difference tests for continuous measures, alongside chi-square and Fisher exact testing for demographic proportions.
Analysis of absolute dimensions documented striking differences in both radial dilation and longitudinal elongation across the three experimental groups. Control patients presented a mean maximum ascending diameter of 3.11 ± 0.30 centimeters and an ascending aortic length of 6.38 ± 0.75 centimeters. In the aneurysm cohort, maximal diameter reached 4.96 ± 0.52 centimeters, accompanied by an ascending length of 9.03 ± 1.08 centimeters. In the predissection cohort, the maximum ascending diameter averaged 3.89 ± 0.60 centimeters, with the highest individual measurement reaching only 4.9 centimeters, yet ascending aortic length measured 10.73 ± 1.41 centimeters. This longitudinal dimension in predissection vessels was significantly longer than both control and aneurysm cohorts at a significance level of P < 0.001.
To separate regional morphologic patterns from global vessel caliber, the authors normalized all segmental measurements to each individual patient’s maximum ascending diameter, producing dimensionless ratios across the thoracic segments. This primary hypothesis-driven analysis demonstrated that the ratio of ascending aortic length to maximum ascending diameter differed significantly across every pairwise group comparison (all P < 0.001). The ratio averaged 2.06 ± 0.22 in the control cohort, 1.83 ± 0.21 in the aneurysm group, and 2.80 ± 0.50 in the predissection group. The lower ratio observed in aneurysm patients reflected substantial radial enlargement that exceeded concurrent elongation, creating a diffusely widened vessel profile. Conversely, the markedly elevated ratio in predissection subjects underscored a geometric state dominated by disproportionate longitudinal stretching relative to moderate transverse widening. Segmental diameter ratios at the sinotubular junction, arch, descending aorta, and diaphragm further corroborated that predissection pathology remained focal to the proximal thoracic segment.
Receiver operating characteristic curve analyses evaluated the discriminatory capacity of the ascending length-to-diameter ratio using stratified bootstrap resampling with 2,000 iterations. For distinguishing predissection aortas from healthy controls, the ratio achieved an area under the curve of 0.94 with a 95 percent confidence interval of 0.87 to 0.99. An optimal cutoff value of 2.40 yielded an 84.6 percent sensitivity and 94.0 percent specificity. When differentiating predissection vessels from thoracic aneurysms, the metric achieved an area under the curve of 0.99 with a 95 percent confidence interval of 0.97 to 1.00, where a cutoff of 2.12 produced 100 percent sensitivity and 93.4 percent specificity. Differentiating aneurysms from normal controls yielded an area under the curve of 0.79 with a 95 percent confidence interval of 0.70 to 0.87 at a threshold of 1.92, emphasizing that the metric specifically isolated the elongated predissection configuration rather than generic vessel expansion.
Because patient age and biological sex distributions varied across cohorts, researchers performed an analysis of covariance across 123 patients with complete anthropometric records to test whether demographic confounders accounted for the morphologic findings. In the multivariable model adjusting for age, sex, and height, study group remained the dominant predictor of both ascending length and the length-to-diameter ratio. For ascending aortic length, predissection vessels remained significantly longer than aneurysms by an estimated beta coefficient of +1.92 centimeters (95 percent confidence interval 1.31 to 2.54, P < 0.001), while age exhibited a modest positive association of +0.018 centimeters per year (P = 0.005). For the length-to-diameter ratio, predissection aortas remained significantly higher than aneurysms (beta = +1.00, 95 percent confidence interval 0.83 to 1.16, P < 0.001), with no demographic covariate reaching statistical significance.
Direct evaluation of anatomical deformation at the moment of catastrophic dissection was possible through paired imaging in all thirteen predissection patients who underwent repeat computed tomography during acute presentation. In no patient was a reduction in either parameter observed. Pearson correlation analyses revealed that the magnitude of structural change did not correlate with the elapsed time between scans for either length (r = -0.04, P = 0.90) or diameter (r = -0.01, P = 0.98), though the authors emphasized that pre-event growth and acute intra-dissection deformation cannot be disentangled from interval duration alone. Review of acute scans localized the primary intimal disruption in eleven patients, with nine tears situated in the proximal ascending aorta, one in the mid-ascending segment, and one at the base of the innominate artery.
Synthesizing these findings, the authors proposed that thoracic aortic pathology does not progress along a single linear continuum from normal caliber through uniform aneurysmal dilation to dissection. Instead, ascending aortic dissection appears linked to at least two distinct morphometric phenotypes: a classical aneurysmal manifestation marked by advanced age, diffuse longitudinal and radial dilation extending throughout the thoracic aorta, and lower length-to-diameter ratios; and a predissection phenotype characterized by younger presentation, moderate radial dilation, preserved downstream thoracic dimensions, and profound longitudinal elongation. This disproportionate elongation is hypothesized to increase axial wall tension, exacerbating multiaxial mechanical stress in the proximal curvature where tears predominantly originate. The authors emphasized that predissection aortas do not simply represent early-stage aneurysms but instead reflect a distinct vascular morphology that remains undetected when surveillance protocols focus exclusively on transverse diameters.
The study authors highlighted several methodological limitations inherent to their single-center retrospective design, stating that findings must be viewed as exploratory and hypothesis-generating. The predissection cohort was restricted to thirteen individuals due to the stringent requirement for retrieval of diagnostic-quality cross-sectional imaging prior to sudden dissection, introducing unavoidable selection bias and limiting statistical power. Electrocardiographic gating status could not be verified for imaging performed at outside referring institutions, although institutional scans were uniformly gated. Furthermore, ethical clearance for deidentified imaging restricted access to detailed clinical risk factors, preventing adjustments for systemic hypertension, smoking history, or medical therapies. Relevant three-dimensional variables such as aortic tortuosity, arch angulation, and total luminal volume were not included in the primary model, and the derived length-to-diameter thresholds lack independent prospective validation. The researchers concluded that multicenter studies will be necessary to confirm whether incorporating automated centerline length measurements into standard radiological reporting can enhance risk stratification before acute dissection occurs.
Subject of Research: Radiographic morphology and ascending aortic elongation preceding acute type A aortic dissection
Article Title: Radiographic phenotyping of healthy and diseased aortas
Article References: Boudreaux, J. C., Chaudhry, S., Yasmine, N., Dhakal, S., Zhang, H., Sonka, M., Wahle, A., Vigmostad, S., Ramachandra, A. B., Thiel, W. H., Smith, L. E., Streeter, J., Bello, R. M., & Singhal, A. K. (2026). Radiographic phenotyping of healthy and diseased aortas. Journal of Cardiovascular Imaging, 34(1), Article 39. https://doi.org/10.1186/s44348-026-00086-5
Image Credits: AI Generated
DOI: 10.1186/s44348-026-00086-5
Keywords: acute type A aortic dissection, ascending aortic length, computed tomography angiography, thoracic aortic aneurysm, sinotubular junction, maximum ascending diameter, centerline reconstruction, vascular morphology, aortic phenotyping, receiver operating characteristic, area under the curve, biomechanical wall stress, intimal tear, interobserver reproducibility, intraclass correlation coefficient, analysis of covariance, vitrea workstation, multiaxial stress
News Source: Ophelia Keating. (November 17, 2026). Aortic Elongation Distinguishes Acute Dissection Risk Below Standard Diameter Thresholds. Scienmag.