


Endurance athletes often develop hearts that look, on a resting scan, remarkably like the early stages of a serious disease. Their left ventricles enlarge with years of training, and a substantial minority show a resting ejection fraction in the 45 to 54 percent range — numbers that would raise concern in a non-athlete. Distinguishing this physiological remodelling from early dilated cardiomyopathy (DCM) is one of the most consequential dilemmas in sports cardiology, because the two diagnoses point in opposite directions: one means reassurance and continued sport, the other means withdrawal from intensive exercise, surveillance and, potentially, life-saving therapy. A new study published in Echo Research & Practice reports that adding a single measurement — how the ejection fraction behaves between submaximal and peak exercise — nearly eliminates the diagnostic blind spot left by the current standard test.
The research, led by a team at St George’s University Hospital and the Royal Brompton Hospital in London, enrolled 182 athletic individuals between August 2021 and July 2023. The cohort comprised three groups: 62 control athletes with enlarged left ventricles but normal resting ejection fractions, 58 individuals with athletic dilated cardiomyopathy, and 62 so-called grey zone athletes whose dilated ventricles and mildly depressed ejection fractions made them indistinguishable from early disease on resting imaging alone. All participants were asymptomatic and exercised vigorously for more than four hours per week, and the control and DCM groups were matched for age and sex.
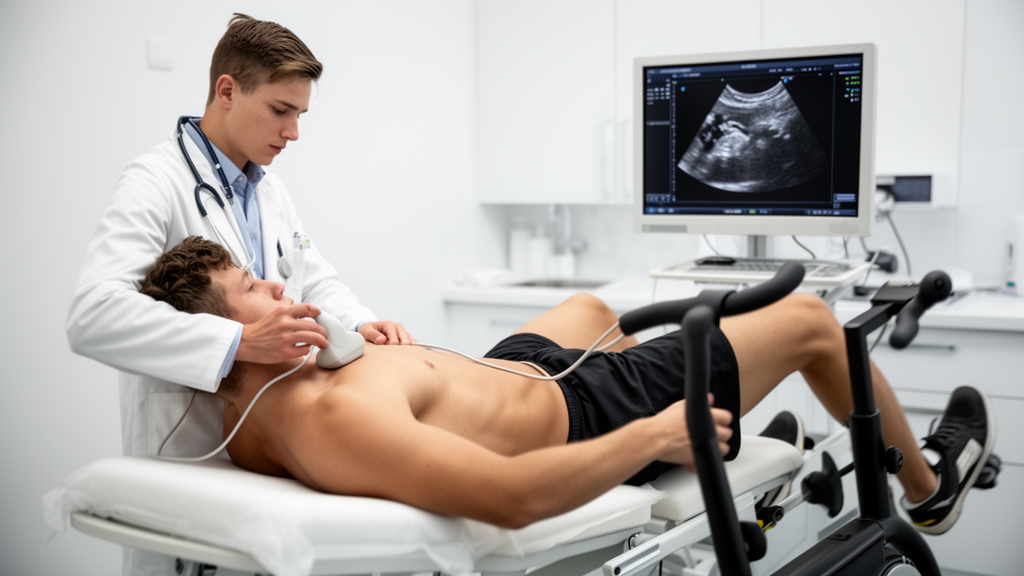
Each participant underwent stress echocardiography on a semi-recumbent bicycle, with images acquired at rest, at 60 percent and 80 percent of age-predicted maximal heart rate, and at peak exercise. The researchers evaluated two indices of contractile reserve: the traditional increase in ejection fraction from rest to peak exercise, and a novel measure — whether the ejection fraction continued to rise from the 80 percent stage to peak exertion. The European Society of Cardiology currently regards an increase of at least 10 percent from rest to peak as evidence of good myocardial reserve, and this threshold is widely applied in clinics to separate athlete’s heart from cardiomyopathy.
The results confirmed the value of that conventional measure but also exposed its limits. Resting left ventricular dimensions were similar across all three groups, and control athletes had higher resting ejection fractions than the other two cohorts (62.1 percent versus 52.1 percent in grey zone athletes and 53.1 percent in those with DCM). From rest to peak exercise, control and grey zone athletes augmented their ejection fractions by 21 percent and 19.2 percent respectively, compared with just 4.9 percent in the DCM group. Nearly all control athletes (98.3 percent) and 90.3 percent of grey zone athletes achieved the 10 percent threshold, whereas only 20.6 percent of athletic DCM individuals did so.
The critical finding emerged at the submaximal stage. Control athletes increased their ejection fraction by a mean of 7.5 percent between 80 percent of maximal heart rate and peak exertion, and grey zone athletes by 3.8 percent, while individuals with DCM showed a mean decline of 4.3 percent. Although roughly one in five athletic DCM individuals passed the conventional rest-to-peak threshold, only a single individual in that group continued to augment ejection fraction from submaximal to peak exercise. In other words, the failing heart revealed itself not at peak effort but in the final push from high submaximal work to maximal effort, where rising preload appears to reduce contractile efficiency in diseased myocardium, a pattern the authors relate to the Starling relationship.
Combining the two criteria transformed diagnostic performance. Failure to increase ejection fraction by at least 10 percent from rest to peak exercise alone identified DCM with 79.4 percent sensitivity and 98.3 percent specificity. Adding the failure to augment from submaximal to peak exercise raised sensitivity to 98.2 percent while preserving specificity at 98.4 percent. Receiver operating characteristic analysis confirmed the superiority of the combined criterion, with an area under the curve of 0.942 (95 percent confidence interval 0.890 to 0.994), compared with 0.888 for the 10 percent threshold alone. Logistic regression showed both the rest-to-peak change and submaximal-to-peak augmentation were independent predictors of DCM.
The combined index proved robust even in diagnostically awkward subgroups. Among 17 athletic DCM individuals whose left ventricular function had returned to normal after pharmacological treatment, 13 (76 percent) failed to augment from rest to peak exercise, and all 17 were unable to augment from submaximal to peak. Interobserver variability for the ejection fraction change was low, with coefficients of variation between 1.31 and 1.51 percent across the three groups, although the authors caution that this reproducibility reflects offline measurements by experienced echocardiographers on pre-selected high-quality image loops and may be harder to achieve in routine clinical settings.
The study also weighed other proposed discriminators and found them wanting. Global longitudinal strain, measured by speckle-tracking echocardiography, was more negative at rest in control and grey zone athletes than in those with DCM, but the change in strain from rest to peak exercise did not differ between groups — a uniform reduction the authors attribute to the recognised unreliability of speckle-tracking at heart rates above roughly 140 to 150 beats per minute rather than a true physiological decline. Resting strain values, they conclude, would generate many false positives, and exercise strain changes carry no discriminatory value. Among grey zone athletes, the small subgroup with mid-wall myocardial fibrosis on cardiovascular magnetic resonance showed exercise responses no different from those without scarring, with five of six fibrosis cases still achieving normal contractile reserve.
The authors frame the technique as a pragmatic second-line investigation for the grey zone phenotype, noting that exercise cardiovascular magnetic resonance, which has shown similar reserve findings, is not widely available. They also recommend focusing on the change in ejection fraction rather than peak values, since all healthy athletes in this study reached a peak ejection fraction of at least 72 percent, but only 63.2 percent of grey zone athletes and 11.5 percent of those with DCM did so — and lower resting values mean grey zone athletes would need disproportionately greater reserve to hit that peak.
Important limitations temper the findings. The study was cross-sectional, so the grey zone athletes who failed to show adequate reserve may or may not progress to cardiomyopathy; prospective follow-up of this cohort is ongoing. The sample, though larger than previous efforts, remains modest, and participants were predominantly male and white, with only six women in the grey zone group, limiting generalisability to female athletes and other ethnic groups. Genetic testing was not performed on grey zone athletes, and the semi-supine bicycle protocol may not translate directly to centres using treadmill-based imaging. Sex did not influence augmentation among control and grey zone athletes, though males with DCM showed slightly higher rest-to-peak change than females. Within those constraints, the message for clinicians is concrete: a heart that passes the conventional rest-to-peak test may still fail the sterner submaximal-to-peak examination, and adding that final-stage measurement catches virtually every case of athletic dilated cardiomyopathy that the current standard misses.
Subject of Research: Stress echocardiography for distinguishing physiological left ventricular enlargement in athletes from early dilated cardiomyopathy
Article Title: Unravelling the grey zone: submaximal-to-peak stress echocardiography enhances diagnostic accuracy in differentiating early dilated cardiomyopathy from physiological adaptation
Article References: Marwaha, S. K., Basu, J., Bhatia, R., Maclachlan, H., Fyyaz, S., Esteban, M. T. T., Behr, E. R., Finocchiaro, G., Malhotra, A., Prasad, S., Gati, S., Papadakis, M., & Sharma, S. (2026). Unravelling the grey zone: submaximal-to-peak stress echocardiography enhances diagnostic accuracy in differentiating early dilated cardiomyopathy from physiological adaptation. Echo Research & Practice, 13(1), Article 23. https://doi.org/10.1186/s44156-026-00123-5
Image Credits: AI Generated
DOI: 10.1186/s44156-026-00123-5
Keywords: stress echocardiography, dilated cardiomyopathy, athlete's heart, left ventricular ejection fraction, contractile reserve, sports cardiology, grey zone athletes, exercise testing, global longitudinal strain, myocardial fibrosis, diagnostic accuracy, endurance exercise
News Source: Ophelia Keating. (October 30, 2026). Submaximal-to-Peak Stress Echocardiography Improves Detection of Early Dilated Cardiomyopathy in Athletes. Scienmag.



