The retrospective study, published in BMC Surgery, followed 15 patients with neurological deficits for a mean of 27.6 months.
When canal encroachment is severe, or when fragments are inverted so their cortical surface faces the canal, anterior vertebrectomy and fusion is generally recommended. The authors argue that current approaches carry notable limitations and proposed posterior vertebral wedge resection, or pVWR, as a decompression option.
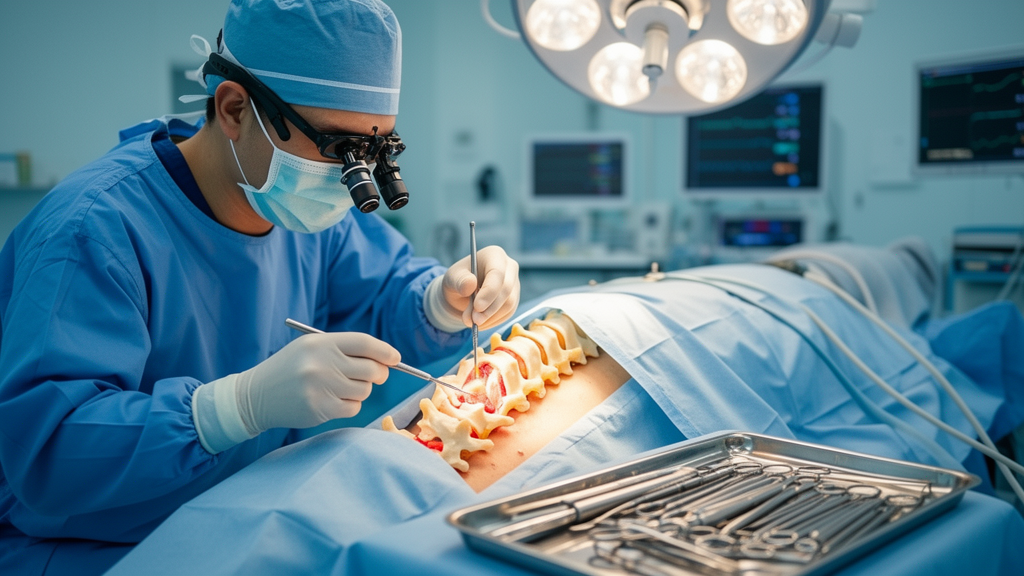
The technique works through a unilateral transpedicular route. Rather than approaching the canal from the front, the surgeon resects a wedge of the damaged vertebral body from behind, creating space to reduce the retropulsed fragments and relieve pressure on the spinal cord and nerve roots while posterior instrumentation stabilizes the column.
The cohort consisted of 15 patients with a mean age of 39.4 years, ranging from 25 to 58, all treated for severe spinal canal stenosis of at least 66 percent encroachment by retropulsed fragments, or canals compromised by reverse cortical fragments. Mean follow-up was 27.6 months, with a range from 9 to 48 months.
Decompression was substantial. The mean traumatic spinal stenosis rate, defined as the proportion of the canal cross-sectional area occupied by fragments, fell from 60.9 percent preoperatively to 0.7 percent postoperatively. Among patients with severe stenosis, the rate dropped from 74.5 percent to zero.
Alignment and height restoration also improved. The Cobb angle changed from 5.8 degrees to minus 8.4 degrees from preoperatively to final follow-up, and the vertebral body compression ratio decreased from 60.5 percent to 8.3 percent.
Neurological and functional outcomes were reported alongside the radiological findings. Twelve patients with incomplete neurological deficits achieved improvement in ASIA grade. The visual analogue scale pain score fell from 8.3 to 1.3, and the Oswestry Disability Index dropped from 84.3 percent to 16.8 percent by the final follow-up.
The operation is demanding. Mean estimated blood loss was 593.3 millilitres with a standard deviation of 293.9, and mean operating time was 258.1 minutes, about 67 minutes standard deviation. Cerebrospinal fluid leakage occurred after surgery in three patients, but no implant failure was recorded.
The authors conclude that although anterior vertebrectomy and fusion remains the general recommendation for burst fractures with severe canal encroachment or inverted retropulsed fragments, satisfactory decompression and neurological recovery can also be achieved with the pVWR technique in such patients.
The team notes the article is being shared early as peer-reviewed, accepted research, and the version is subject to further edits before the final record appears.
Subject of Research: A posterior vertebral wedge resection technique for decompressing severe thoracolumbar burst fractures with neurological deficits
Article Title: Modified posterior spinal decompression via vertebral wedge resection for severe thoracolumbar burst fractures with neurological deficits
Article References: Wu, C., Wang, X., Wang, W., Ning, S., & Chen, C. (2026). Modified posterior spinal decompression via vertebral wedge resection for severe thoracolumbar burst fractures with neurological deficits. BMC Surgery. https://doi.org/10.1186/s12893-026-04305-0
Image Credits: AI Generated
DOI: 10.1186/s12893-026-04305-0
Keywords: thoracolumbar burst fractures, spinal canal stenosis, posterior vertebral wedge resection, spinal decompression, transpedicular approach, neurological deficits, ASIA grade, Cobb angle, retropulsed fragments, BMC Surgery, spinal surgery, Modified
News Source: Ophelia Keating. (October 27, 2026). Wedge resection through the pedicle decompresses severe burst fractures in small series. Scienmag.