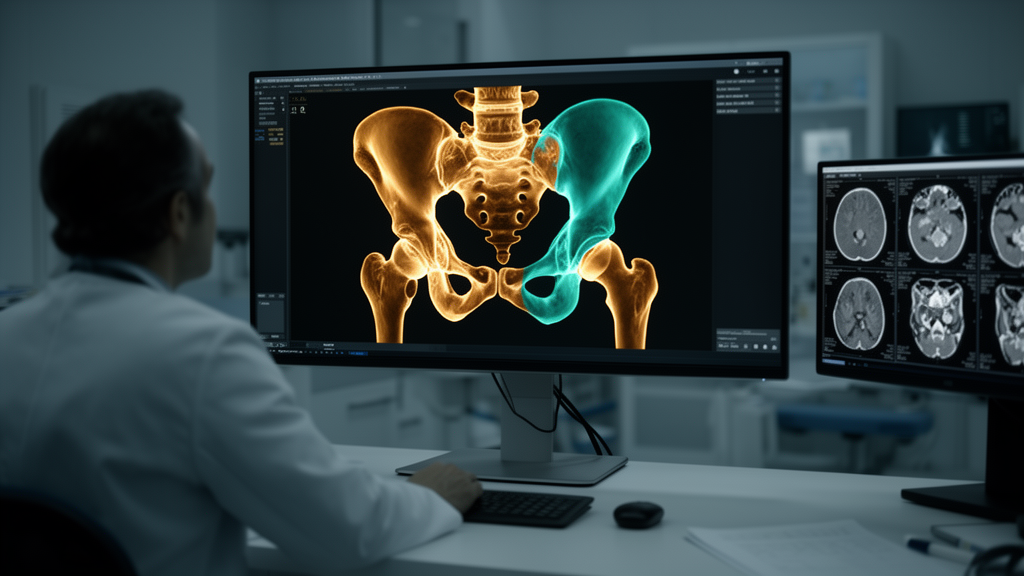
The human pelvis is one of the most anatomically complex structures in the body, a three-dimensional jigsaw of curved bones, weight-bearing columns, and joint surfaces that surgeons must navigate with millimeter precision. Computed tomography is the reference standard for imaging this region, yet the digital tools that automatically analyze pelvic CT scans have largely stopped at the level of whole bones. They can outline the pelvis or the femur as a single object, but the finer surgical subregions—the acetabular roof, the anterior column, the femoral neck—have remained the domain of slow, laborious, and operator-dependent manual contouring. A new study published in BMC Medical Imaging by Mohammed Rashed and colleagues at University Hospital Aachen now describes a rule-based pipeline that closes this gap, automatically dividing pelvic and proximal femoral CT scans into a structured hierarchy of clinically meaningful subregions and anatomical landmarks.
The core idea behind the pipeline is elegantly pragmatic. Rather than training a deep neural network to recognize every fine-grained subregion from scratch—an approach that would require enormous amounts of expert-labeled training data—the researchers built their system on top of an existing whole-bone segmentation tool called TotalSegmentator. That tool first identifies the parent bone structures in a scan. The pipeline then applies a set of fixed, anatomy-driven rules to carve those parent masks into 81 distinct segments, including the iliac columns, the acetabular regions that form the hip socket, and the proximal femoral regions. Because the division follows deterministic anatomical rules rather than learned approximations, the output is reproducible and transparent, and the entire process runs as a one-click operation within 3D Slicer, a widely used open-source platform for medical image analysis.
To test the system, the team retrospectively collected anonymized pelvic CT scans of normal adults and screened 1,316 cases against predefined quality criteria. A total of 757 scans passed the filter and were processed through the pipeline. The primary endpoint of the study was deliberately conservative: instead of simply measuring how well the automated segments matched some ideal, the researchers asked how much manual correction a human expert would actually need to make the outputs anatomically acceptable. In 100 randomly selected cases, every one of the 81 segments was expert-reviewed and corrected wherever necessary, with the frequency of correction serving as the study’s key metric.
The results were striking. Across 8,100 individual segment observations, 93.8 percent were accepted by the expert reviewers without any correction at all. Even more telling, 51 of the 81 segments required no correction in any of the hundred cases examined. When corrections were needed, they clustered tightly in a small number of boundary regions, chiefly the ischium and the femoral neck, where the transition between bones is anatomically subtle. On average, the median correction burden amounted to just 4.5 segments per case—a modest workload compared with the dozens of contours that would otherwise have to be drawn by hand.
Accuracy, computed only on the segments that required correction, told a similarly encouraging story. The median Dice similarity coefficient—a standard overlap metric where 1.0 indicates perfect agreement—reached 0.94 for these corrected segments, indicating that even where the pipeline deviated from expert judgment, the errors were spatially modest rather than gross. A secondary symmetry analysis, which compared corresponding structures on the left and right sides of the pelvis, showed median surface agreement of 90 percent within 2 millimeters and 99.9 percent within 5 millimeters. This bilateral symmetry check matters because the human pelvis is nominally symmetric, and deviations can flag either genuine anatomical variation or segmentation error.
Normal anatomy, of course, is the easy case. The true test of any automated segmentation tool is whether it survives contact with the fractured, deformed, and diseased anatomy that fills real clinical caseloads. To probe this, the researchers assembled a separate 60-case cohort featuring pathological anatomy and compared the pipeline’s output on affected segments against manually segmented ground truth. The pooled median Dice coefficient across affected components was 0.970, a figure that suggests the rule-based approach retains much of its reliability even when fractures or deformities disrupt the expected geometry. Pooled landmark error came in at a median of 5.37 millimeters, and 91.9 percent of manually placed landmark clicks fell inside the automated landmark regions.
The implications for clinical practice and research extend well beyond the numbers. Precise subregional segmentation of the pelvis underpins a remarkable range of interventions: planning total hip arthroplasty, where cup positioning depends on accurate acetabular morphology; managing acetabular fractures, where classification systems depend on identifying which columns and walls are involved; and morphometric studies that map population-level variation in pelvic shape. By converting a raw CT scan into a structured, labeled map in a single click, the pipeline could compress hours of manual contouring into minutes of light review, while preserving exactly the anatomical detail that morphometric analyses and dataset generation require.
The study also highlights a broader trend in medical imaging: the rise of hybrid pipelines that combine learned and rule-based components. Deep learning models excel at the perceptual task of finding organs and bones in noisy images, but they can be brittle at boundaries, inconsistent across cases, and expensive to retrain for new label sets. Deterministic anatomical rules, by contrast, are transparent, cheap, and easy to audit, but they need a reliable starting point. By chaining TotalSegmentator’s learned whole-bone masks into a rule-based subdivision stage, the Aachen team gets the best of both worlds—and, crucially, they quantify the residual human workload rather than hiding it behind a single accuracy score. That honest accounting of the correction burden is what makes the results actionable for clinics deciding whether such a tool is ready for their workflow.
The authors are careful to draw the line between what has been validated and what remains unproven. The pipeline is validated for normal adult anatomy, and its performance held up in an initial pathological-anatomy sample, but the researchers explicitly state that extension to fracture management, deformity correction, or clinical decision-making requires dedicated validation in abnormal anatomy. Fractured pelvises can shatter the geometric assumptions on which any rule-based subdivision depends, and a tool that works beautifully on intact bones cannot simply be assumed to work on a shattered acetabulum. That caveat is not a weakness of the study but a roadmap: the 0.970 pooled Dice in the pathological cohort provides a credible foundation for the larger, fracture-specific validation studies that would need to follow.
For a field where the pelvis has long been described as among the most demanding regions in musculoskeletal imaging, the arrival of a one-click, anatomy-driven subsegmentation tool marks a genuine shift. The work, published open access under a Creative Commons license, emerged from a collaboration between the departments of Orthopaedic Surgery and Diagnostic and Interventional Radiology at University Hospital Aachen, with the team reporting no funding sources or conflicts of interest. If subsequent validation in fractured and deformed anatomy confirms the early promise, the tedious manual contouring that has long been the hidden cost of pelvic surgery planning and morphometric research may finally give way to a workflow in which the computer does the drawing and the surgeon does the deciding.
Subject of Research: Automated anatomy-driven subsegmentation of pelvic and proximal femoral CT into surgical subregions and landmarks
Article Title: Anatomy-driven automated subsegmentation of pelvic and proximal femoral CT into clinically relevant subregions and landmarks
Article References: Rashed, M., Alabdulrahman, H., Westfechtel, S. D., Hildebrand, F., & Truhn, D. (2026). Anatomy-driven automated subsegmentation of pelvic and proximal femoral CT into clinically relevant subregions and landmarks. BMC Medical Imaging, 26(1), Article 454. https://doi.org/10.1186/s12880-026-02753-x
Image Credits: AI Generated
DOI: 10.1186/s12880-026-02753-x
Keywords: pelvic CT, automated segmentation, subsegmentation, proximal femur, acetabulum, anatomical landmarks, 3D Slicer, TotalSegmentator, Dice coefficient, orthopedic surgery, medical imaging, morphometry
News Source: Ophelia Keating. (October 18, 2026). Automated CT Tool Maps the Pelvis Into Surgical Subregions With Minimal Correction. Scienmag.