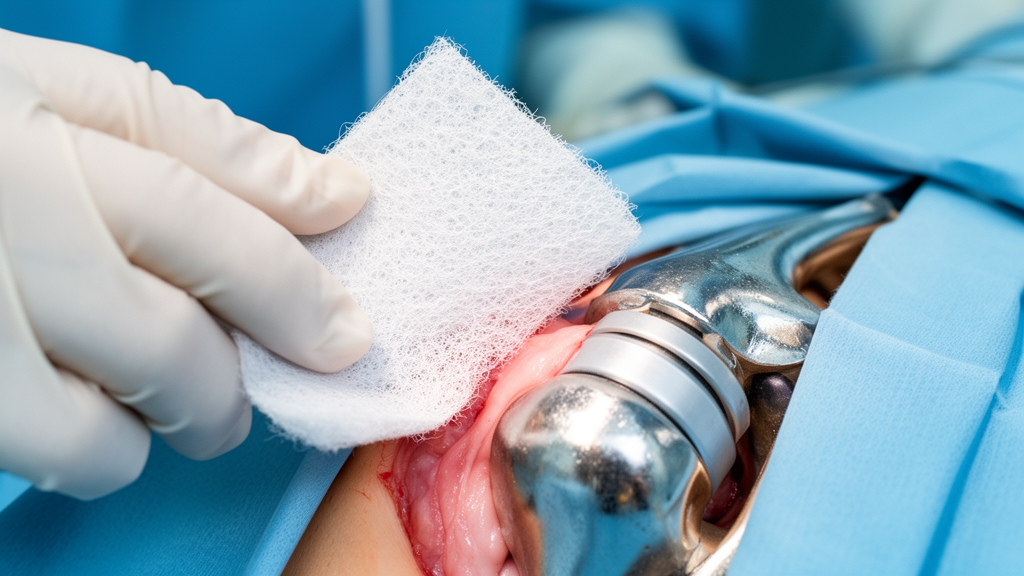
Radiofrequency-tagged surgical sponges, which have previously demonstrated complete sensitivity and specificity in general surgical procedures, encounter specific detection vulnerabilities when deployed during orthopedic total joint arthroplasty, according to a retrospective clinical validation study of 2,251 surgical procedures published in Patient Safety in Surgery. Investigators evaluating procedures performed at Texas Health Resources Clearfork examined discrepancy rates between standardized manual counting protocols and automated radiofrequency wand detection, observing an overall discrepancy rate of 0.13 percent across the operative cohort. The findings indicate that while electronic sponge-tracking tools provide an additional layer of surveillance for preventing retained foreign objects, metallic orthopedic components and bone cement polymerization can directly impede radiofrequency signal transmission and tag functionality.
Retained foreign objects remain among the most consequential yet preventable complications in operative medicine, representing persistent clinical, financial, and legal challenges across health systems. Retained surgical items are formally defined as any surgical material inadvertently left inside an operative patient following procedural completion, with surgical sponges constituting the most frequently retained category across surgical specialties. Because surgical sponges feature soft textures, high pliability, and compact physical dimensions, they can easily become obscured within deep tissue planes or anatomical cavities.
Standard clinical protocols across operating theaters have long relied on systematic manual counts performed audibly and visually by circulating registered nurses and surgical technologists at designated stages of a procedure. At the investigated facility, institutional policies mandated baseline counts before operative entry, intermediate counts during the initial closure of deep anatomical cavities, and final reconciliation counts prior to skin closure, conducted within designated non-distraction zones to limit procedural errors. However, manual counts remain susceptible to human error, particularly during prolonged interventions, emergency cases, or operative sequences involving frequent sponge exchanges. To reduce reliance on purely manual counts, hospitals have increasingly adopted electronic tracking systems, including passive radiofrequency chips embedded within sponge gauze that emit detectable signals when scanned with an external handheld detection wand.
However, orthopedic procedures—particularly total knee arthroplasty and total hip arthroplasty—introduce substantially different physical environments characterized by confined joint spaces, rigid bony retractors, dense cortical bone, and large metallic prosthesis components. With more than 1.3 million joint arthroplasties conducted annually across the United States, determining whether high concentrations of metal and mechanical impaction alter the diagnostic accuracy of radiofrequency wand systems represents an important patient safety objective.
To assess real-world diagnostic concordance, the research team analyzed 2,251 joint arthroplasty procedures conducted between April 30, 2024, and February 28, 2025. The procedural dataset encompassed 1,509 primary and revision total knee arthroplasties alongside 742 primary and revision total hip arthroplasties. Eligible records required complete electronic health record documentation of all initial, intermediate, and closing manual sponge counts, as well as documented execution of intraoperative radiofrequency field scanning before final skin wound closure. Any counting discrepancy triggered immediate procedural pauses to reconcile counts through re-scanning, physical search, and mandatory intraoperative plain radiography if discrepancies remained unresolved.
Across the 2,251 evaluated arthroplasty procedures, the combined counting and scanning protocol identified exactly three discrepant cases. The first discrepancy represented a false-negative radiofrequency wand scan occurring during a left revision total knee arthroplasty. During deep closure, circulating staff documented an incorrect manual count that remained unreconciled upon an immediate repeat count. The surgical team systematically passed the radiofrequency wand over the open surgical field, yet the wand failed to detect any retained sponge signal within the patient’s knee. When the wand was moved over the operating room waste receptacle, it registered a positive signal, leading clinicians to assume the missing sponge was among discarded materials.
Subsequent examination of the waste receptacle failed to recover the physical sponge, prompting the surgical team to obtain mandatory intraoperative plain radiographs before leaving the operative theater. The radiographic imaging revealed that the missing radiofrequency-tagged sponge was retained directly inside the femoral canal, firmly cemented beneath the base of the newly positioned femoral prosthesis. Clinicians elected to leave the cemented sponge in place intraoperatively, scheduling a secondary procedure for its controlled extraction.
The remaining two discrepant cases involved correct manual counts alongside initial positive radiofrequency wand detections across the surgical field. Following established institutional reconciliation workflows, surgical personnel verified manual counts and repeated the wand sweeps across the surgical field without modifying the sponges present, whereupon repeat scans yielded negative readings.
Investigators noted that these false-positive alerts likely arose from transient electromagnetic interference or physical interactions between the handheld wand and nearby metallic retractors or implant components. Although these false-positive alarms did not cause unnecessary surgical exploration, they introduced workflow delays by requiring count reverification and repeat scanning cycles. The specific detection device associated with both false-positive signals was taken out of service for recalibration, and no further aberrant signals were documented across the remainder of the study period. The authors emphasized that scanning waste receptacles can introduce confounding signals and foster false reassurance, recommending that wand sweeps remain strictly confined to the sterile operative field.
The study authors concluded that while radiofrequency-tagged surgical sponges serve as a helpful adjunct to surgical counting routines, the technology cannot completely replace manual visual counts or intraoperative radiography in orthopedic theaters. The mechanical forces required to seat joint implants, combined with thermal cement reactions and metallic signal interference, present unique physical failure modes not encountered in soft-tissue general surgery. The researchers emphasized that robust patient safety depends upon a layered approach combining audibly verified nursing counts, calibrated electronic adjuncts, and prompt radiographic verification whenever manual or technological discrepancies emerge during joint reconstruction.
Beyond immediate procedural workflows, the broader epidemiology of retained surgical items underscores why hospitals continue evaluating automated tracking adjuncts. Published surveillance estimates suggest that retained foreign objects occur in roughly one of every 5,500 operations, though researchers widely suspect true baseline rates remain substantially underreported because of variable institutional monitoring practices and persistent medicolegal concerns. In evaluating previous clinical literature, the study authors highlighted documented complications arising from retained materials across surgical disciplines, including the structural fragmentation of radiopaque surgical gauze requiring operative removal, a retained cotton ball discovered during revision surgery for delayed healing and persistent infection, and retained abdominal sponges culminating in chronic fistula formation after lapses in safety protocols. These historical precedents demonstrate that counting breakdowns and retained foreign materials can produce severe, prolonged clinical consequences if auxiliary detection mechanisms fail to operate reliably.
The investigation also detailed specific institutional data collection parameters and technical variables that influence radiofrequency detection reliability. Researchers identified eligible surgical candidates by extracting clinical records from the hospital’s EPIC electronic health record platform using established International Classification of Diseases procedural codes for primary and revision total knee and hip arthroplasties. Per Texas Health Resources system-wide clinical specifications, inclusion required complete documentation across initial, intraoperative, and final counts, while cases with missing count entries or undocumented scanning sweeps were excluded. Manual counting protocols required two trained staff members, including at least one registered nurse, to conduct audible and visual counts recorded contemporaneously on an operating room whiteboard. In analyzing why detection failures occur, the authors observed that physical tag orientation relative to the handheld scanning wand directly influences sensor sensitivity. Furthermore, signal transmission can be compromised not only by metallic implants and exothermic bone cement, but also by proximity to metal operating tables or mechanical crushing against rigid cortical bone.
Several critical methodological limitations temper the broader generalizability of the reported findings. Because the investigation was structured as a retrospective review conducted at a single high-volume orthopedic center, institutional outcomes may not mirror performance across community hospitals or centers with differing surgical workflows. More importantly, because only three discrepancies were detected across the 2,251 procedures, the extremely low event frequency prevented researchers from calculating formal diagnostic performance statistics, including sensitivity, specificity, and positive or negative predictive values within orthopedic cohorts. Intraoperative detection success also remains inherently contingent on operator scanning technique, physical wand proximity, and consistent equipment calibration, as demonstrated by the transient false-positive readings that necessitated device servicing.
To address these technical boundaries and operational uncertainties, the authors underscored the need for further clinical investigation. Prospective multicenter studies spanning diverse orthopedic surgical environments and varying implant designs are warranted to validate radiofrequency efficacy, refine scanning protocols, and optimize hardware sensitivity near dense hardware. The study authors also noted that the underlying dataset generated and analyzed during the investigation remains available from the corresponding author upon reasonable request. Until larger prospective validation trials establish definitive diagnostic accuracy across complex reconstructive environments, radiofrequency detection must function as a complementary safeguard rather than an autonomous replacement for disciplined manual counts and prompt radiographic imaging.
Subject of Research: Radiofrequency surgical sponge detection reliability and limitations during orthopedic joint arthroplasty
Article Title: The safety of radiofrequency surgical sponges in orthopedic surgery: a validation study in 2,251 arthroplasty procedures
Article References: Will, J. A., Anderson, L. F., & Ogden, S. (2026). The safety of radiofrequency surgical sponges in orthopedic surgery: a validation study in 2,251 arthroplasty procedures. Patient Safety in Surgery, 20(1), Article 19. https://doi.org/10.1186/s13037-026-00485-z
Image Credits: AI Generated
DOI: 10.1186/s13037-026-00485-z
Keywords: orthopedic surgery, total joint arthroplasty, total knee arthroplasty, total hip arthroplasty, retained foreign objects, surgical sponges, radiofrequency detection, patient safety, intraoperative complications, surgical counts, medical devices, bone cement, implant interference, false-negative detection, false-positive detection, intraoperative radiography, surgical technology
News Source: Ophelia Keating. (November 20, 2026). Radiofrequency Surgical Sponges Show Limitations During Joint Replacement Procedures. Scienmag.