Robotic assistance during total hip replacement may make surgery easier on the surgeon, not just more accurate for the patient, according to a new prospective study. Researchers found that when a single high-volume arthroplasty surgeon performed hip replacements with robotic help limited to the acetabular, or socket, side of the operation, the surgeon showed a lower heart-rate-variability-derived stress index and reported lower perceived workload than during conventional procedures, even though the robotic operations took significantly longer.
The study, published in the journal Arthroplasty, was designed as an exploratory, hypothesis-generating prospective comparative cohort study conducted at a tertiary academic practice between July 2025 and January 2026. It included 60 elective primary total hip arthroplasties, split evenly between 30 conventional procedures and 30 robot-assisted procedures, all performed by one fellowship-trained, high-volume surgeon who carried out roughly 70 conventional and 180 robotic hip replacements per year. Because a single surgeon performed every case, the researchers treated the individual procedures as repeated observations within one operator rather than as independent comparisons across many surgeons.
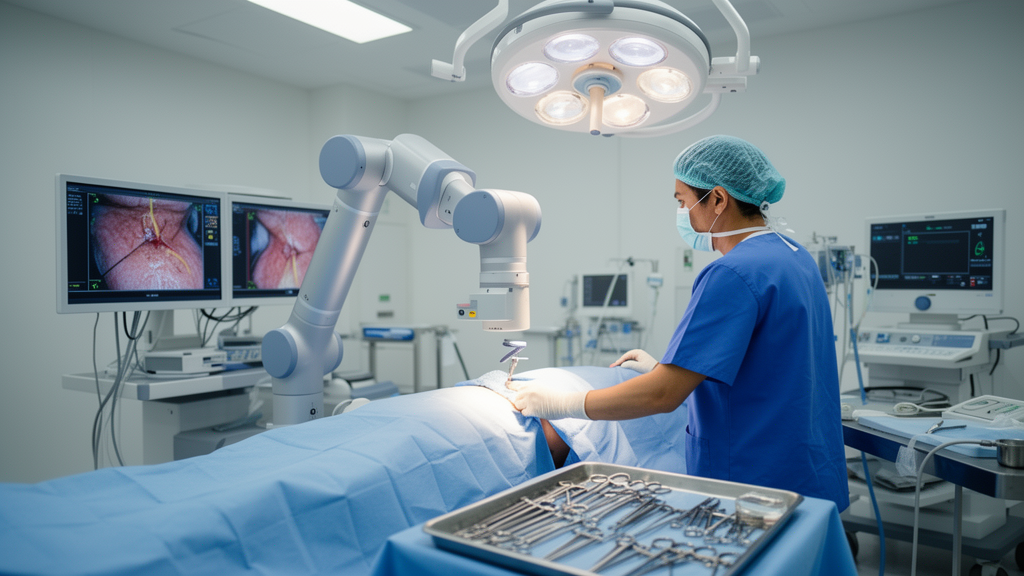
All operations followed a standardized posterolateral approach and were performed in the lateral decubitus position under general anesthesia, with each case scheduled as the first operation of the day to minimize the influence of accumulated fatigue. In the robotic group, the MAKO robotic-arm system from Stryker was used only for acetabular preparation and cup implantation, while femoral preparation and stem insertion were completed with standard instrumentation in both groups. The researchers emphasized that because the implant and instrumentation systems differed between the two techniques, the comparison represents the complete conventional and robotic workflows rather than the isolated effect of adding robotic guidance.
To capture the surgeon’s physiological state objectively, the surgeon wore a Hexoskin smart garment throughout every operation. The garment continuously recorded electrocardiography- and respiration-derived measures, including heart rate, a stress index reflecting sympathetic activation, heart rate variability summarized as the root mean square of successive differences, or RMSSD, respiratory rate, minute ventilation, and energy expenditure rate. Heart rate variability data were processed in Kubios HRV software using a five-minute moving window with a two-and-a-half-minute step, and the circulating nurse recorded the start and end times of four predefined operative phases in real time: exposure, acetabular preparation, femoral preparation, and wound closure. After each case, the surgeon completed the Surgery Task Load Index, or SURG-TLX, a validated surgery-specific questionnaire, within ten minutes of finishing the operation.
The headline result was a consistent pattern of lower surgeon strain during the robotic workflow. Whole-case stress index was significantly lower during robot-assisted surgery, with an adjusted mean difference of minus 2.52 (95 percent confidence interval minus 4.21 to minus 0.83, p = 0.004). The composite SURG-TLX score was also lower in the robotic group, with an adjusted mean difference of minus 0.47 (95 percent confidence interval minus 0.85 to minus 0.09, p = 0.039). Within the individual questionnaire domains, the differences were concentrated in task complexity, which was lower with robotic assistance by an adjusted mean difference of minus 1.45, and situational stress, which was lower by minus 1.18. Mental demands showed only a trend toward lower scores during robotic procedures, while physical demands, temporal demands, and distractions did not differ significantly between the two techniques.
Not every physiological measure moved in the same direction. Although the geometric mean RMSSD was numerically higher during robotic surgery, the adjusted between-group difference was not statistically significant, with a geometric mean ratio of 1.35 (95 percent confidence interval 0.98 to 1.86, p = 0.067). Heart rate, respiratory rate, minute ventilation, and energy expenditure rate likewise showed no significant differences between the two workflows. The authors interpret this pattern as indicating that the surgeon-centered differences associated with the robotic workflow were concentrated in the heart-rate-variability-derived stress index and in perceived task complexity and situational stress, rather than reflecting a generalized difference in autonomic state, physical exertion, or metabolic demand.
The phase-specific analysis added an important nuance. Using linear mixed-effects models adjusted for patient age, sex, body mass index, and American Society of Anesthesiologists physical status, with a random intercept for each case, the researchers found that stress index was lower during robotic surgery in exposure (mean difference minus 2.78), acetabular preparation (minus 1.92), and femoral preparation (minus 1.84), each statistically significant after false discovery rate adjustment. However, during wound closure, an identical manual phase in both groups, the stress index was actually higher in the robotic group, with a mean difference of plus 2.14. RMSSD was significantly higher during robotic surgery in the exposure and acetabular preparation phases, with geometric mean ratios of 1.60 and 1.62 respectively, but not during femoral preparation or wound closure.
The authors caution that the higher closure-phase reading may reflect the later position of that phase within the longer robotic procedures, cumulative fatigue, or end-of-case time pressure rather than the robotic step itself. Because the whole-case heart rate variability summaries were calculated across equally spaced moving windows, longer operative phases contributed more heavily to the overall estimates, meaning the whole-case values represent time-weighted averages of autonomic state rather than cumulative physiological burden. The coexistence of a lower whole-case stress index with a higher closure-phase stress index is therefore not contradictory, but it does show that the robotic workflow was not associated with lower workload throughout every part of the operation.
Operative time told a different story from the stress measures. Robotic procedures took significantly longer than conventional ones, at 141.50 plus or minus 30.76 minutes versus 116.86 plus or minus 21.88 minutes, a difference the authors attribute in part to the additional time required for registration, verification, and other technology-mediated workflow steps. Notably, operative duration and whole-case stress index were not directionally aligned in this surgeon, meaning the longer robotic procedure was nonetheless associated with a lower average physiological stress reading. On the patient side, cup inclination, cup anteversion, and the proportion of cups within the Lewinnek safe zone did not differ between groups, while absolute postoperative leg-length discrepancy was 1.3 millimeters lower in the robotic group at 2.9 versus 4.2 millimeters. Calculated total blood loss did not differ, and no patient in either group received a perioperative transfusion, experienced an intraoperative complication, or had a complication, readmission, reoperation, or revision within 90 days.
The study’s limitations are substantial and central to how the findings should be read. The single-surgeon design means the 60 procedures were repeated observations within one experienced operator who was well beyond the early robotic learning curve, and the results cannot be generalized to novice robotic surgeons, lower-volume surgeons, trainees, or surgeons as a group without multisurgeon validation. The study was not randomized, with technique selected through shared decision-making based primarily on patient preference, so residual confounding by unmeasured factors cannot be excluded, and the adjusted findings should be interpreted as associations rather than causal effects. No preoperative physiological baselines were recorded, the surgeon could not be blinded to the technique used, and expectation-related influences on both questionnaire ratings and autonomic responses cannot be ruled out. The authors also note that the sample size was planned for surgeon-workload outcomes and provides limited precision for the radiographic and safety results, and that no patient-reported outcome measures were collected. They describe their results as hypothesis-generating within-operator observations that warrant validation in multisurgeon studies examining different levels of surgical experience, robotic workflows, and operative contexts.
Subject of Research: Surgeon physiological stress and perceived workload during acetabular-only robot-assisted versus conventional total hip arthroplasty
Article Title: Acetabular-only robot-assisted total hip arthroplasty is associated with lower surgeon stress index and perceived workload than conventional total hip arthroplasty: a prospective comparative cohort study
Article References: Yu, M., Hu, M., Liu, T., Xu, Y., Yang, X., Peng, H., Weng, X., & Feng, B. (2026). Acetabular-only robot-assisted total hip arthroplasty is associated with lower surgeon stress index and perceived workload than conventional total hip arthroplasty: a prospective comparative cohort study. Arthroplasty, 8(1), Article 80. https://doi.org/10.1186/s42836-026-00442-2
Image Credits: AI Generated
DOI: 10.1186/s42836-026-00442-2
Keywords: total hip arthroplasty, robot-assisted surgery, surgeon workload, heart rate variability, stress index, SURG-TLX, wearable monitoring, MAKO robotic system, operative time, orthopaedic surgery, prospective cohort study, occupational health
News Source: Ophelia Keating. (October 28, 2026). Robot-Assisted Hip Surgery Lowers Surgeon Stress and Workload in Single-Surgeon Study. Scienmag.